Testing Sensory Levels With Pinprick and Light Touch
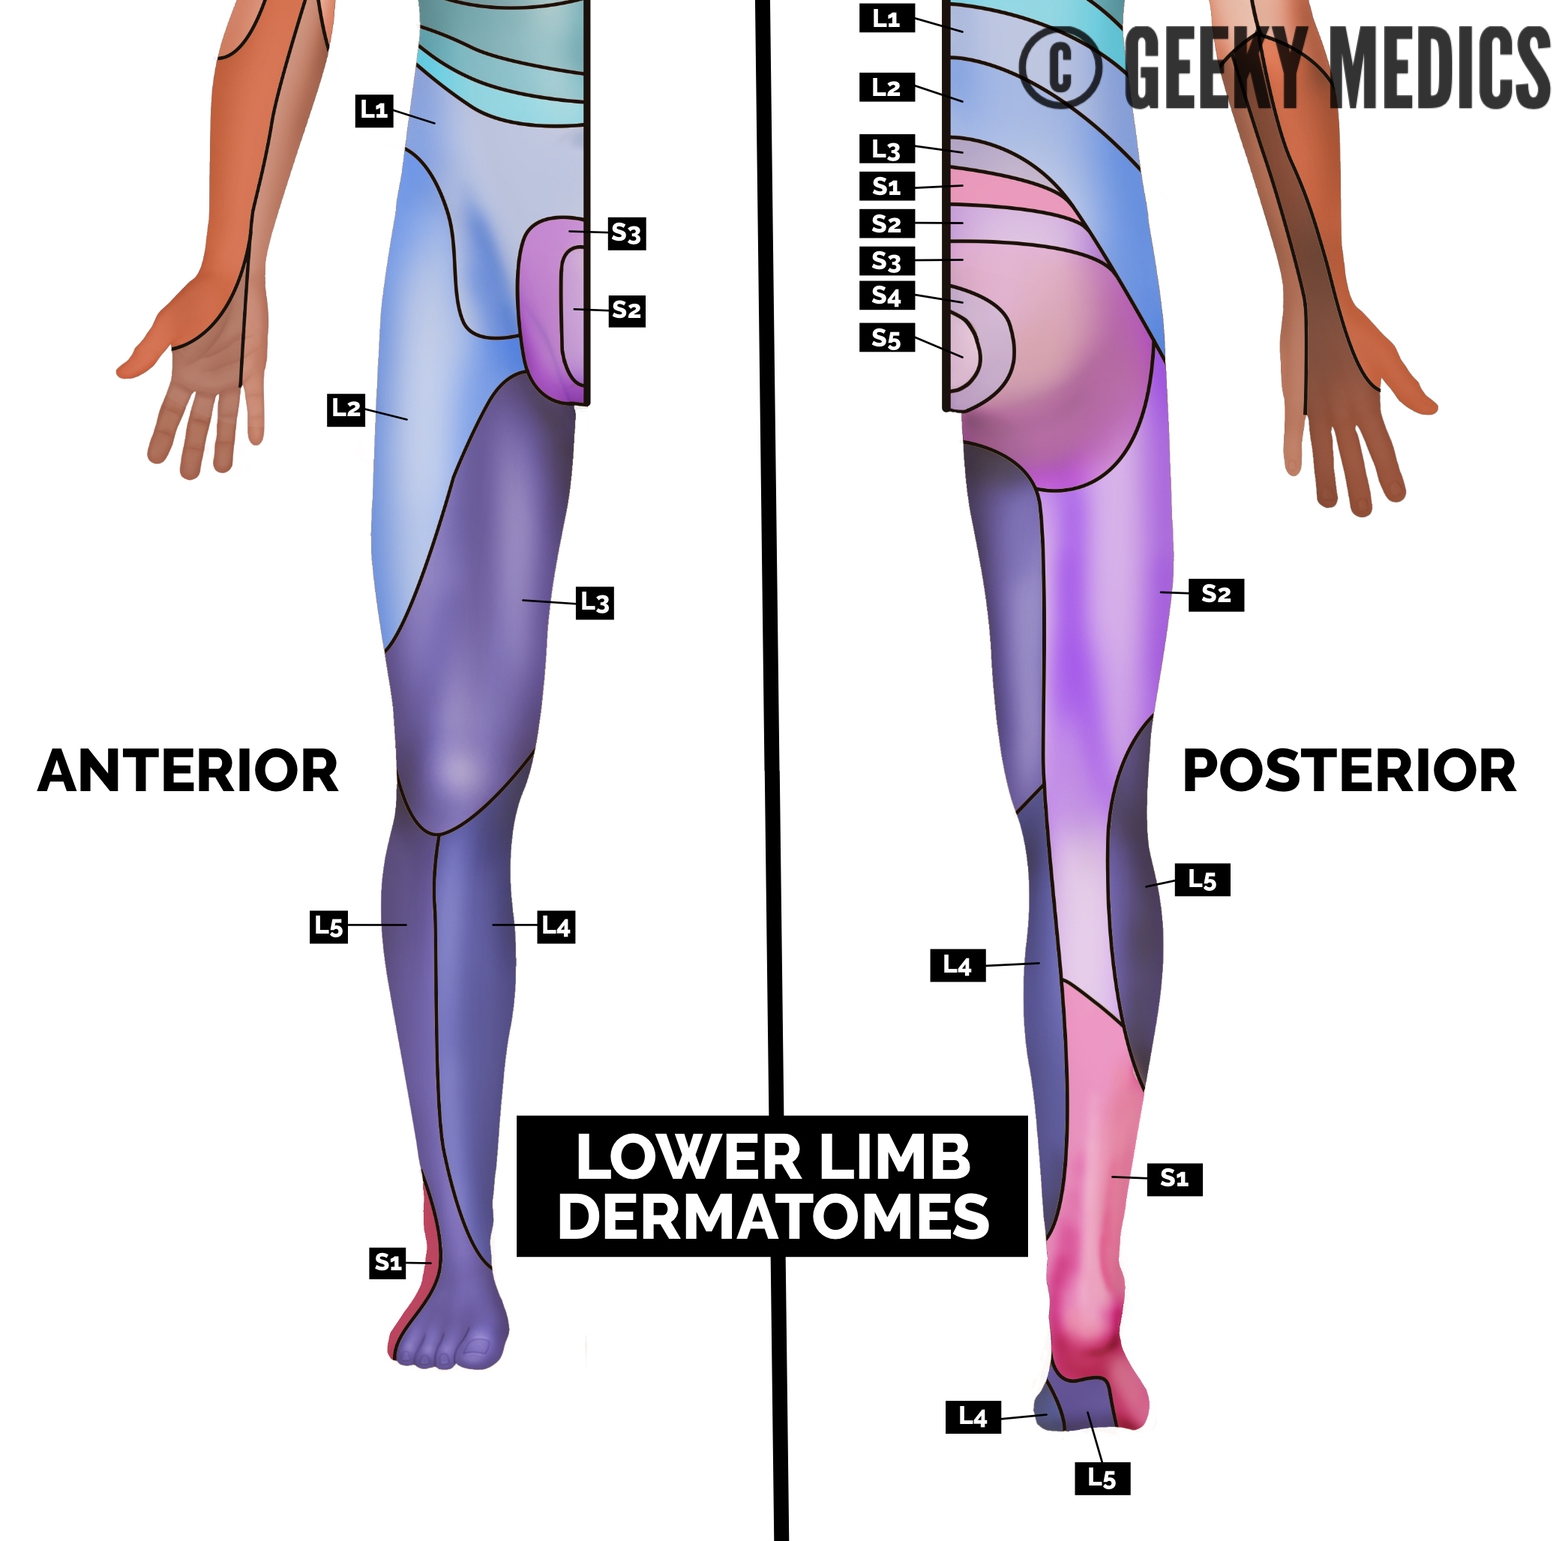
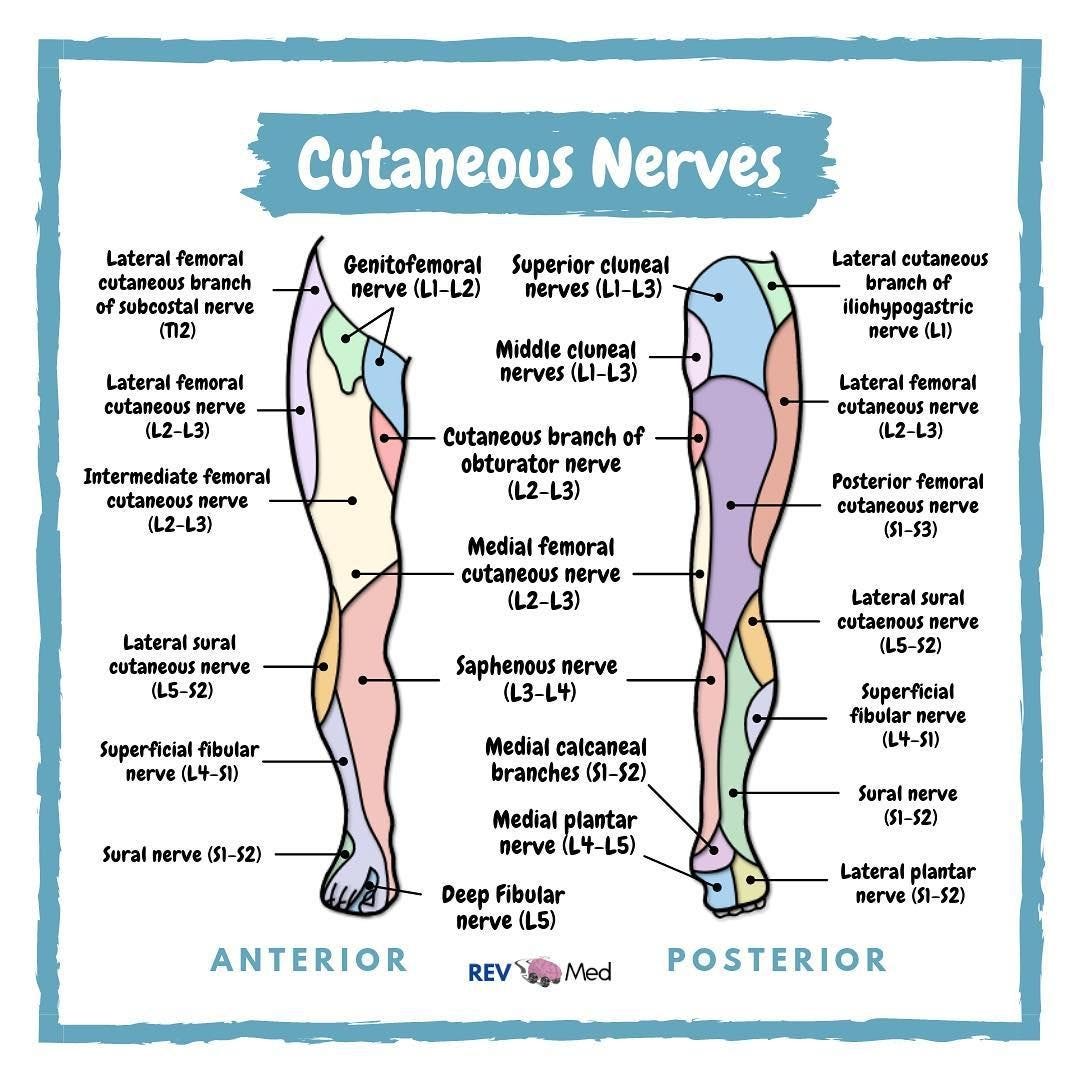
The standard dermatome map you see in textbooks is a rough approximation. In clinical practice, you will find that the actual sensory boundaries on a patient's leg rarely align perfectly with the idealized charts. I spent years relying on the L4-L5-S1 diagrams from Netter's Atlas during physical therapy assessments, only to realize too late that individual variation is massive. A patient's L4 dermatome might start significantly higher or lower than the textbook label suggests, and if you document findings rigidly without acknowledging this, your neurological mapping becomes essentially useless for surgical planning or precise diagnosis. I use a simple setup when mapping the lower extremities. A disposable monofilament for light touch, a sterile neurotip for pinprick sensation, and a skin marking pen. I start at the ankle and work my way up, testing each segment against the known nerve root territories. The L5 dermatome typically covers the dorsum of the foot and the big toe, but I have encountered at least a dozen patients where L5 sensation extended all the way down to the lateral malleolus, blurring into S1 territory. This kind of overlap is not rare. It is the norm. Most beginners treat dermatome borders as hard lines when they are actually soft zones of transition. The S1 root innervates the lateral foot and the sole. Testing the plantar surface with pinprick will tell you immediately whether S1 is intact or compromised. Patients with S1 radiculopathy from a herniated disc at L5-S1 often present with decreased sensation along the outer border of the foot and difficulty performing single-leg heel raises. That motor finding paired with the sensory loss is a strong clinical indicator, but you should never rely on one modality alone. Combine the sensory exam with reflex testing. The Achilles reflex maps directly to S1, and its absence strengthens the localization significantly.
L4 is trickier because its sensory field varies the most between individuals. The medial malleolus and the medial aspect of the lower leg are the classic landmarks, but in my experience, roughly thirty percent of patients show substantial overlap between L4 and L3 at the knee region. I once had a patient whose L4 pinprick sensation extended up to the mid-thigh, making it nearly impossible to distinguish a pure L4 deficit from an L3-L4 overlap. What I ended up doing was relying more heavily on the patellar reflex and the tibialis anterior strength testing, which are more reliably L4-specific. Sensory maps alone could not give me the confidence I needed for that case.
Why Dermatome Maps Fail You In Real Patients
The biggest problem with dermatome testing is that patients do not come in with clean, textbook presentations. Peripheral neuropathy from diabetes can cause a stocking distribution of sensory loss that overlaps multiple dermatomes, making it look like a radiculopathy when it is not. I spent two weeks chasing what I thought was an L5-S1 radiculopathy in a diabetic patient before a nerve conduction study revealed bilateral peroneal neuropathies instead. The sensory exam had pointed me in the wrong direction because I was treating the dermatome map as definitive rather than as a starting framework. Another common failure point is patient interpretation. Asking someone to identify sharp versus dull sensations on their leg assumes they can consistently distinguish between the two. Fatigue, cognitive impairment, anxiety, and even ambient temperature can affect their responses. I have seen patients report decreased sensation in an entire leg simply because they were anxious and hypervigilant, creating a false positive for a neurological deficit. Running the exam in a warm room and repeating the test after five minutes of rest usually clarifies the picture. The overlapping nature of dermatomes means that a single nerve root lesion often produces minimal or no sensory loss. The body has redundant innervation from adjacent roots, so losing one dermatome does not create a blind zone unless two or more adjacent roots are damaged simultaneously. This is why myofascial pain syndromes and trigger points in the gluteal or piriformis region can refer pain into L5 or S1 distributions without any actual nerve root compression. Treating the root when the real problem is muscular waste time and delays recovery.
Get the Full Details

A Practical Workflow For Mapping The Legs
I start every exam by asking the patient to lie supine with legs slightly externally rotated. This position relaxes the hamstrings and makes the posterior aspects of the legs more accessible. I test light touch first using the monofilament, applying it perpendicularly with enough pressure to bend the filament slightly. I then switch to the neurotip for pinprick, working in a systematic pattern from distal to proximal within each dermatome zone. The key zones to document are the great toe dorsum for L5, the lateral foot margin for S1, the medial malleolus for L4, and the anterior thigh just below the inguinal ligament for L2. If you find any asymmetry between the left and right sides, note the exact millimeter distance from a reliable bony landmark. Saying "L5 is diminished on the right" is not specific enough for follow-up assessments or for communicating with physicians who will use your findings to guide treatment. I also recommend testing two-point discrimination on the sole of the foot when you need finer sensory resolution. The standard clinical exam often stops at pinprick and light touch, but two-point discrimination can detect subtle dorsal root ganglion dysfunction that the basic exam misses. The thresholds on the plantar surface are typically eight to twelve millimeters in healthy adults, increasing with age and with conditions like tarsal tunnel syndrome or early peripheral neuropathy.
If you are mapping for a surgical referral or a medicolegal evaluation, take photographs of the marked skin immediately after the exam. Ink can fade or smear within an hour, and patient positioning changes the skin tension enough to shift the apparent location of the markings. A quick photo provides an unambiguous record that can be referenced later without relying on memory or handwritten notes that may be illegible.
Common Mistakes That Skew Your Results
The most frequent error I see is testing through clothing or over lotions that reduce skin friction. A thin pair of sweatpants or a residue of moisturizer can dull the pinprick sensation enough to create a false impression of hypoesthesia. Always expose the skin directly and work on a clean, dry surface. Another mistake is using excessive force with the neurotip, which causes the patient to flinch and interpret the stimulus as pain rather than sharp sensation. The tip should barely penetrate the stratum corneum. A light brush is sufficient. Some clinicians skip the S2 dermatome entirely, focusing instead on L4 through S1. This is a blind spot. The perianal region and the posterior calf are S2 territory, and loss of sensation here is a red flag for cauda equina syndrome. I make it a rule to always test S2 when assessing lower extremity sensation because missing it has real consequences. One patient presented with vague leg numbness that I initially attributed to lumbar spondylosis. It was not until I tested the saddle area and found decreased S2 sensation that I ordered an urgent MRI, which revealed a massive disc herniation compressing multiple nerve roots. Another mistake is assuming that a normal dermatomal sensory exam rules out nerve root pathology. As I noted earlier, overlapping innervation means that single-root lesions often spare sensation entirely. If the clinical picture suggests radiculopathy but the sensory exam is normal, you should move on to reflex testing, motor strength grading, and provocative maneuvers like the straight leg raise rather than assuming the nerves are fine because the pinprick test is symmetric.

When To Look Beyond The Dermatome Map
Dermatome mapping is a screening tool, not a diagnostic endpoint. If your findings are inconsistent with the expected patterns, or if the sensory loss does not follow any recognizable dermatomal or peripheral nerve distribution, you need to expand the differential. Peripheral neuropathies, spinal stenosis, disc herniations, and even psychogenic sensory disturbances can all produce atypical patterns that a dermatome chart cannot explain. I keep a reflex hammer and a tuning fork at ninety-six hertz in my kit for this reason. When the dermatome exam yields ambiguous results, adding reflex grading and vibration sense testing often clarifies whether the issue is radicular, peripheral, or central. A single abnormal reflex combined with a non-dermatomal sensory change usually points away from a simple root lesion and toward a broader process that needs imaging or laboratory workup. The lower extremity dermatome map is useful, but it is not authoritative. Your hands, your documentation, and your willingness to notice when the pattern breaks are what actually determine whether you catch the real pathology or miss it. Treat the chart as a reference, not a rulebook, and you will avoid the traps that catch most people who learn this material for the first time.