Why University Medical Center Heliports Matter More Than Most People Realize
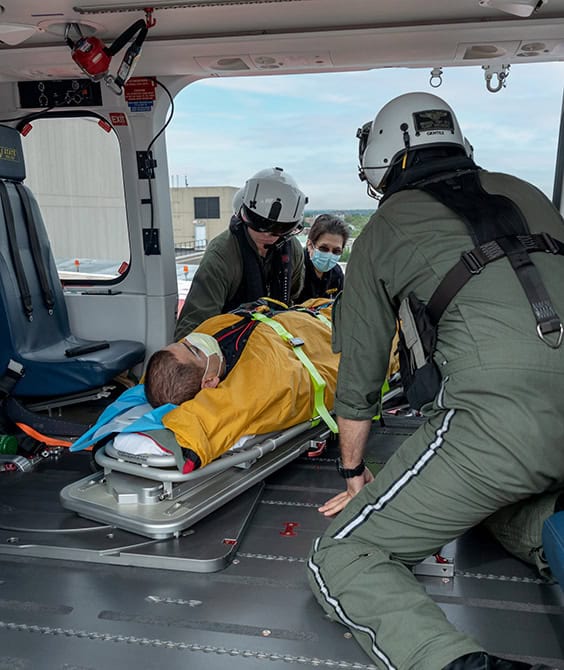
Most people think of hospital heliports as dramatic rescue scenes from television. The reality is much more procedural, less cinematic, and honestly far more important than the dramatized version would suggest. A university medical center heliport operates as a tightly coordinated node in the emergency medical services network, connecting trauma centers, rural dispatch, aviation services, and hospital intake teams into a single operational chain. When a critical trauma patient arrives from a rural area three hours away by ground, the difference between helicopter and ambulance transport isn't just about speed. It's about the entire cascade of preparation that happens while the aircraft is still airborne. The trauma team gets activated before takeoff. Blood products are cross-matched based on the mechanism of injury reported over the radio. Operating rooms are held or cleared depending on the predicted arrival window. All of this depends on the heliport being functional, certified, and properly integrated into the regional EMS system. I spent several years working with helicopter EMS coordination at a Level I trauma center, and the thing nobody tells you about heliport operations is how much of the actual work happens on the ground before the rotors even spin up. The landing zone needs to be assessed for wind patterns, overhead obstructions, surface conditions, and ground crew positioning every single time. Weather minimums for rotorwing aircraft are different from fixed-wing, and most people don't understand the distinction until they're standing on a rooftop at 2 AM trying to figure out why the flight got diverted.
The technical standards for these heliports are governed by FAA guidelines, state health department regulations, and often joint commission requirements that go beyond what the FAA mandates. You need a certified hardstand or roof landing surface with proper load-bearing capacity, obstacle-free approach and departure paths, fire suppression systems in many cases, and clear communication links to both air traffic control and the hospital's emergency operations center. The lighting system has to meet specific intensity and color standards for nighttime operations, which means regular maintenance and testing that many facilities treat as an afterthought until an inspection forces their hand. Here's something most facility managers don't realize: the biggest operational bottleneck isn't the helicopter itself or the weather. It's ground handling coordination. I once watched a perfectly good landing get aborted because the ground crew hadn't positioned the firefighting equipment in the correct staging area per the facility's own emergency action plan. The pilot had the green light from the tower, the trauma team was ready, and the whole operation fell apart over a paperwork violation about where the extinguisher truck needed to sit. We ended up writing a revised ground handling checklist that reduced pre-arrival setup time from about twenty minutes to roughly eight, and more importantly eliminated that category of avoidable diversion. The economic angle is worth mentioning because it's often overlooked. A university medical center heliport represents a significant capital investment, but the return calculation isn't straightforward. You're not measuring revenue per flight in any simple way. What you're really measuring is outcomes data: mortality reduction for trauma patients within the golden hour window, avoidance of ground transport delays through mountainous or congested terrain, and the ability to perform organ procurement flights that wouldn't be feasible otherwise. Some studies have shown ground transport times reduced by sixty to seventy percent in rural-to-urban transfer scenarios, which translates directly into survival rates for certain types of traumatic injuries.
One counter-intuitive fact about these operations: smaller helicopter models often outperform larger ones in hospital rooftop environments despite having less range and payload capacity. The Bell 407 or Airbus H130 family can access tighter landing zones and requires less infrastructure than a Medevac-class medium helicopter. Many university hospitals that upgraded to larger pad capabilities found they were grounding flights more often because the larger aircraft demanded wider approach corridors and stronger structural reinforcement. The answer for many facilities turned out to be maintaining a multi-tiered capability with different aircraft sized for different mission profiles rather than going all-in on one platform. Staffing is another area where expectations and reality diverge significantly. You need certified heliport safety technicians who understand aviation ground handling, not just hospital orderlies who've been assigned to the job. These are people who read ATIS reports, understand NOTAMs, can communicate with pilots using standard phraseology, and know when to absolutely not allow a landing regardless of how critical the patient situation is. I've seen facilities cut corners here and it always comes back to haunt them during an actual emergency when every second counts and someone on the ground needs to make the right call without second-guessing. Documentation and regulatory compliance for a medical center heliport involves more layers than most people expect. Beyond FAA Part 135 requirements for the air medical operators, there are state EMS regulations, hospital accreditation standards, occupational safety reporting, and often university-specific policies that add additional bureaucratic weight. Monthly inspection reports, quarterly drill documentation, annual certification reviews, and continuous quality improvement tracking all feed into this system. The administrative burden is real, but skipping any of it creates liability exposure that isn't worth the effort to avoid.
Get the Full Details

If you're evaluating whether your facility needs a heliport or should maintain an existing one, the first question to answer honestly is your catchment radius. Patients who can reach your trauma bay within sixty minutes by ground transport through normal traffic conditions may not benefit significantly from air medical transport. But if your service area includes rural regions with single-lane roads, mountain passes, or areas where traffic congestion routinely adds two or more hours to transport times, the heliport becomes a genuine lifeline rather than a prestige project. Be honest about that distinction because the funding and political support required to sustain these operations depends on proving actual utilization, not aspiration.