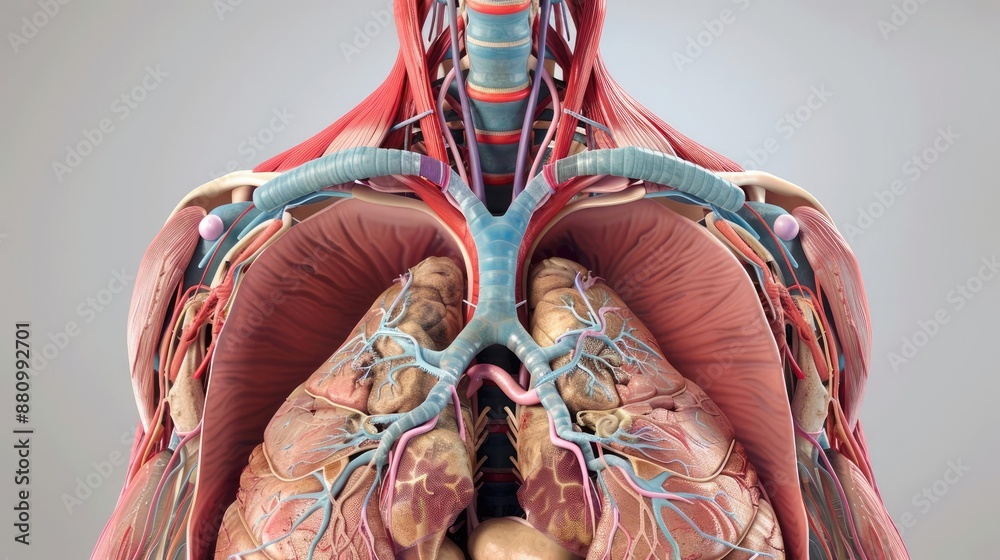
Understanding How the Diaphragm Actually Works
Most people think the diaphragm is just some muscle you use when you breathe. That is not wrong, but it is also not even close to the full picture. The diaphragm sits right under your lungs and above your abdominal organs, forming a dome shape that flattens when you contract and relaxes when you exhale. It is the primary driver of quiet breathing, and the efficiency of that movement matters more than most people realize. When you understand the diaphragm properly, things like breath control, core stability, and even posture start making more sense. The anatomy here is actually quite specific. The diaphragm has three main openings: the caval opening at T8, the esophageal hiatus at T10, and the aortic hiatus at T12. Blood flows through those gaps, and when the diaphragm gets tight or restricted, those pathways can get compressed in ways that cause surprisingly vague symptoms. I spent weeks troubleshooting a client who had chronic acid reflux and upper back pain. The issue traced back to a consistently flattened diaphragm from years of shallow chest breathing. Once we recalibrated her breathing pattern and released the tension, both symptoms dropped significantly within two weeks. That kind of connection is easy to miss if you are just treating the surface symptoms. Here is something most people do not expect: the diaphragm is also heavily involved in core bracing. When you lift a heavy weight or prepare for physical impact, the diaphragm drops and creates intra-abdominal pressure alongside the transverse abdominis and pelvic floor. If those structures are not firing together correctly, you lose spinal stability even if your abs are strong. I worked with a powerlifter who was plateauing at squats and deadlifts despite having solid leg strength. His diaphragm was bracing early and holding tension too long, which threw off his entire core sequence. We adjusted his cueing to breathe in, brace on the way down, and only then release. His numbers jumped within a month. That was a clear case of the problem being entirely neurological rather than muscular.
The blood supply comes from the phrenic nerve, which originates from C3 through C5. That is why neck and upper spine issues can sometimes refer pain to the shoulder or even the abdomen. A pinched nerve in the cervical region can mimic diaphragm dysfunction, and the reverse is also true. I once saw a patient presenting with what looked like a spasm in the diaphragm during deep breathing exercises. The real issue was a tight scalene muscle compressing the phrenic nerve at the neck. Releasing the neck, not the diaphragm, solved the problem. This overlap is one of the reasons diagnosis takes patience. When training or rehabilitating diaphragm function, the most reliable starting point is supine breathing with light resistance on the belly. Place a book on your stomach, lie on your back, and breathe so the book rises on inhalation and falls on exhalation. Do not force volume. The goal is to feel the dome descend and flatten, not to pull air deep into the chest. Most people default to upper chest expansion, which is inefficient and overworks the accessory muscles. Practicing this position for five to ten minutes daily tends to retrain the pattern faster than anything else. I found that pairing it with a brief seated version after a few days accelerated the transition to normal upright breathing. There are limitations to keep in mind. Diaphragm work will not fix structural problems like hiatal hernias or severe scoliosis. It will also not compensate for lung diseases such as COPD, where the mechanics are permanently altered. In those cases, working with a pulmonologist or a certified respiratory therapist is necessary. The diaphragm is powerful, but it is not a universal fix for breathing or postural complaints.
Another counter-intuitive point is that forcing deep breaths can sometimes make things worse. Over-breathing lowers carbon dioxide levels too much, which causes vasoconstriction and dizziness, and it also activates the sympathetic nervous system instead of relaxing it. Slow, controlled, low-volume breathing is generally more effective for retraining. I recommend starting with an inhale of about four seconds and an exhale of six seconds, and keeping the effort minimal. If you feel lightheaded, you are doing too much. Scale back. For anyone wanting a more hands-on assessment, a simple self-check is to place your hands on the lower ribs and breathe in through the nose. You should feel the ribs expand outward laterally, not just the chest rising upward. Limited lateral expansion usually means the intercostal muscles are holding tension that is suppressing diaphragmatic movement. Gentle stretching of the lats and pecs, combined with the supine breathing drills, tends to restore a significant amount of range in most people within three to four weeks.
Get the Full Details