Understanding Extreme Morbid Obesity and the Medical Journey Back
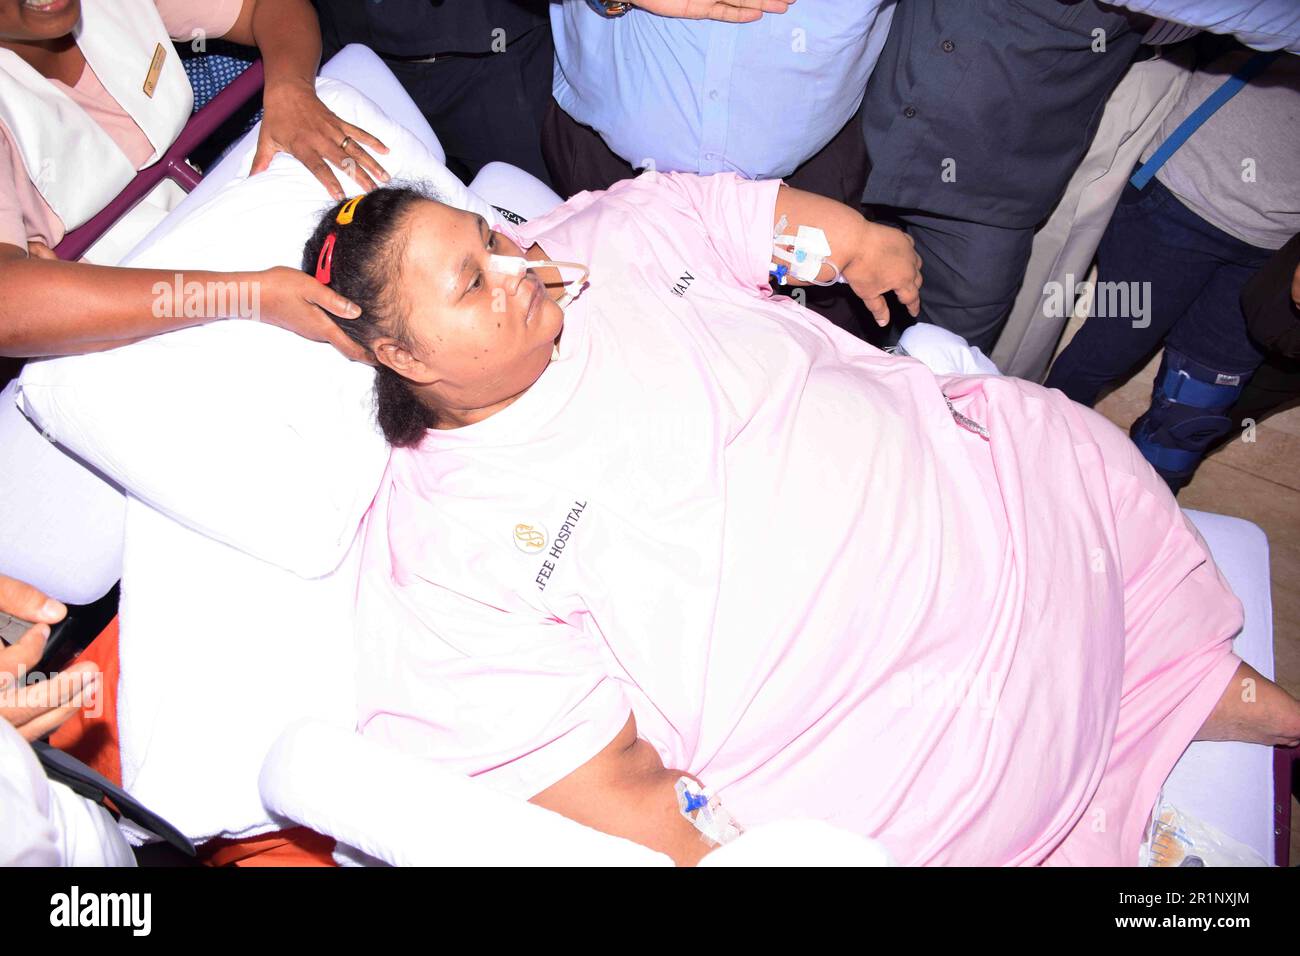
Eman Ahmed Abd El Aty from Egypt became one of the most documented cases of extreme morbid obesity in modern medical history. At her peak weight, she was recorded at approximately 500 kilograms (around 1,100 pounds), which placed her under global medical scrutiny. Her case drew attention not because of spectacle, but because of the sheer complexity of treating a body that large. What follows is a look at what actually happened, how the medical system responded, and the realities of bariatric intervention at that scale. Eman was born in 1991 in a rural area outside Cairo. Early on, her family noticed she was gaining weight far faster than other children. By her teens, the weight gain had become unmanageable by any standard approach. Local hospitals in Egypt lacked the equipment and surgical capacity to intervene effectively. She was essentially stranded medically until a American medical team took an interest in her case around 2017. The decision to operate was not straightforward. Bariatric surgery at 500 kilograms carries risks that most surgeons would not attempt. The anesthetic dosing alone is nearly impossible to calculate with standard charts. The surgical team at the University of Mississippi Medical Center spent months planning every detail before they ever made an incision. They coordinated with nutritionists, psychologists, physical therapists, and critical care specialists. This was not a single-surgeon operation. It was a full institutional commitment.
What happened next was a staged intervention. Instead of going straight to gastric bypass or sleeve gastrectomy, the team first had Eman lose some weight through a medically supervised diet. This was critical because operating on a patient at 500 kilograms directly dramatically increases the risk of complications. They used a very low-calorie protein formula to reduce her weight gradually while preserving muscle mass. Over several months, she lost roughly 100 kilograms before the surgery was even considered viable. Once she reached a safer threshold, she underwent bariatric surgery. The exact procedure details were not fully disclosed to the public, but reports indicate it involved a combination of surgical restriction and metabolic adjustment. After the surgery, she entered a long rehabilitation phase. Physical therapy was essential. Moving a body that size, even after significant weight loss, requires relearning basic motor functions. Her legs and joints had been under extreme load for most of her life. Tendons, cartilage, and ligaments had adapted to a stress level most people never experience. Her current status, as of the latest available reports, is that she continues to lose weight and remains under medical supervision. She is not "cured" of obesity. Obesity is a chronic metabolic condition. Surgery is a tool, not a reset button. Without ongoing dietary management, behavioral therapy, and regular medical checkups, weight regain is extremely common. Studies show that roughly 20 to 25 percent of bariatric patients experience significant weight regain within five to seven years post-surgery. That number goes up when the starting weight is extreme, because the metabolic adaptations are more severe.
One thing that rarely gets discussed in coverage of cases like Eman's is the psychological component. Extreme obesity almost always coexists with some form of psychological distress. Depression, trauma, binge eating disorder, and deeply ingrained coping mechanisms around food are common. I have spoken with clinicians who treat severely obese patients and the consensus is blunt: surgery without psychiatric support has a much higher failure rate. The weight comes back because the underlying behaviors that drove the weight gain were never addressed. In Eman's case, the medical team at Mississippi included mental health professionals in her ongoing care plan. That is the standard of care that should apply to every bariatric patient, not just high-profile cases. Another under-discussed factor is the financial reality. Bariatric surgery for a patient at Eman's starting weight can cost well over $100,000 when you factor in pre-op preparation, the surgery itself, hospital stay, rehabilitation, and long-term follow-up. Most insurance plans in the United States will cover bariatric surgery if certain criteria are met, but those criteria usually include documented attempts at supervised weight loss beforehand, a BMI above 40, and proof of comorbidities like sleep apnea or hypertension. International patients seeking treatment in the U.S. often do not qualify for standard insurance coverage. Eman's case was covered through a combination of charitable medical outreach and institutional sponsorship. That is not a model that scales. Most people with extreme obesity simply cannot access this level of care. There are also limitations to what bariatric surgery can achieve. It is not a cosmetic procedure. It does not guarantee a normal life. Some patients develop nutritional deficiencies that require lifelong supplementation. Others experience dumping syndrome, where food moves too quickly through the digestive tract, causing nausea, diarrhea, and dizziness. A small percentage develop strictures or internal hernias that require additional surgery. None of this is highlighted in media coverage, which tends to frame the story as a simple before-and-after transformation. The reality is messier and more complicated.
Get the Full Details

For anyone researching this topic or considering bariatric intervention for themselves or someone they know, the most important thing to understand is that the surgery is the beginning, not the end. The months of pre-operative preparation, the years of post-operative lifestyle adjustment, the constant medical monitoring, and the psychological work are all non-negotiable components. Skipping any of them significantly increases the risk of complications or weight regain. There are resources available for people seeking information. The American Society for Metabolic and Bariatric Surgery maintains a patient resource center at asmbs.org. The Obesity Society at theobesitysociety.org provides research-backed information on treatment options. Local support groups, whether in person or online, can also be valuable. Isolation is one of the biggest barriers to long-term success after bariatric surgery. Eman's case is notable because it represents one of the most extreme examples of treatable morbid obesity in recent medical history. Her journey shows that even at weights most clinicians would consider inoperable, intervention is possible with the right resources and team. It also shows that survival is only the first step. What comes after requires sustained effort, medical oversight, and support systems that most healthcare systems are not designed to provide.


