What Interstitial Lung Disease Actually Is
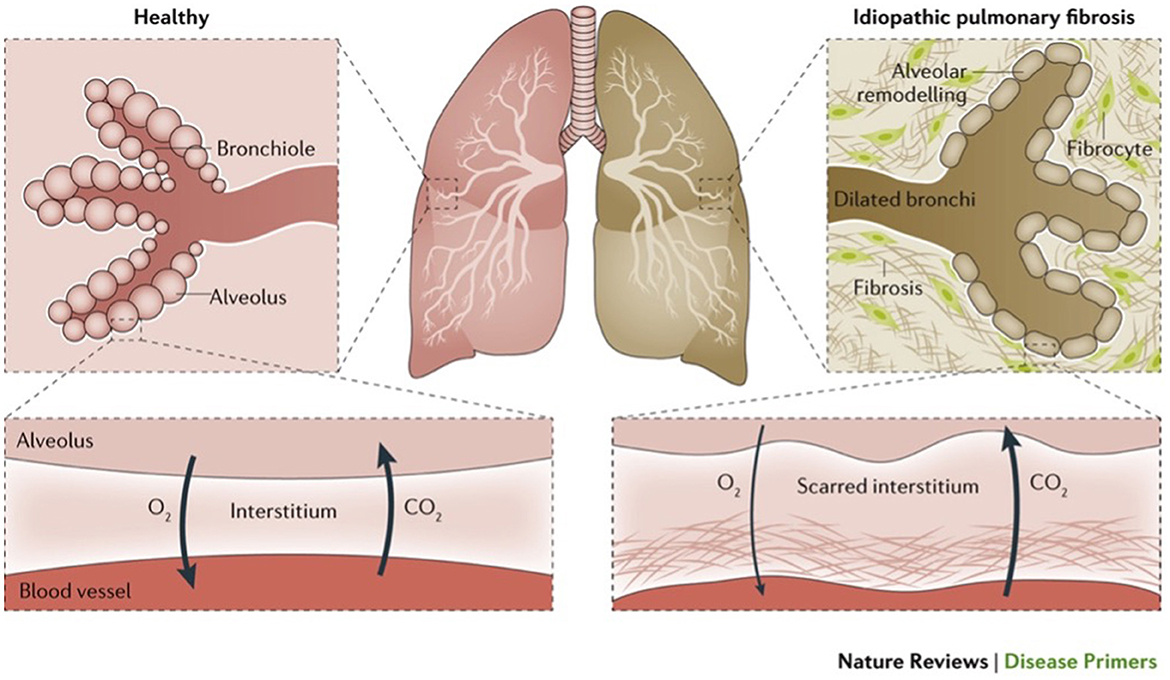
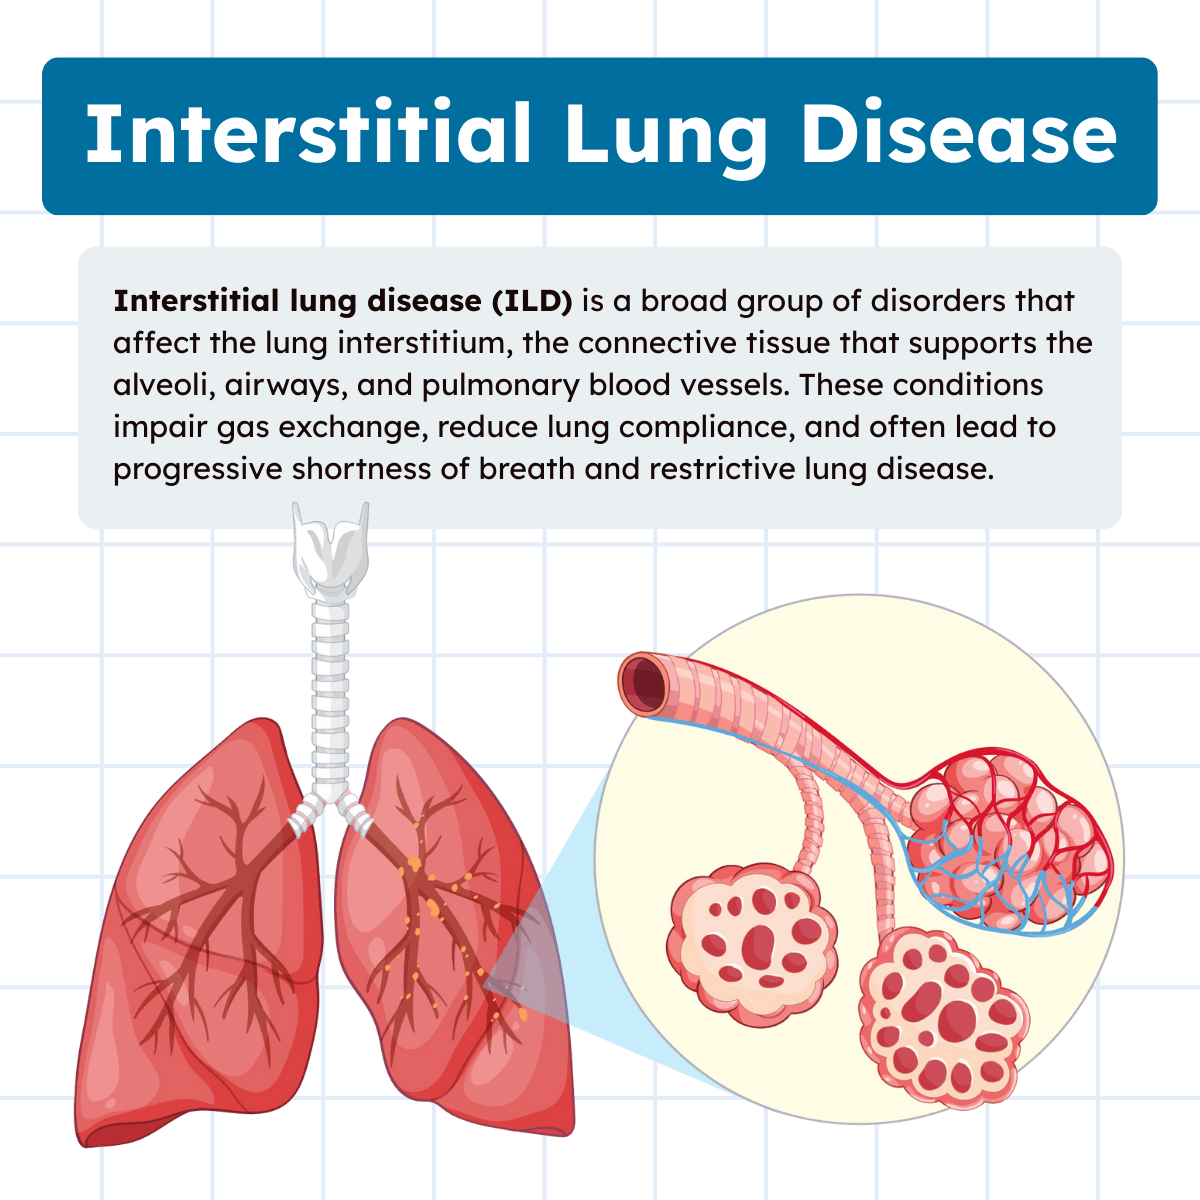
Interstitial lung disease isn't one illness. It's a broad category covering over 200 conditions that all share one thing in common: scarring or inflammation of the lung interstitium, which is the tissue and space around the air sacs. When that tissue thickens, the lungs lose elasticity and oxygen can't cross into the bloodstream efficiently. Kurt Russell was diagnosed with pulmonary fibrosis, a specific form of ILD, in 2015. He talked openly about the fear that came with it. The diagnosis itself was sudden for him. He was mid-production on a show when doctors found nodules on his lungs. He had to pause everything while they figured out exactly what was happening. His case highlights something most people don't understand about ILD. It often presents with symptoms that look like something much less serious. Shortness of breath during routine activity. A persistent dry cough that won't go away. Fatigue that you just brush off as aging or stress. By the time the diagnosis lands, the disease has frequently been progressing for months or even years. That's the core mystery and the core danger. ILD is deceptive. The diagnostic path is not linear. You start with a high-resolution CT scan, usually a thin-cut HRCT. Standard CT misses early fibrotic changes. I've seen radiologists catch patterns that a standard protocol completely overlooked because they knew what to look for. The HRCT can reveal a reticular pattern, honeycombing, ground-glass opacities. Those three findings together point toward usual interstitial pneumonia, the pattern most associated with progressive pulmonary fibrosis.
Beyond imaging, pulmonologists order pulmonary function tests. The key metric is FVC, forced vital capacity, and DLCO, the diffusion capacity for carbon monoxide. DLCO tends to drop earlier than FVC. Patients often feel fine breathing-wise but their numbers are already declining. This mismatch between how you feel and what the tests show is genuinely confusing for people who haven't dealt with it before. If imaging and function tests still leave questions open, a multidisciplinary discussion happens. That means pulmonologists, radiologists, and sometimes rheumatologists reviewing everything together. For autoimmune-related ILD, which accounts for a significant portion of cases, blood work for antibodies like anti-CCP, rheumatoid factor, and ANA becomes critical. I once worked through a case where the lung pattern looked idiopathic but the antibody panel revealed undiagnosed scleroderma. That changed the entire treatment direction.
Treatment Landscape And What Actually Gets Prescribed
Fibrosis-specific medications exist now. Nintedanib and pirfenidone are the two FDA-approved antifibrotic drugs. They don't reverse scarring. They slow progression. Nintedanib targets multiple kinase receptors involved in fibroblast proliferation. Pirfenidone has anti-inflammatory and antifibrotic properties through different pathways. Clinical trials show these drugs reduce the rate of FVC decline by roughly 50 percent compared to placebo. That's meaningful if you think about it in terms of preserving lung function over time. Oxygen therapy comes into play when saturation drops below 88 percent during activity or sleep. Many patients resist supplemental oxygen at first. The tubing feels cumbersome. The equipment makes you feel sick. But I've watched patients who initially refused it start sleeping better within days because their overnight desaturations improved significantly. The quality of life shift is real. Pulmonary rehabilitation is another standard recommendation. It's not just exercise. It's education on energy conservation, breathing techniques like pursed-lip breathing, nutrition counseling, and psychological support. Programs typically run 6 to 12 weeks. Compliance rates are moderate. People drop out because it's inconvenient or because they don't feel immediate results. But the data is clear. Patients who complete pul rehab have fewer hospitalizations and better exercise tolerance.
Get the Full Details

When Transplant Evaluation Becomes Relevant
Lung transplantation is the only definitive option for end-stage ILD. The criteria are strict. Most centers want patients under 65 to 70 depending on overall health. You need to be off supplemental oxygen in many cases, or at most on low-flow oxygen. Delayed referral is a well-known problem. Patients get referred too late and miss the window where transplant listing makes sense. The wait time for a donor lung averages around 12 to 18 months in the United States. Some people decline before they get an offer. Post-transplant survival rates are reasonable. Five-year survival sits around 50 to 55 percent for fibrotic ILD recipients. It's not a cure. Recurrence of certain ILD types, especially autoimmune-associated forms, can affect the graft. But for the right candidate, it extends life meaningfully.
A Specific Problem I Encountered And How I Handled It
Here's a practical issue that doesn't get discussed enough. Medication side effects can mimic disease progression. Pirfenidone causes nausea, photosensitivity, and elevated liver enzymes in a substantial number of patients. Nintedanib causes diarrhea that can be severe. I once had a patient whose FVC dropped sharply over three months and the team initially suspected rapid disease progression. Turns out he'd been taking his pirfenidone without food because it made him nauseous, and his nutritional intake had deteriorated significantly. Once we adjusted the dosing schedule and added antiemetics, his weight stabilized and the FVC decline slowed dramatically. The workaround was treating the side effects aggressively before assuming the drug was failing. One major misconception is that ILD equals pulmonary fibrosis. Pulmonary fibrosis is one pattern of ILD. There are acute forms like acute interstitial pneumonia that progress over weeks. There are connective tissue disease-associated forms linked to rheumatoid arthritis or lupus. There are hypersensitivity pneumonitis cases triggered by environmental exposures like bird feathers or mold. Each has different management priorities. Treating hypersensitivity pneumonitis without removing the antigen exposure will fail regardless of medications. Another misconception involves smoking. Smoking is a major risk factor for pulmonary fibrosis and makes it progress faster, but some forms of ILD like Langerhans cell histiocytosis are almost exclusively seen in smokers and actually improve with smoking cessation alone. The relationship isn't uniform across the spectrum.
Monitoring And Follow-Up Rhythm
Standard follow-up for stable ILD is every 3 to 6 months. That includes PFTs, six-minute walk tests, and clinical evaluation. If the patient is on antifibrotic therapy, liver function tests are needed periodically for pirfenidone. Nintedanib requires monitoring for diarrhea and hepatic effects as well. Every progression event should prompt reassessment of the diagnosis. A change in pattern on HRCT might indicate something new has developed alongside the original condition. Patients and caregivers should keep a symptom diary. Note changes in cough frequency, sputum production, exertional tolerance, and any new swelling in the ankles which could signal developing pulmonary hypertension. Pulmonary hypertension complicates roughly 20 to 30 percent of advanced ILD cases and significantly worsens prognosis. It's often underdiagnosed because clinicians focus on the lung parenchyma and miss the vascular component.
What I Wish People Understood Sooner
The emotional toll of an ILD diagnosis is underestimated. It's a progressive condition for many subtypes. Patients hear "we'll monitor it" and initially feel relieved. Then six months later they're more short of breath. The uncertainty creates a specific kind of anxiety. Support groups help but most Pulmonary hypertension and ILD patients go through periods of denial, anger, and Bargaining before reaching acceptance. That's normal. Practical advice that actually matters: get seen at a center with ILD expertise if possible. General pulmonologists are competent but ILD is complex and nuanced. Second opinions change management in a meaningful percentage of cases. Bring all prior imaging on CD. Newer CT scanners and reading protocols evolve constantly. Old films reviewed by a specialized radiologist might show something that was missed the first time around. The field is advancing. Clinical trials for new antifibrotic approaches, stem cell therapies, and better transplantation protocols are ongoing. It's not a static landscape anymore. The options available today are materially different from what existed five years ago. That alone is worth knowing.