What You Actually Need To Know About Eyelid Structure Before You Start Messing Around
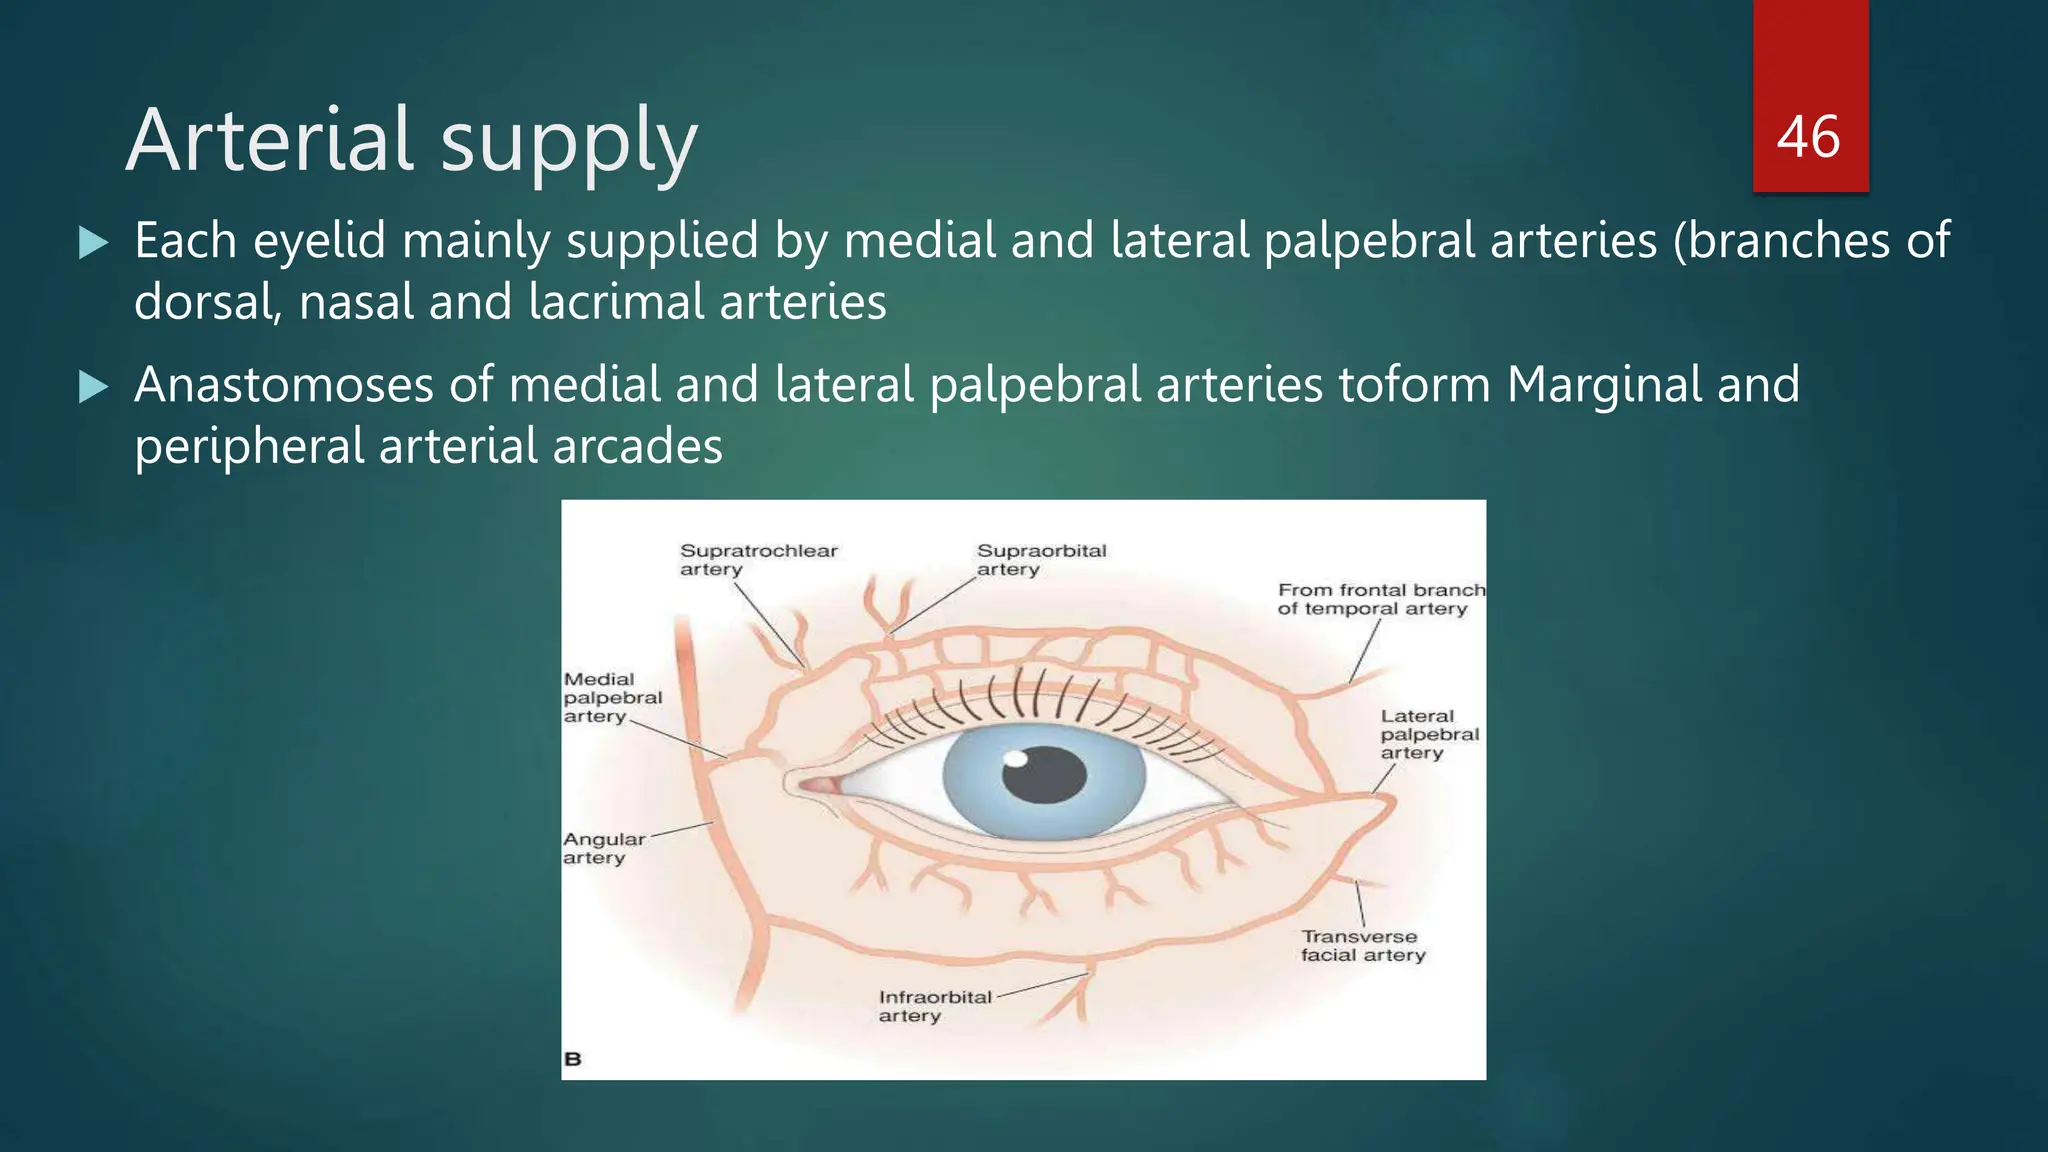
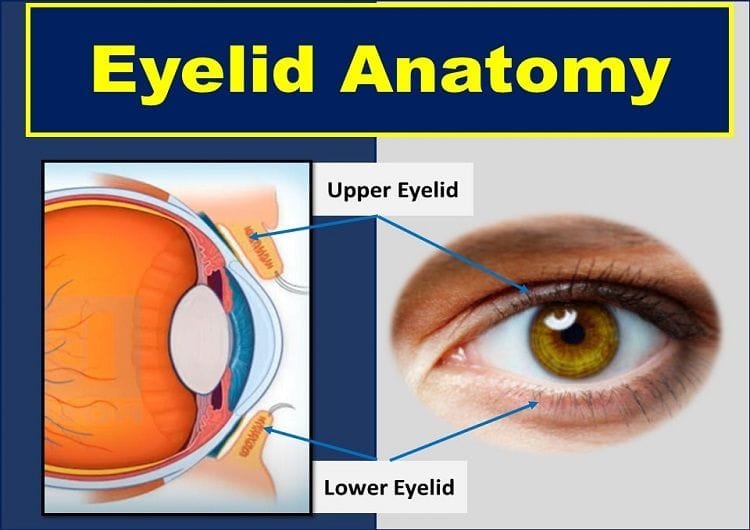
The palpebra is made up of several distinct layers stacked on top of each other. Front to back you have skin, subcutaneous tissue, the orbicularis oculi muscle, the submuscular areolar layer, and the tarsal plate with its conjunctiva. The skin here is the thinnest on your entire body, somewhere around 0.5 millimeters thick. That's why swelling shows up so dramatically when something goes wrong. The tarsal plate itself is dense connective tissue that gives the eyelid its structural shape. Embedded inside it are the meibomian glands, which produce the oily layer of your tear film. If those get blocked, you end up with a chalazion, which is basically a cyst formed from backed-up secretions. People tend to think of the eyelid as just a flap that covers the eye. It's actually a sophisticated mechanical system involving multiple muscles working in concert. The levator palpebrae superioris lifts the upper lid, innervated by the third cranial nerve. The Müller's muscle, a smooth muscle component, provides additional lift and is controlled by sympathetic fibers. When someone has a Horner's syndrome, you'll see mild ptosis because that sympathetic pathway is disrupted. I've seen cases where people came in complaining of a droopy eyelid and the real issue was a subtle Horner's from a lung apex tumor. The eyelid was the first visible sign. Ectropion and entropion are two conditions that sound similar but go in opposite directions. Ectropion is when the eyelid turns outward, exposing the conjunctiva. Entropion is when it rolls inward, causing the lashes to rub against the cornea. Entropion is more painful and tends to develop faster as a complication. In age-related involutional entropion, the lower lid retractors stretch out and the lid margin rotates. I deal with this frequently in my clinic, and the workaround is pretty straightforward: temporary adhesives to pull the lid down while you schedule surgery, but that's a bandaid. The actual fix is a tightening procedure on the lateral canthal tendon combined with repositioning the lid retractors.
One thing beginners miss when studying eyelid disorders is the difference between a hordeolum and a chalazion. A hordeolum is an acute bacterial infection, usually staphylococcal, of either the glands of Zeis or Moll at the lid margin. It's red, tender, and comes on fast. A chalazion is a chronic granulomatous inflammation of a meibomian gland deeper in the tarsal plate. It's usually painless and feels like a firm lump. The treatment for a hordeolum is warm compresses and sometimes topical antibiotics. For a chalazion that doesn't resolve, you inject triamcinolone or incise and curette. I once had a patient who kept misdiagnosing her own chalazion as a stye and putting antibiotic ointment on it for weeks. It wasn't infected. The granuloma just sat there. Warm compresses alone would have resolved it in two weeks instead of two months. Another counter-intuitive thing: blepharitis doesn't always cause obvious redness. Posterior blepharitis, which involves the meibomian glands, can present primarily with dry eye symptoms. Patients complain of burning and grittiness but the lids look relatively normal on inspection. The key is to flip the lid and look at the gland openings. If they're plugged or expressing cloudy rather than clear oil, you've got your answer. Treatment is lid hygiene with diluted baby shampoo or commercial lid wipes, plus warm compresses to liquefy the secretions. The compress step is where most people fail because they don't hold the heat long enough. You need at least ten minutes at a temperature that's comfortably warm, not scalding. Five minutes just isn't cutting it. Ptosis assessment is another area where shortcuts lead to mistakes. You need to measure the levator function by asking the patient to look down, holding the forehead still to eliminate frontalis compensation, then having them look up and measuring the margin-to-pupil distance. If levator function is poor, less than four millimeters of excursion, you're dealing with a true levator deficiency. If it's good but the lid still drops, the culprit might be aponeurotic dehiscence or a frontalis overaction issue. I had a case where a patient was referred for cosmetic ptosis repair but the real problem was thyroid eye disease causing lid retraction on the contralateral side. The apparent ptosis was just the other eye looking higher than it should. Fixing the "droopy" lid would have made the asymmetry worse. Always check for thyroid history and do a thorough slit lamp exam before booking any surgery.
Cellulitis of the eyelid is split into preseptal and orbital types, and the distinction matters because orbital cellulitis is a genuine emergency. Preseptal cellulitis involves the tissues anterior to the orbital septum. It's painful and swollen but vision is normal and eye movements are full. Orbital cellulitis extends behind the septum and causes proptosis, pain with eye movement, decreased vision, and restricted extraocular movements. A CT scan with contrast is the standard diagnostic tool here. I've seen instances where a dental abscess tracked upward through the maxillary sinus and presented as what looked like a routine stye initially. By the time the patient reported double vision and fever, the infection had breached the septum. The turnaround from minor complaint to orbital cellulitis can happen in under forty-eight hours. Neoplasms of the eyelid are another category worth understanding practically. Basal cell carcinoma accounts for roughly ninety percent of malignant eyelid tumors. It typically appears as a pearly papule with telangiectasias on the lower lid or medial canthus. The danger isn't metastasis, it's local destruction. These things eat into cartilage and bone if left alone. Sebaceous cell carcinoma is rarer but more deadly, and it loves to mimic chronic blepharitis or a recurrent chalazion. If a patient has a "chalazion" that comes back in the same spot after curettage, you biopsy it. I learned that lesson the hard way. Missed sebaceous carcinoma once because it presented exactly like a stubborn chalazion on the upper lid. By the time I caught it, there was pagetoid spread across the conjunctiva. Survival rates drop significantly once that happens. Trauma to the eyelid follows predictable patterns but the complications can be unpredictable. A laceration through the punctum requires repair of the lacrimal drainage system or the patient will have epiphora for life. You need to probe the system before closing. A simple skin laceration near the eye looks scarier than it is because the area is vascular and bleeds a lot, but healing is generally excellent. The tricky part is assessing whether the underlying structures are involved. Check for globe penetration, check the canthal tendons for rupture, and assess the levator if it's the upper lid. I always use fluorescein staining after any significant trauma to rule out corneal injury. Patients will tell you their eye feels fine until they squint in bright light and realize they have a scratch.
Get the Full Details
Mydriatics and cycloplegics used in eye exams can cause reflex blepharospasm in sensitive patients. It's not an allergic reaction, it's just the eye trying to protect itself from the light. Telling the patient it's normal and asking them to keep the lid open gently usually resolves it within a minute. Forcing it causes more spasm. This is one of those small clinical pearls that nobody writes about in textbooks but matters every single day. If you're studying this material for clinical purposes, focus on the anatomical relationships and learn to correlate surface findings with deeper structures. The eyelid is thin enough that pathology in one layer often becomes visible in another. A subconjunctival mass might show through as a discoloration on the skin. An abscess in the subcutaneous layer will point toward the skin surface. Understanding which layer is involved tells you what's likely going on and what approach to take. Surgery through the skin versus through the conjunctiva gives you access to different planes and different complications. There's no shortcut around practicing lid flips and getting comfortable with the anatomy under direct visualization. Reading about the tarsal plate is one thing, feeling it between your forceps during a chalazion procedure is another. The resistance, the texture, the way the gland orifices look when expressed. Those tactile details are what separate people who can diagnose from people who can treat.