What You Need to Know Before You Start
Seronegative rheumatoid arthritis is one of those conditions where the textbook definition doesn't match what you actually see in the clinic. I've been working with autoimmune rheumatic conditions for long enough to know that "seronegative" doesn't mean "mild." It means the lab tests came back negative for rheumatoid factor and anti-CCP antibodies, but the disease is doing the same damage underneath. People often think that negative bloodwork clears them. It doesn't. I want to walk through how this actually presents, how it's diagnosed, what the treatment landscape looks like, and where most people get stuck. This isn't a quick summary. It's a working guide. The core mystery here is that roughly 20 to 30 percent of people diagnosed with rheumatoid arthritis will test negative on both RF and anti-CCP. That's not a small number. The reason this matters is that seronegative RA tends to follow a different clinical trajectory. It's frequently more inflammatory in the peripheral joints early on, responds differently to certain medications, and can be harder to catch before structural damage occurs because the antibody markers that normally trigger suspicion aren't there.
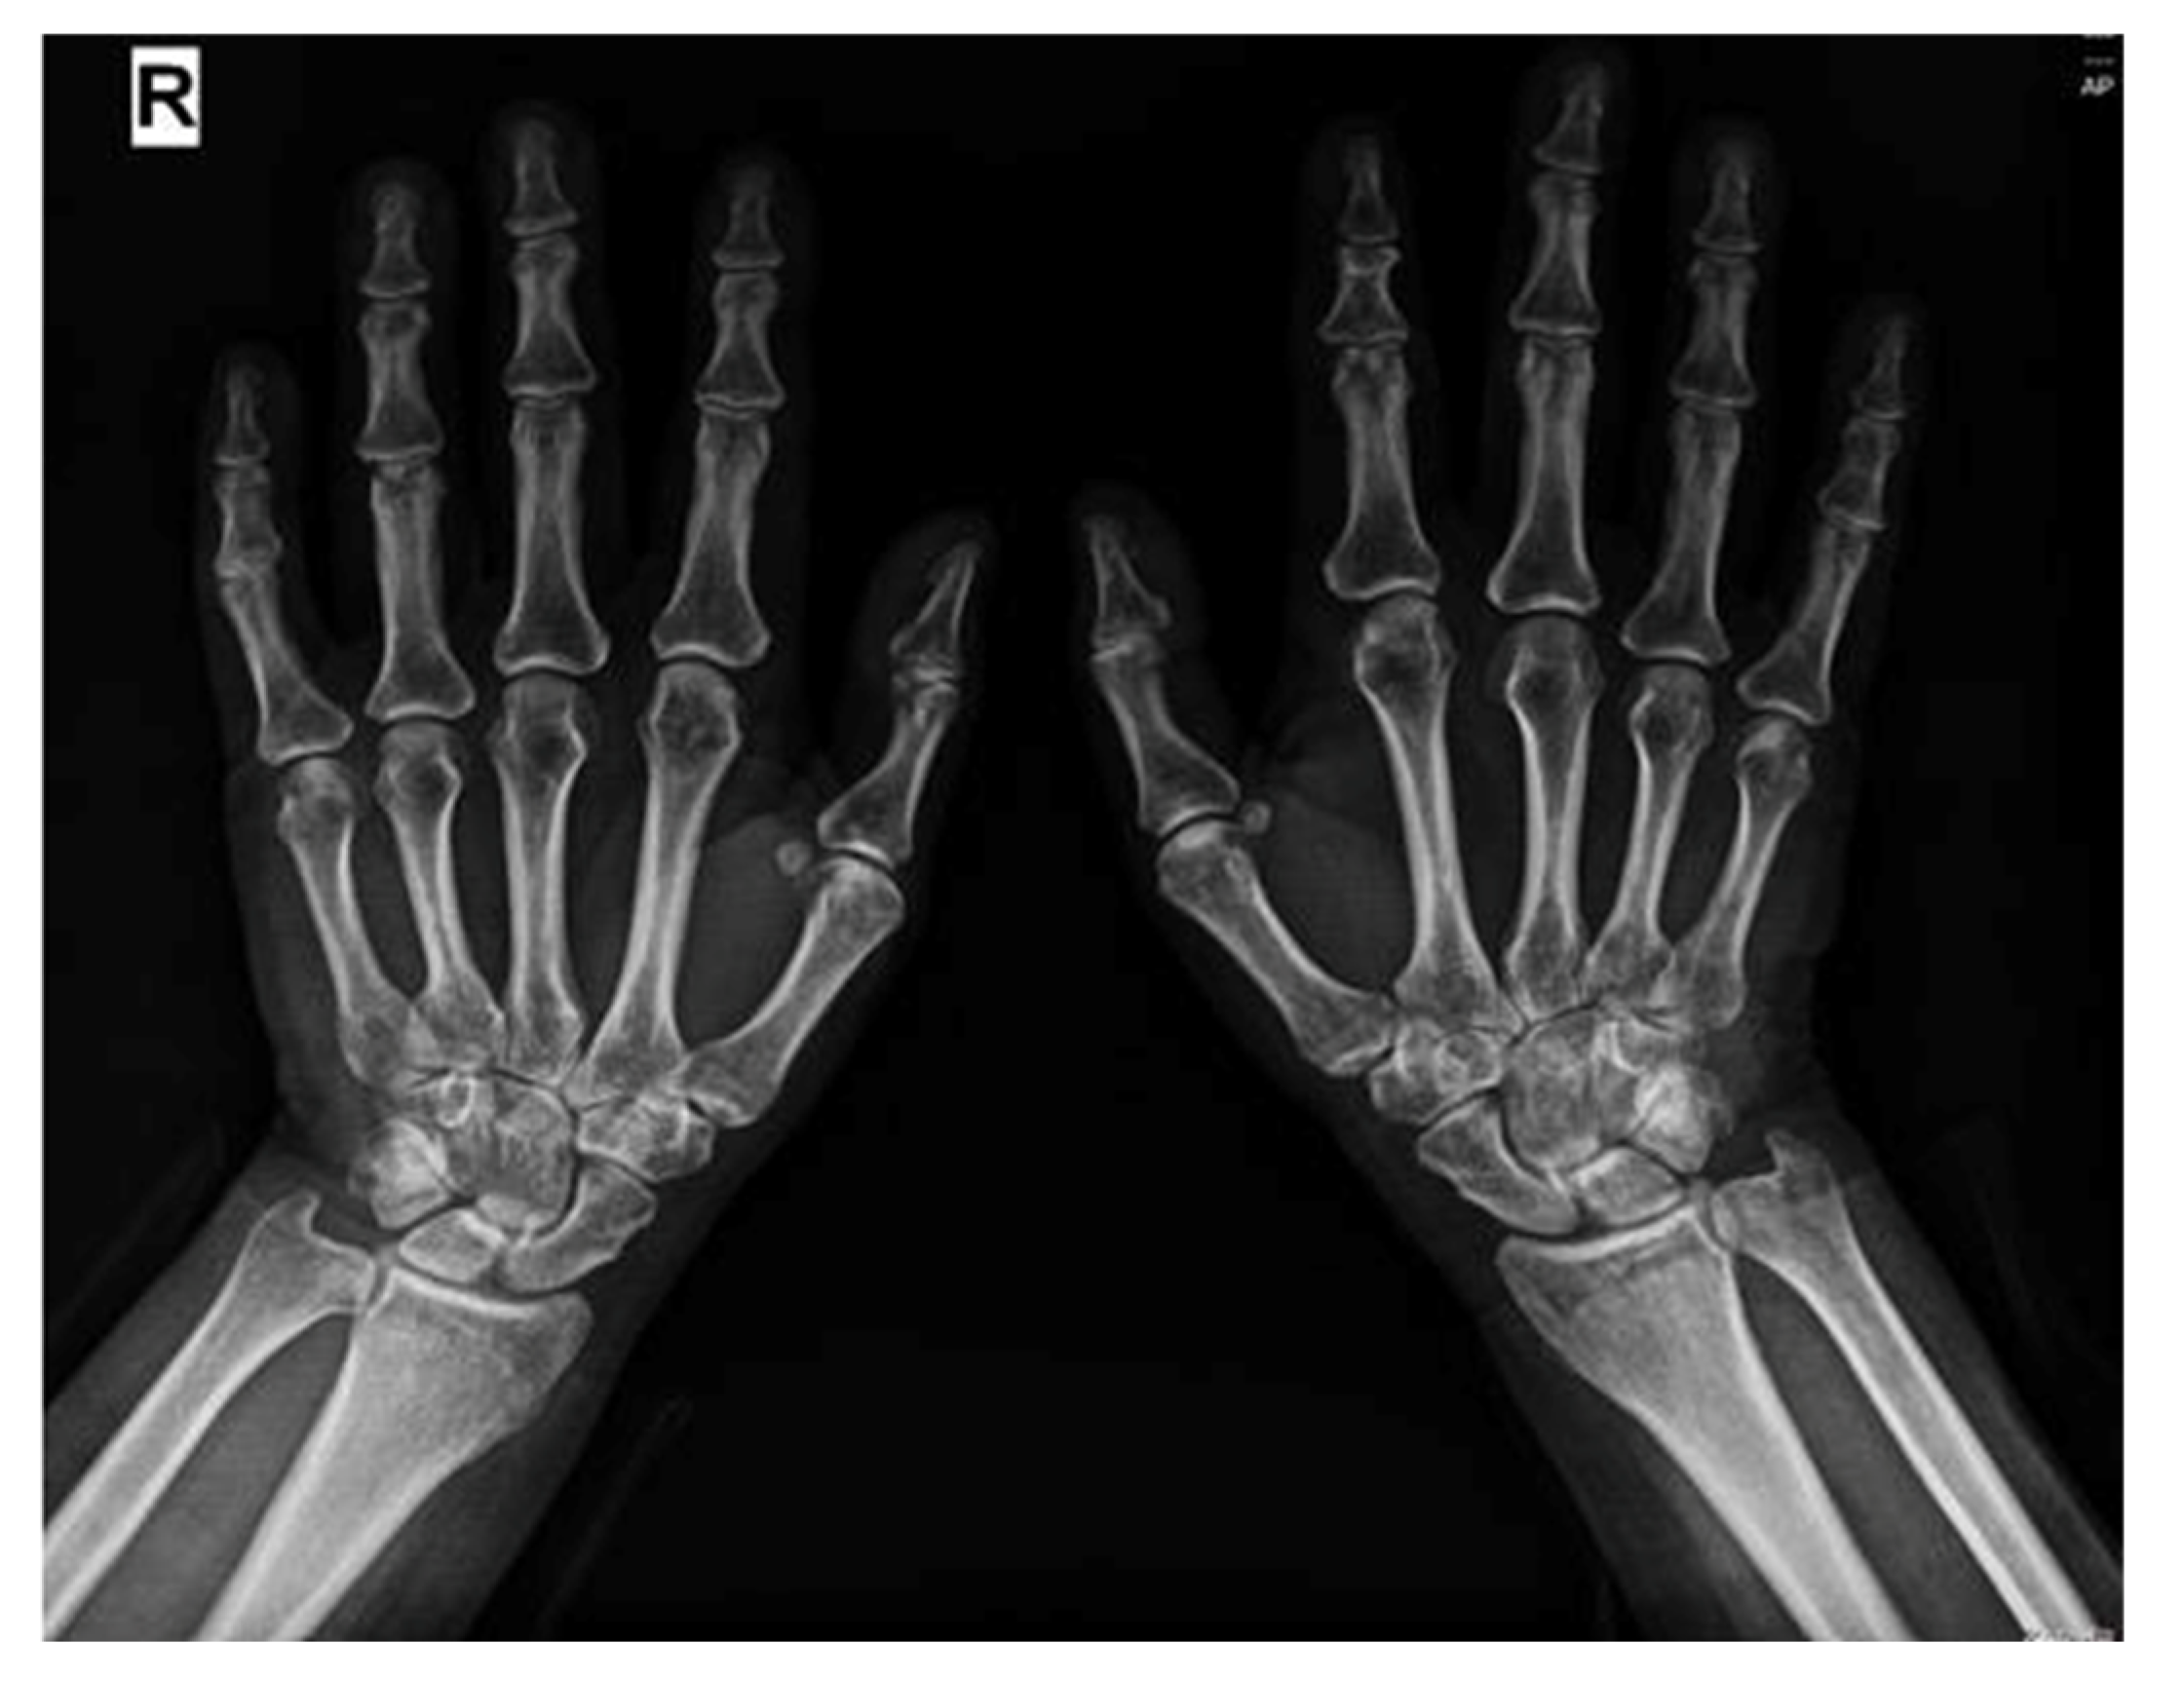
When I see a patient who's been told their bloodwork is normal and therefore their joint pain is probably just wear-and-tear, I take a closer look at the pattern. Seronegative RA often shows up with symmetric involvement of the small joints in the hands and feet, morning stiffness lasting longer than 30 to 60 minutes, and systemic symptoms like fatigue that don't correlate with how much the person slept. These are the clues. The labs just don't provide the usual confirmation. One thing that catches people off guard is the role of ultrasound and MRI in diagnosing seronegative disease. Standard X-rays are often completely normal in the early stages. I had a patient last year who'd been dismissed for eight months across three different clinics because her X-rays were clean and her RF was negative. She could barely grip a coffee mug in the morning. We ran a musculoskeletal ultrasound and found active synovitis in her metacarpophalangeal joints that was completely invisible on X-ray. That image change was the tipping point that got her started on the right treatment. The lesson here is straightforward. If your inflammatory markers are elevated or your clinical picture fits and your antibody tests are negative, push for advanced imaging. Don't accept "we'll watch and wait" as a final answer.
How Diagnosis Actually Works in Practice
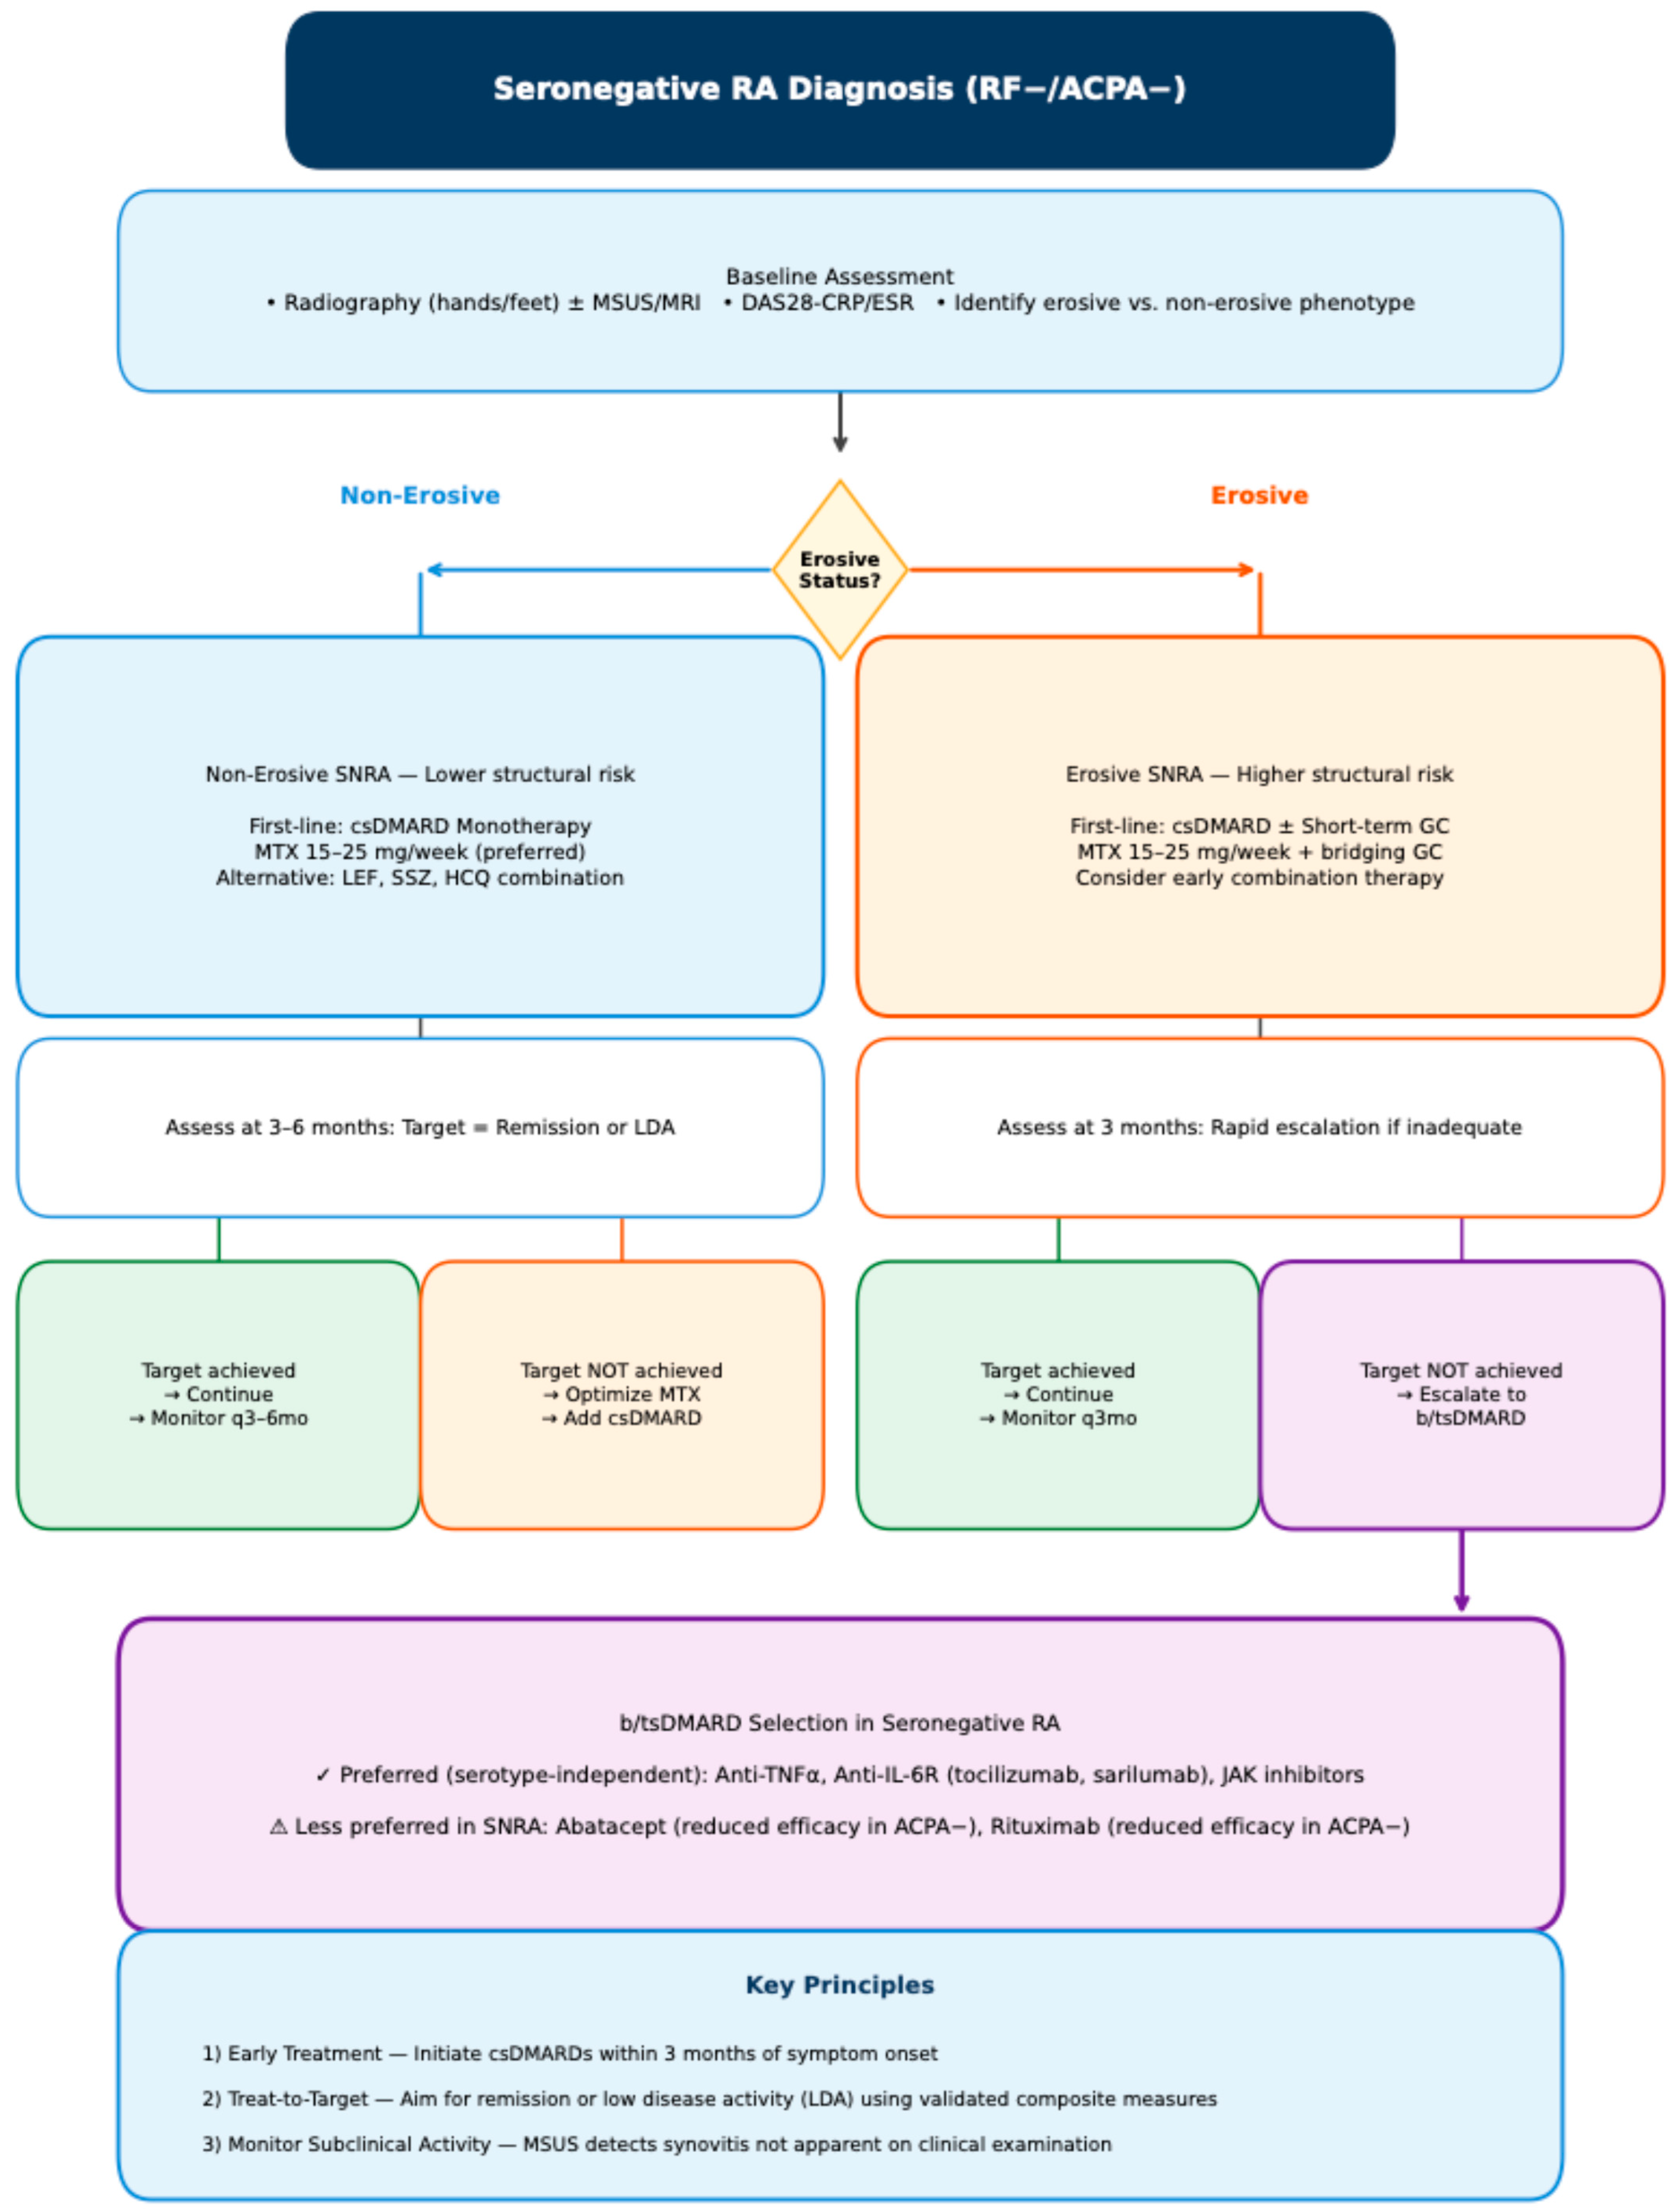
The 2010 ACR/EULAR classification criteria include a scoring system that doesn't rely solely on serology. You accumulate points based on joint involvement, acute phase reactants like CRP and ESR, duration of symptoms, and the presence or absence of antibodies. A score of six or above qualifies for a classification of definite RA regardless of serostatus. Most clinicians understand this, but not all of them apply it rigorously, especially when they're used to relying on the old binary of positive or negative. There's another nuance that doesn't get enough attention. Some patients who test seronegative for RF and anti-CCP will eventually convert to seropositive over time. A 2018 study in Annals of the Rheumatic Diseases found that about 10 to 15 percent of initially seronegative patients developed positive antibodies within five years of diagnosis. This means an initial negative workup doesn't close the book. It warrants follow-up testing, especially if symptoms persist or worsen. When I manage these cases, I track anti-CCP and RF at baseline and again at six and twelve months. I also monitor CRP and ESR quarterly. If those inflammatory markers are consistently elevated alongside clinical symptoms, I'm treating the disease even when the serology stays negative. The alternative is waiting until someone's joints are visibly deformed, and by that point the window for preventing permanent damage has narrowed significantly.
Get the Full Details
Treatment Approaches That Actually Work
Disease-modifying antirheumatic drugs remain the cornerstone. Methotrexate is still first-line for the vast majority of patients, seronegative or not. The difference with seronegative RA is that some studies suggest a slightly lower response rate to methotrexate monotherapy compared to seropositive patients. That doesn't mean you skip it. It means you need a clear escalation plan from day one. If methotrexate isn't controlling things after twelve to sixteen weeks, the next step typically involves adding a biologic or targeting synthetic DMARD. TNF inhibitors like adalimumab, etanercept, and infliximab work well for many seronegative patients. Janus kinase inhibitors like tofacitinib and baricitinib are oral options that have shown solid efficacy in this subgroup. I've seen patients who didn't respond well to one TNF inhibitor switch to a different mechanism and get meaningful relief. It's a process of elimination, but it's a process. Ahead of starting any biologic, you need screening for latent tuberculosis and hepatitis B. This is non-negotiable and sometimes gets rushed. I once had a patient whose screening for TB was deferred because the clinic was backed up. He started adalimumab two weeks later and developed active pulmonary TB three months into treatment. It was entirely preventable. Budget the time for proper pre-biologic workup. It saves you from a much worse problem down the line.
NSAIDs and low-dose corticosteroids can help bridge the gap while DMARDs take effect, but they don't modify the disease course. Using them as a long-term solution without a proper DMARD plan is a common mistake I see. Steroid dependency in particular creates a false sense of control. The inflammation is quiet, but the underlying autoimmune process is still running.
Monitoring and Long-Term Management
Monitoring seronegative RA isn't fundamentally different from seropositive RA, but the absence of antibody titers as a tracking tool means you lean more heavily on clinical assessment and inflammatory markers. The DAS28 score, which factors in tender and swollen joint counts, ESR or CRP, and patient global assessment, is the standard tool. I also use ultrasound assessments periodically to check for subclinical synovitis that the patient might not feel yet but that's still causing damage. Lifestyle factors matter more than most patients realize. Smoking is strongly linked to both the development and severity of RA, and the association is particularly pronounced with seropositive disease, but it's relevant across the board. Weight management reduces mechanical stress on affected joints and lowers systemic inflammation. Sleep disruption is both a symptom and a exacerbating factor, creating a cycle that's hard to break without addressing the underlying inflammation. There's also a mental health component that gets minimized. Living with an unpredictable, progressive condition takes a toll. Depression and anxiety are more common in RA patients than in the general population, and untreated mood disorders negatively impact treatment adherence and pain perception. This isn't ancillary care. It's part of the treatment plan.
Where Things Get Complicated
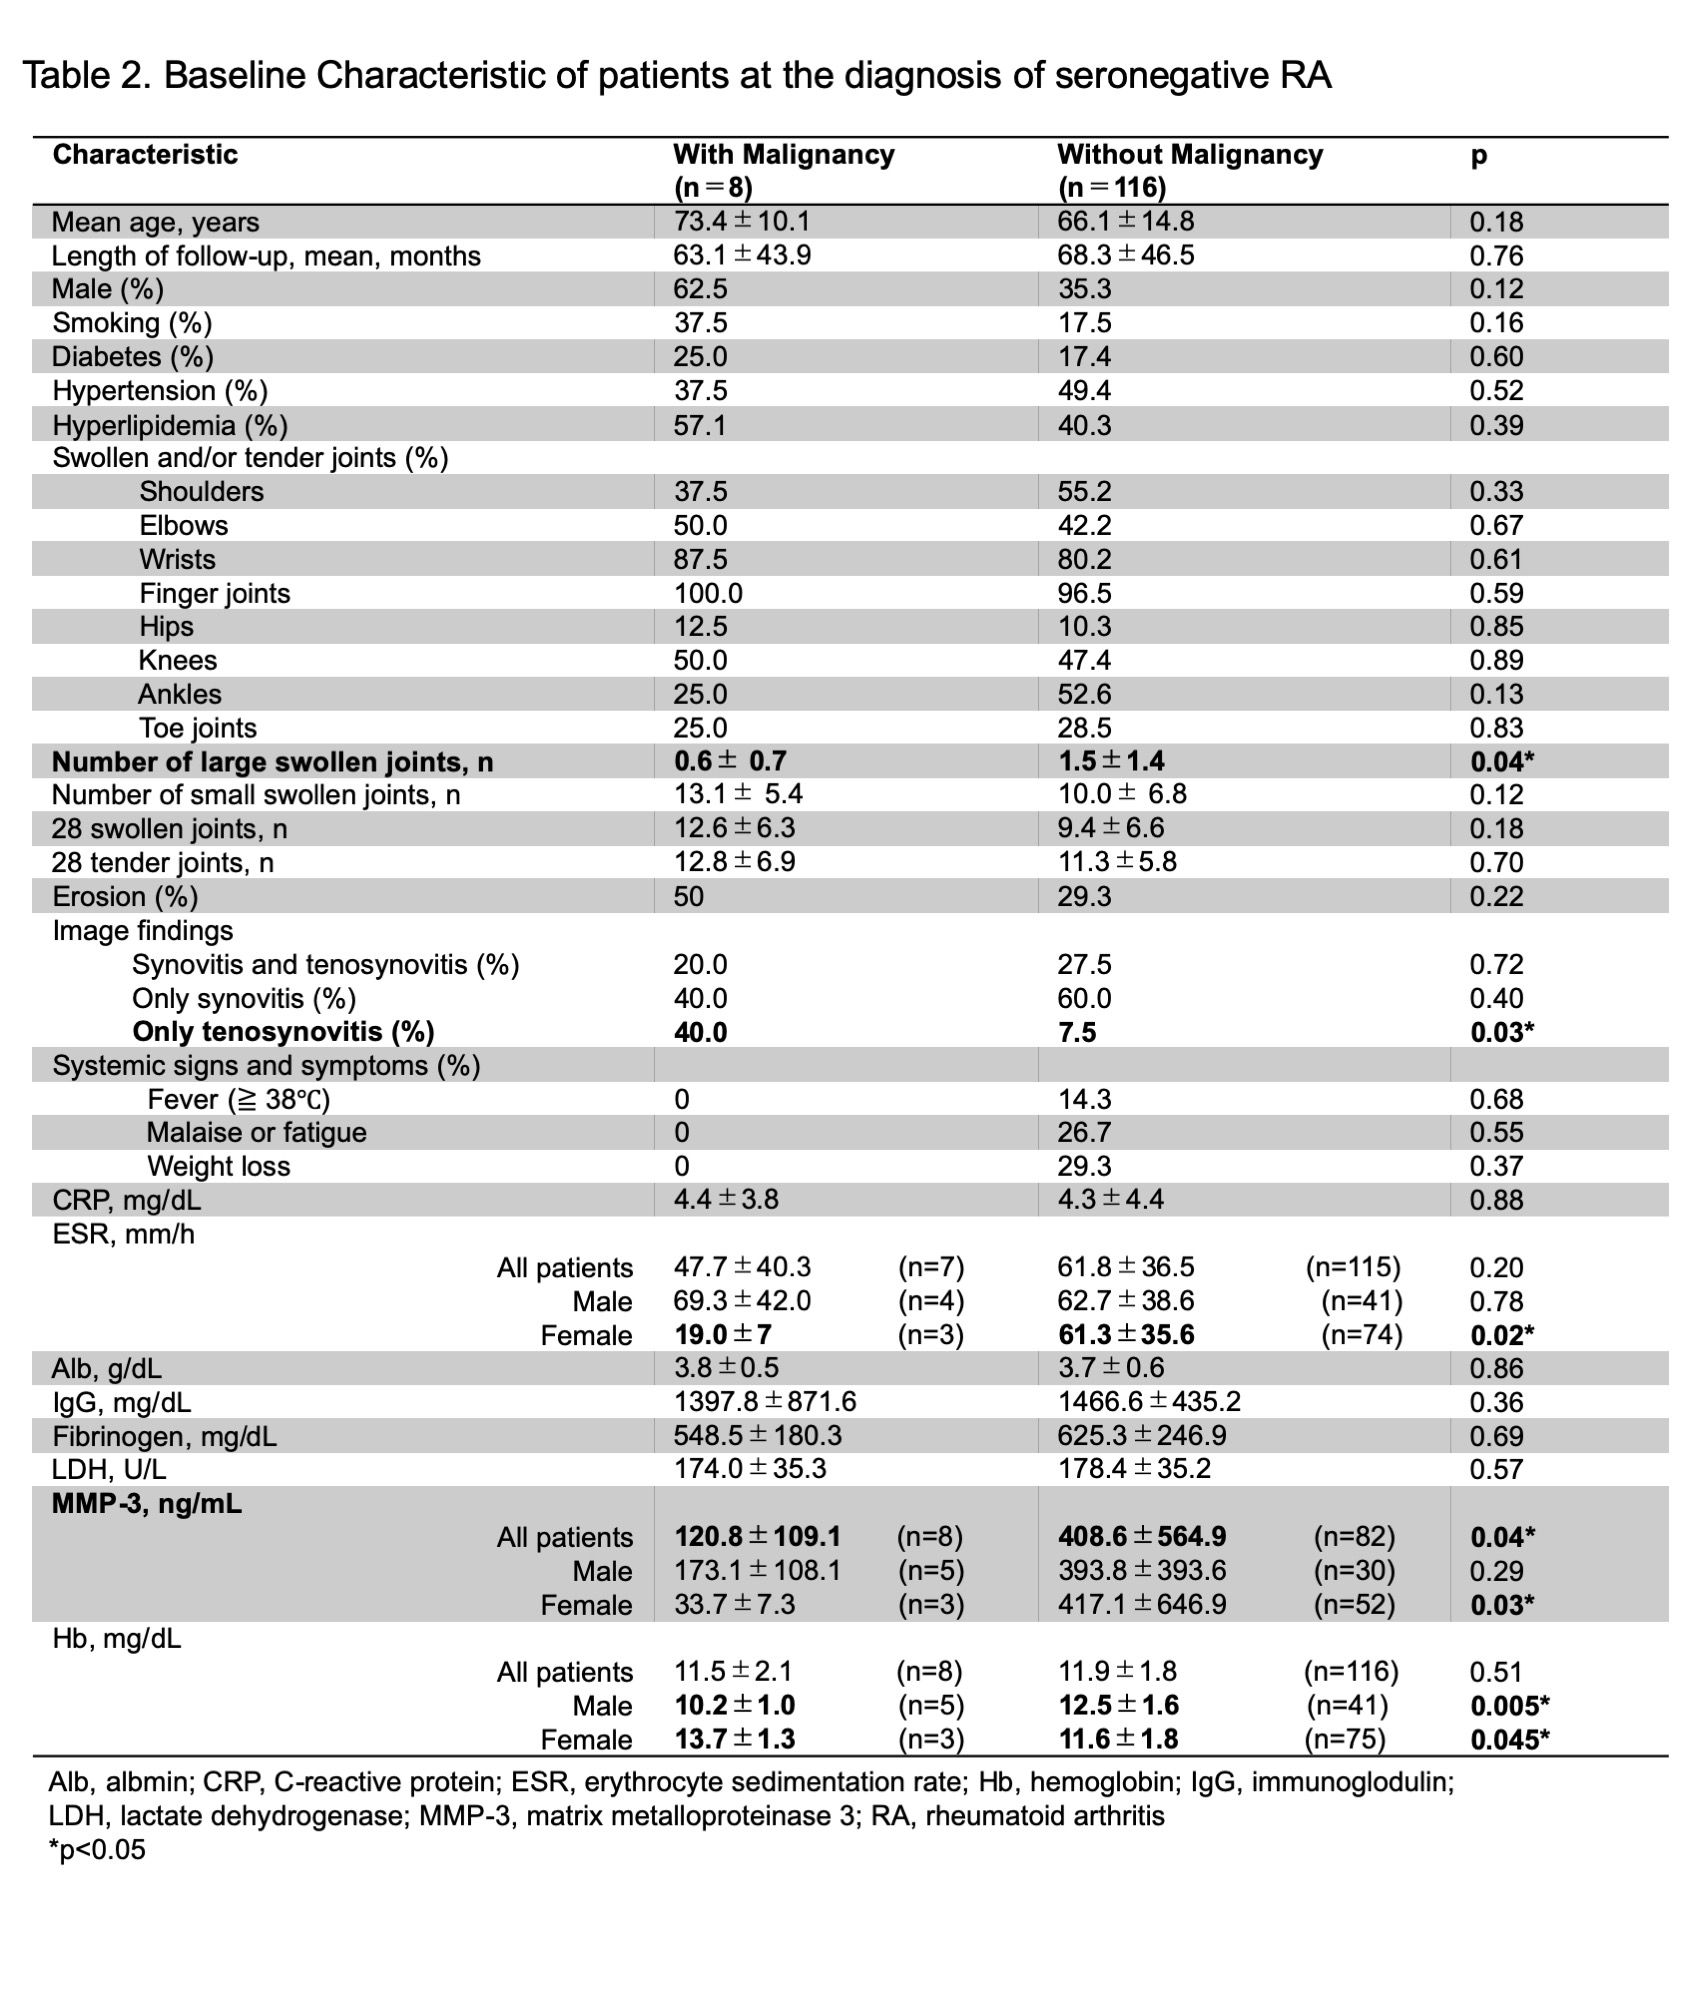
Not every case of seronegative inflammatory arthritis is RA. Psoriatic arthritis, ankylosing spondylitis, reactive arthritis, and even undifferentiated connective tissue disease can present similarly. The overlap is substantial enough that misdiagnosis happens regularly. I've treated patients who were labeled as seronegative RA for years before a rheumatologist recognized enthesitis patterns consistent with psoriatic arthritis. The treatment implications are different. PsA responds better to certain biologics like IL-17 inhibitors, which aren't typically first-line for RA. Another complication is the possibility of overlapping conditions. Some patients develop features of both RA and another autoimmune disease. This is more common than you'd expect and requires careful differential diagnosis. I've seen patients with joint symptoms, negative RF and anti-CCP, positive ANA, and a mixed clinical picture that didn't fit neatly into one category. In those cases, treating the dominant feature and monitoring for evolution is usually the most practical approach. There's also the question of who gets referred and who doesn't. People with seronegative RA are disproportionately likely to be told their symptoms are stress-related or age-related, particularly women and younger patients. A study published in Rheumatology in 2020 found that women with seronegative RA experienced significantly longer diagnostic delays compared to men with the same profile. This isn't just an inconvenience. Every month of untreated inflammation increases the risk of joint damage.
What the Research Says Now
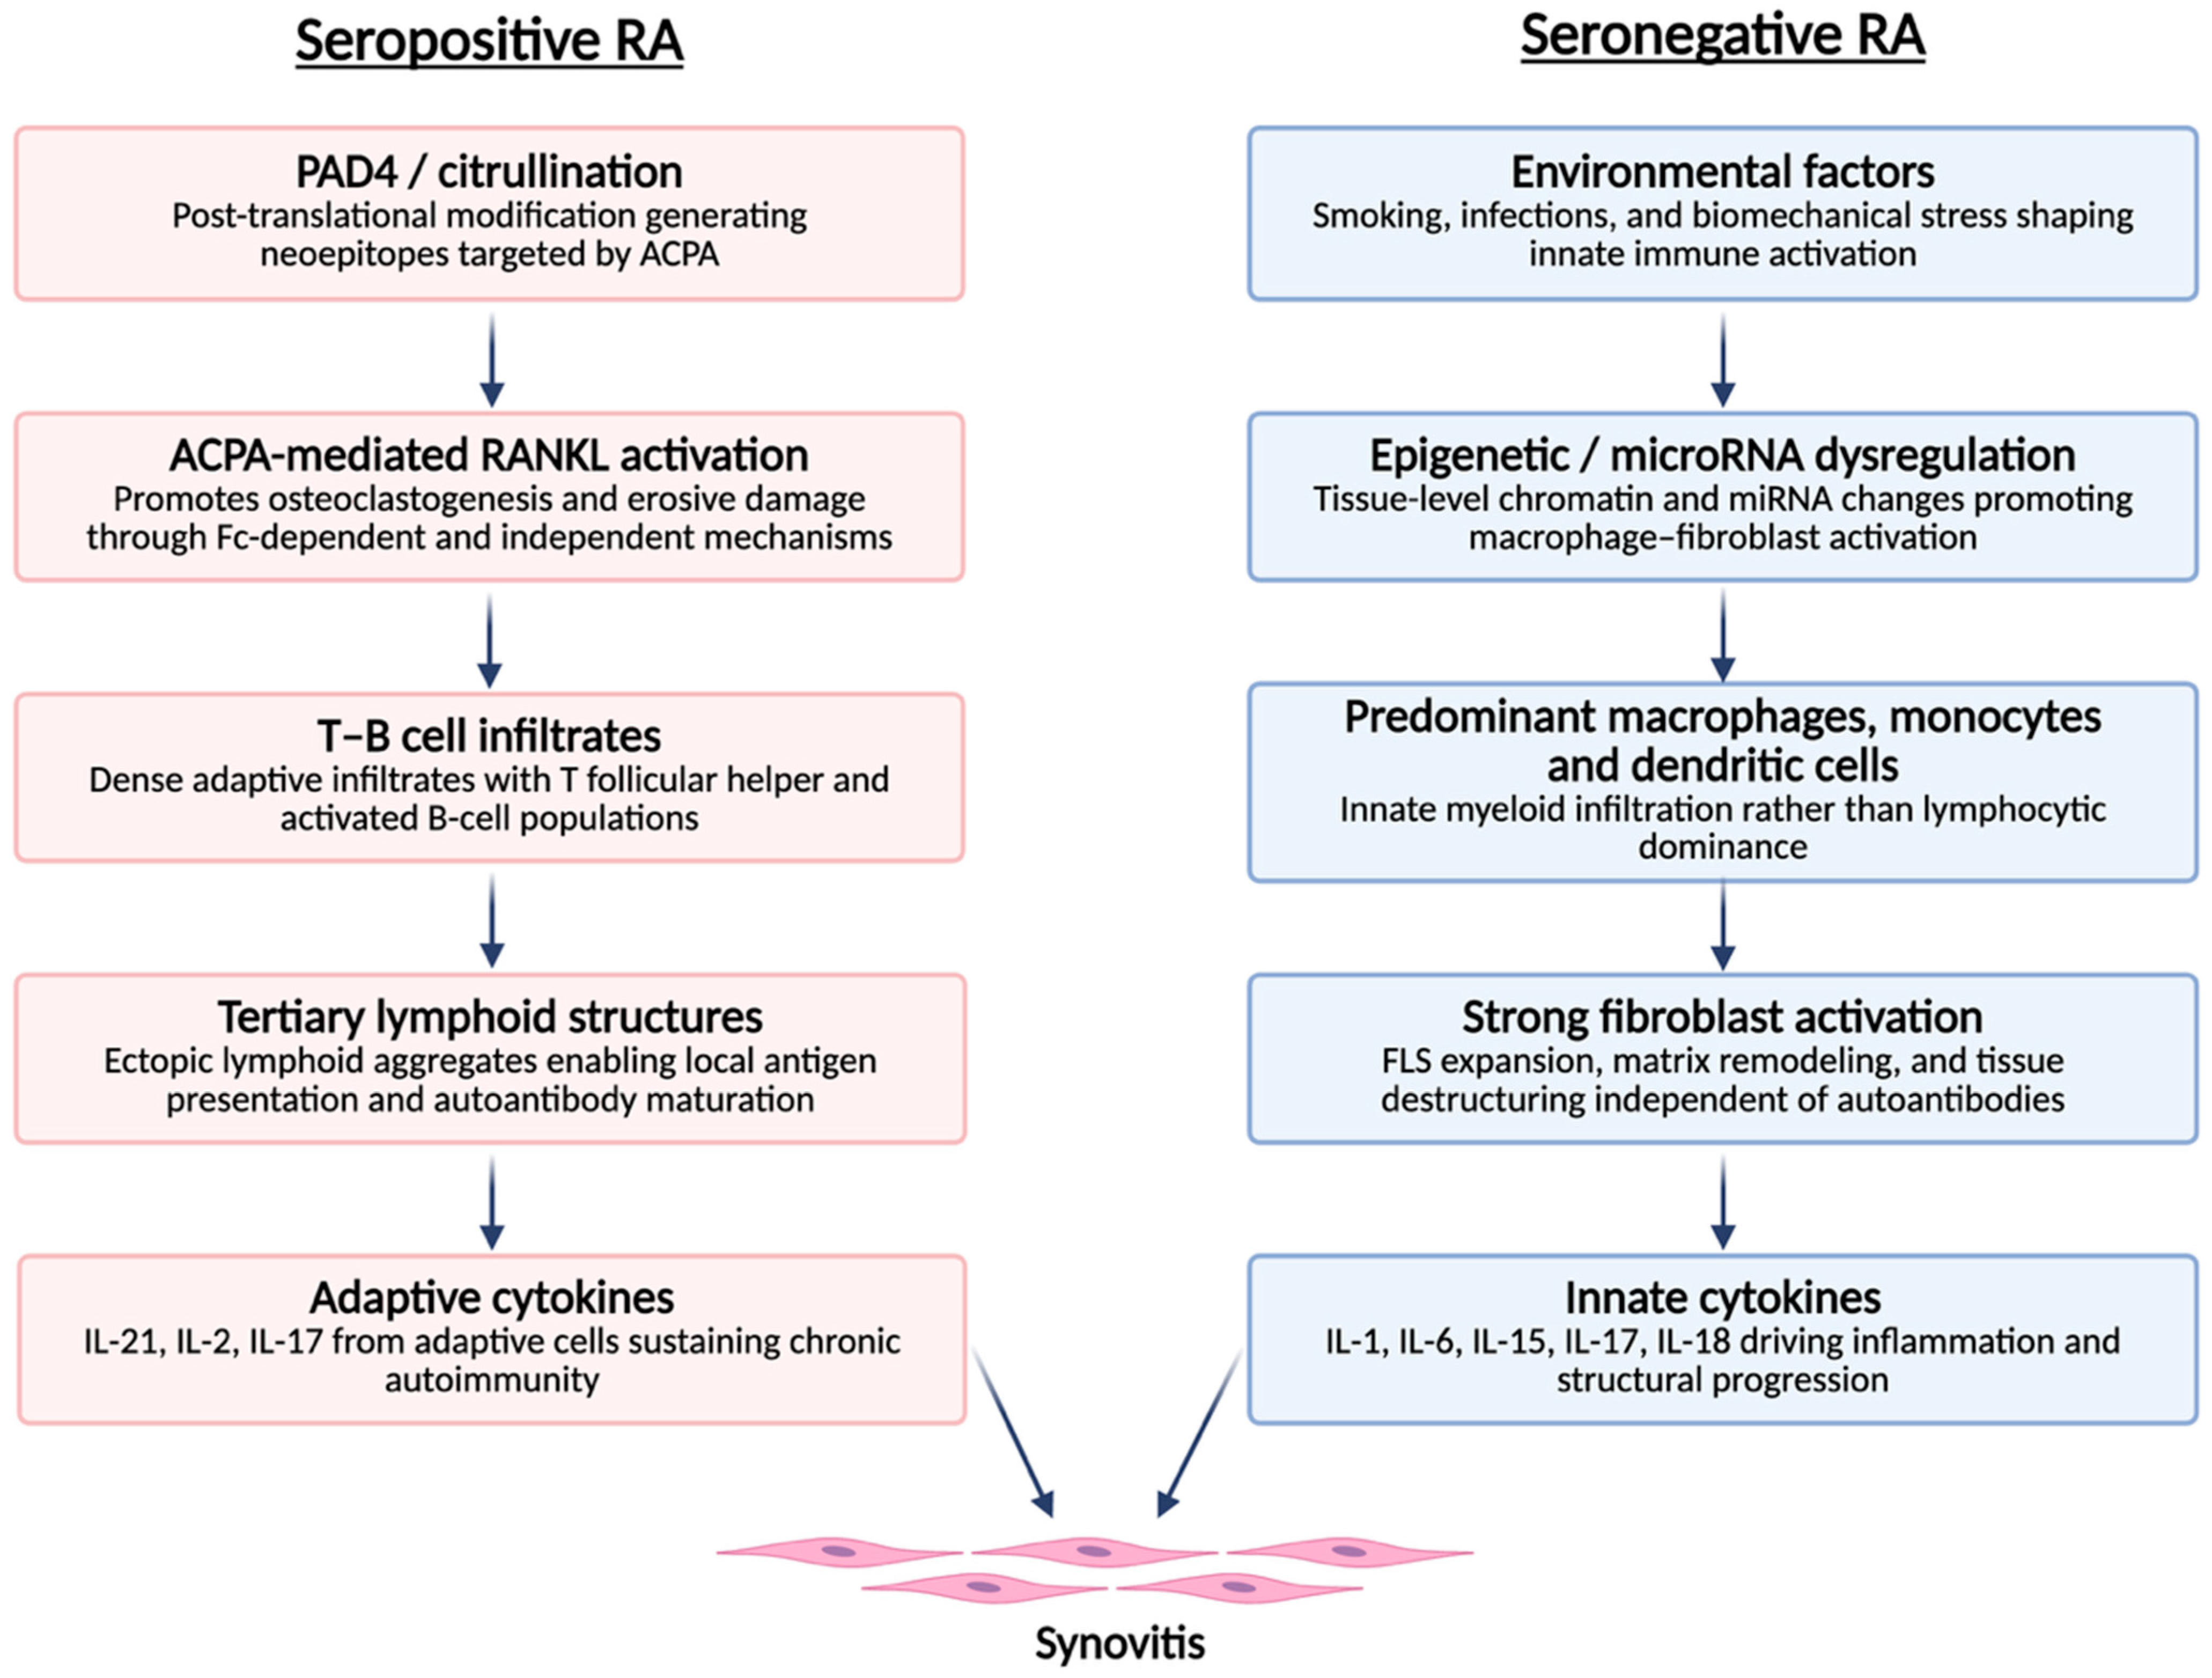
Recent work has looked at whether seronegative RA is truly a single entity or a collection of different conditions grouped together by exclusion. Some researchers argue that "seronegative RA" is a useful clinical label but a questionable biological category. Imaging studies show that a subset of seronegative patients have imaging and clinical features distinct from seropositive patients, while another subset looks almost identical except for the antibody results. New biomarkers are being investigated, including cytokine profiles and genetic markers like HLA-DRB1 shared epitope variants, which can appear in seronegative patients and carry prognostic significance. These aren't routine tests yet, but they're moving toward clinical relevance. If you're following this condition, keeping an eye on publications from major rheumatology journals will give you a sense of where things are heading. The take-away for anyone dealing with this is to find a rheumatologist who treats the patient, not just the lab result. Someone who understands that seronegative RA is real, that it can be aggressive, and that the absence of antibodies is a diagnostic challenge, not a diagnostic endpoint. The people who get the best outcomes are the ones who are engaged, monitored regularly, and willing to adjust their treatment plan as needed rather than settling for a suboptimal regimen because the diagnosis feels uncertain.