Where The Shoulder Meets Its Limits
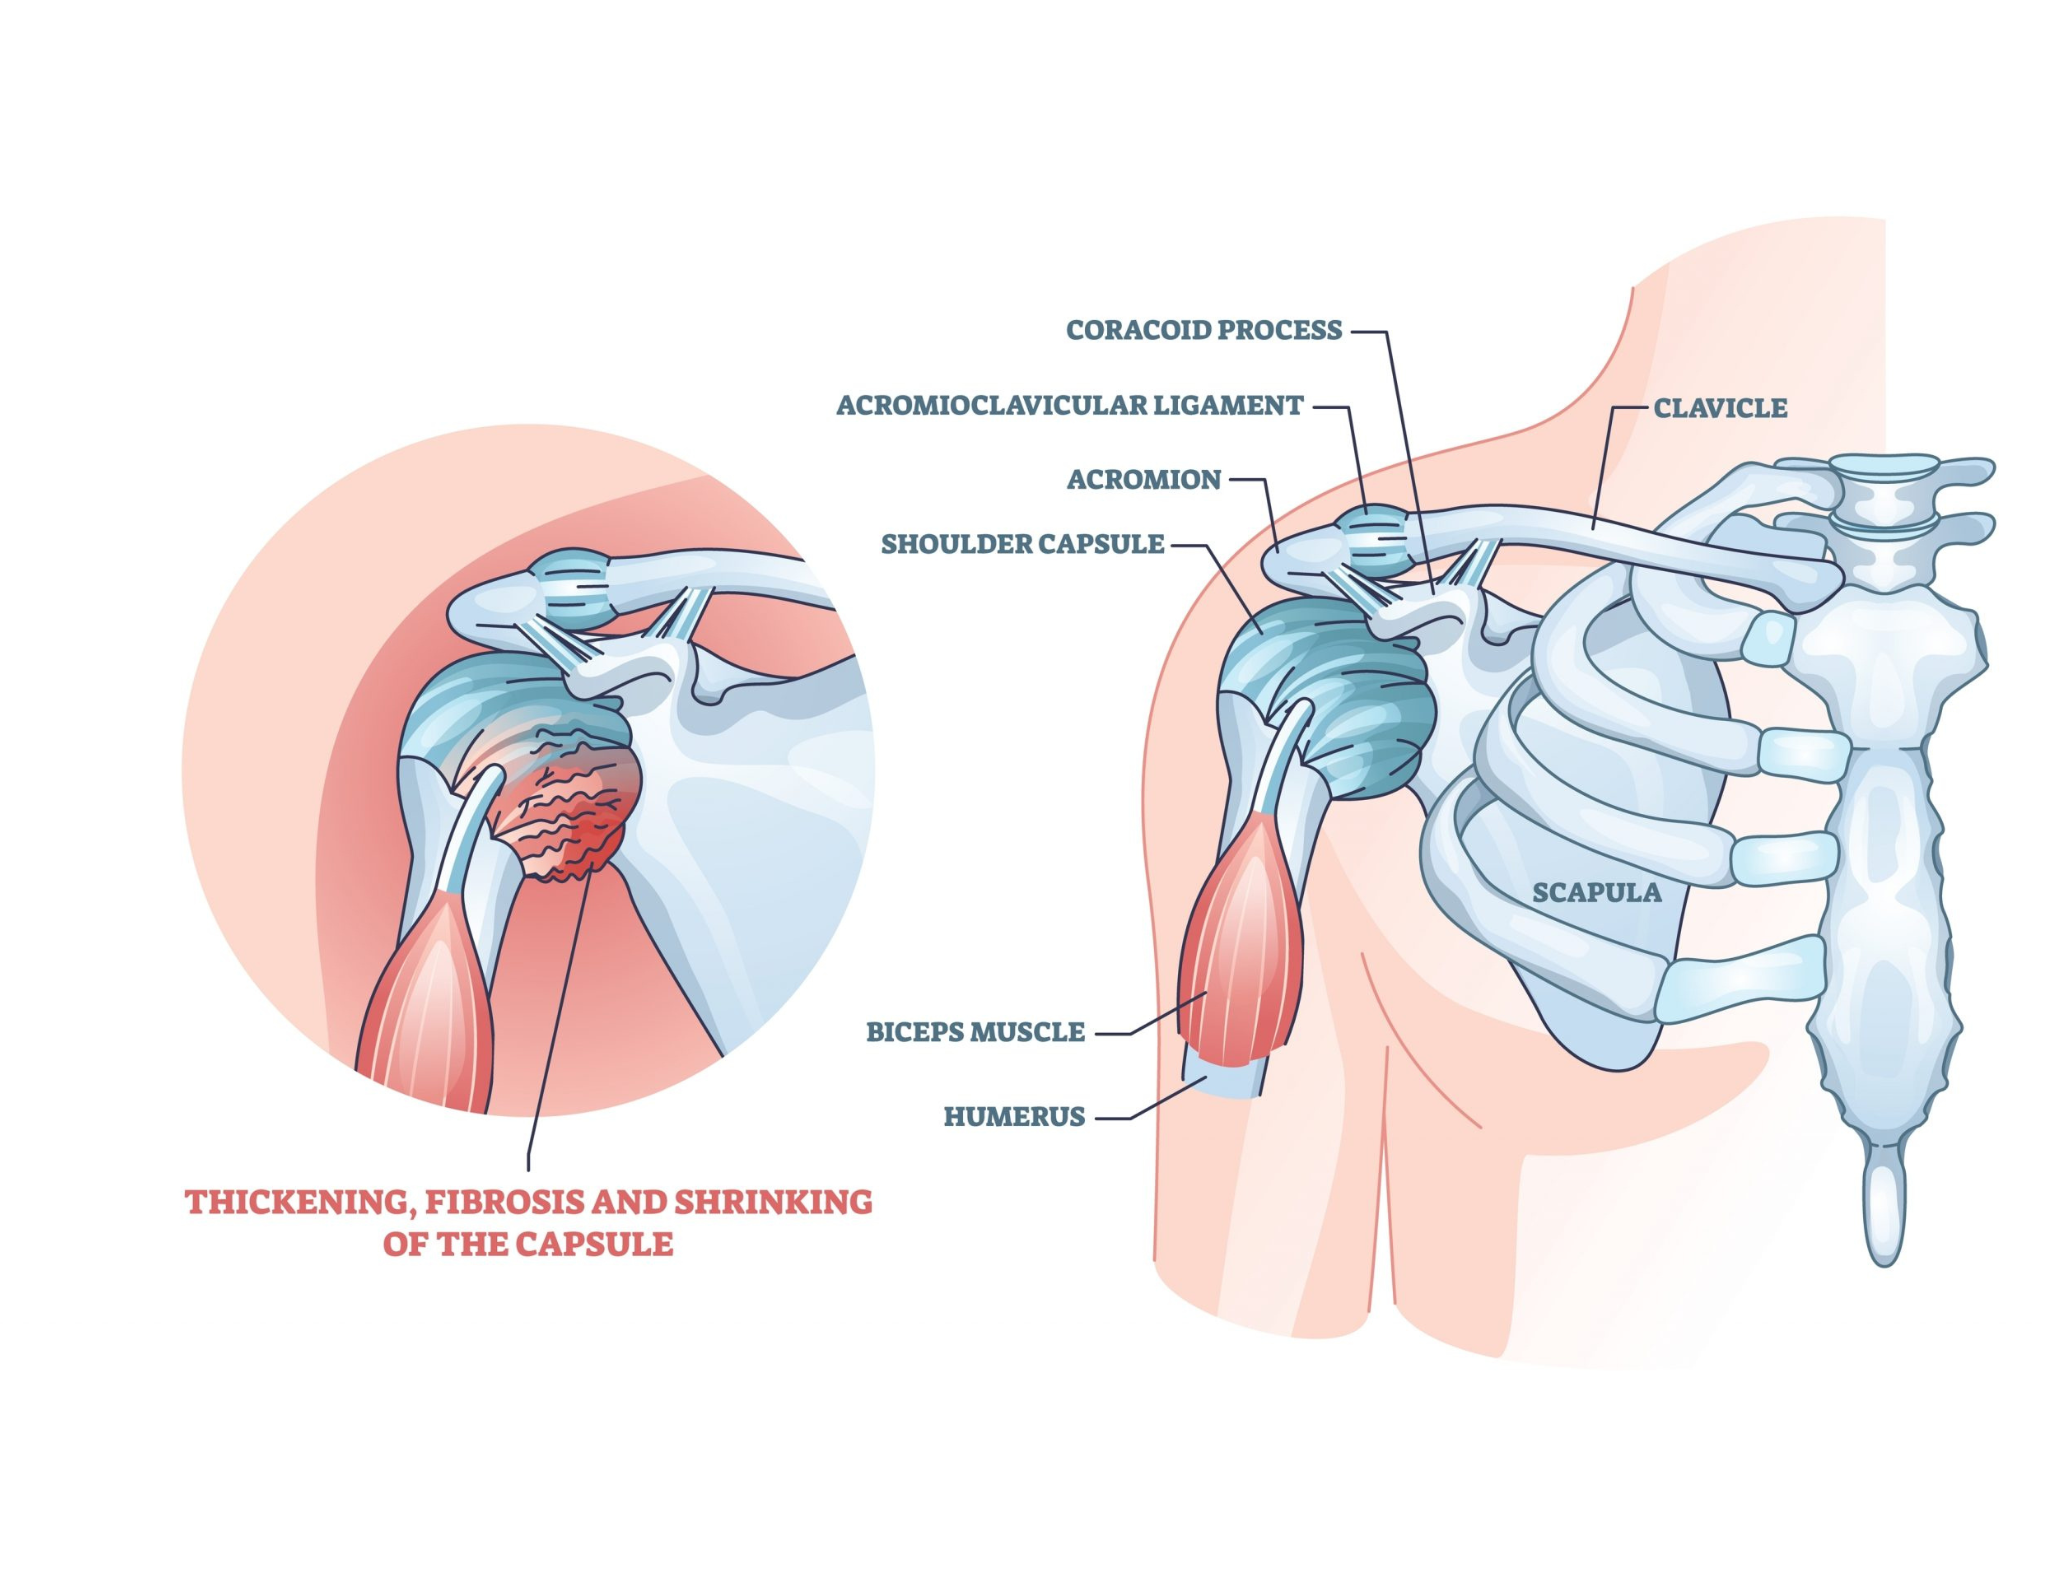
The acromion process is a bony projection off the scapula that forms the highest point of the shoulder. It articulates with the clavicle at the acromioclavicular joint and serves as an attachment point for the deltoid muscle and the coracoacromial ligament. That's the textbook answer. The practical answer is that it's one of the most clinically significant structures in the upper body because of what sits underneath it. I spent years working with shoulder pathologies in a sports medicine clinic, and the acromion consistently showed up as the common denominator in cases that shouldn't have been so difficult to diagnose. People come in with what they think is a rotator cuff issue, and half the time the problem isn't the tendon at all—it's the space beneath the acromion being too small for what's trying to pass through it.
The Hidden Structure Of Strength Uncovering The Acromion Process Of The Scapula
What makes this structure interesting isn't the bone itself. It's the subacromial space, the roughly one-centimeter gap between the acromion and the humeral head. Inside that space sit the supraspinatus tendon, the subscapularis, the long head of the biceps tendon, and the subacromial bursa. When that space narrows even slightly, everything gets compressed during overhead motion. This is subacromial impingement, and it's one of the most common causes of shoulder pain in adults. The shape of the acromion matters more than most people realize. Bigos and Jobe classified acromion shapes into three types back in 1986: Type I is flat, Type II is curved, and Type III is hooked. Their research showed that Type III acromions had a significantly higher association with rotator cuff tears. A flat acromion leaves more room under it. A hooked one creates a literal shelf that grinds into the tendons every time you raise your arm. This isn't theory—I've seen MRIs where the space was barely two millimeters on a hooked acromion versus eight or nine millimeters on a flat one. The difference is catastrophic for the supraspinatus. Here's something counter-intuitive that most beginners miss: the acromion isn't rigid. It moves. The acromioclavicular joint allows the acromion to rotate and translate during shoulder movement. During arm elevation, the acromion actually rolls upward and tilts slightly, which changes the geometry of the subacromial space in real time. Most people treat the acromion as a fixed hook, but it's a dynamic structure. This is why some people with a seemingly narrow space on imaging never develop symptoms—their acromion moves adequately. And some people with a "normal" looking acromion on X-ray still have impingement because their AC joint doesn't move properly.
I dealt with a case a few years back that illustrates this perfectly. A client came in with chronic shoulder pain after starting overhead pressing in the gym. Standard assessment showed full range of motion, negative Neer and Hawkins-Kennedy impingement tests, and an MRI that read as "mild acromial thickening, otherwise unremarkable." The standard protocol would have been rest and anti-inflammatories. But the pain wasn't going away, and the imaging didn't tell the whole story. What I noticed was that during active movement, the acromion didn't tilt. It stayed fixed while the humerus tried to pass underneath it. The rotator cuff was firing but the scapulothoracic rhythm was off—the scapula wasn't rotating enough, so the acromion wasn't clearing the humeral head. The workaround was straightforward but not obvious: stop loading the shoulder and spend three weeks on scapular control work. Bottom-up press holds, serratus punches, wall slides with emphasis on keeping the lower scapula glued to the ribcage. The acromion itself never needed surgery. The problem was that it couldn't move freely because the muscles around it were dysfunctional. Pain resolved in about six weeks once the movement pattern corrected.
Get the Full Details

How To Assess The Acromion Region Properly
Palpation is the simplest starting point. The acromion is easily felt at the top of the shoulder. Run your fingers from the acromion forward along the clavicle—that's the AC joint. Run them backward and downward along the spine of the scapula. Tenderness right at the AC joint points to different issues than tenderness along the undersurface where the rotator cuff passes. For impingement testing, the Neer test is the standard. You stabilize the scapula and passively flex the arm forward, forcing the greater tuberosity of the humerus under the acromion. Pain during this motion suggests subacromial impingement. The Hawkins-Kennedy test is similar but involves forward flexing the arm to 90 degrees and then forcefully internally rotating the humerus. Both tests have decent sensitivity but poor specificity—they tell you impingement is possible but don't identify the underlying cause. The true test is dynamic. Watch the shoulder during movement. Does the acromion track smoothly? Does the scapula wing? Is there pain at a specific angle? Pain between 60 and 120 degrees of abduction is the classic impingement arc, but that's a generalization. Some people hurt at 40 degrees. Others only at 150. The angle tells you less than the quality of movement.
Common Pitfalls
The biggest mistake I see is assuming that all shoulder pain near the acromion is impingement. Cervical radiculopathy from C5-C6 can refer pain directly to the lateral shoulder and acromion region. A disc issue at those levels mimics subacromial problems almost exactly. If treating the shoulder doesn't help, check the neck. Simple as that. Another pitfall is focusing exclusively on the acromion when the problem originates elsewhere. The coracoacromial arch—formed by the acromion, coracoid process, and the coracoacromial ligament connecting them—is a rigid structure. If the ligament is tight or thickened, nothing about the acromion itself needs to change for impingement to occur. I've seen cases where releasing the coracoacromial ligament through targeted soft tissue work resolved chronic impingement symptoms that had persisted for years despite rotator cuff strengthening and even surgery. Acromial fractures are rare but serious. They usually result from a direct fall onto the shoulder or a severe forced adduction injury. The pain is immediate and severe, with inability to abduct the arm. Imaging will show the fracture line, and treatment depends on displacement. Non-displaced fractures can be managed conservatively with a sling for about six weeks. Displaced fractures often require surgical fixation. I've only seen a handful of these in my career, and they're always dramatic presentations.
When The Acromion Is The Actual Problem
Some people are born with a Type III hooked acromion and simply never develop symptoms until later in life, when cumulative wear on the rotator cuff tips them over the edge. In these cases, the acromion shape is a structural bottleneck that can't be changed without surgery. Acromioplasty—surgically reshaping the acromion to create more subacromial space—has been performed for decades. It's not a new procedure, and it's not universally effective. Success rates vary, and the recovery is measured in months, not weeks. I've seen patients who underwent acromioplasty and still had persistent pain because the underlying scapular dysfunctions weren't addressed. Removing bone doesn't fix bad movement patterns. In fact, it can sometimes make things worse by altering the lever arms of the deltoid and other shoulder muscles. The surgery should be considered only after conservative measures have been exhausted and the diagnosis is clear. It's not a first-line treatment for anyone. For most people dealing with acromion-related shoulder issues, the solution starts with improving scapular positioning and movement. The serratus anterior, lower trapezius, and rhomboids control where the scapula sits on the ribcage. When these muscles are weak or inhibited, the scapula tilts forward and the acromion drops into a position that narrows the subacromial space. Strengthening these muscles doesn't change the acromion, but it changes the space around it.

Practical progression: start with scapular retractions and depressions in a neutral arm position. Hold for five seconds, ten reps. Progress to overhead reaches with emphasis on keeping the shoulder blades down and back. Then add light resistance. Band pull-aparts, prone Y raises, and floor-based scapular push-ups all target the right muscles. Avoid heavy overhead pressing until the pain-free range of motion is established. Loading a compromised shoulder only accelerates the wear. The acromion is a small bone, but it carries disproportionate responsibility for shoulder health. Understanding its anatomy, its movement, and its relationship to the structures around it changes how you approach shoulder problems. Most of the time the fix isn't dramatic. It's just a matter of making sure the mechanics around the acromion are working the way they should.