Understanding What Your Step 2 Score Actually Means
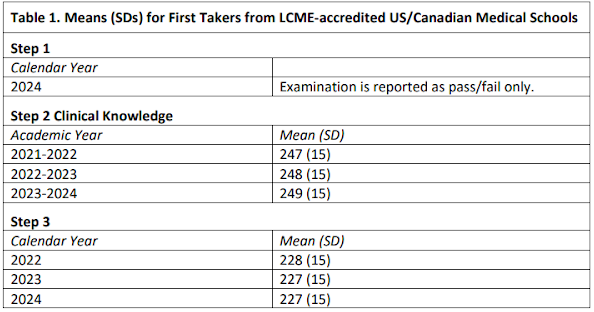
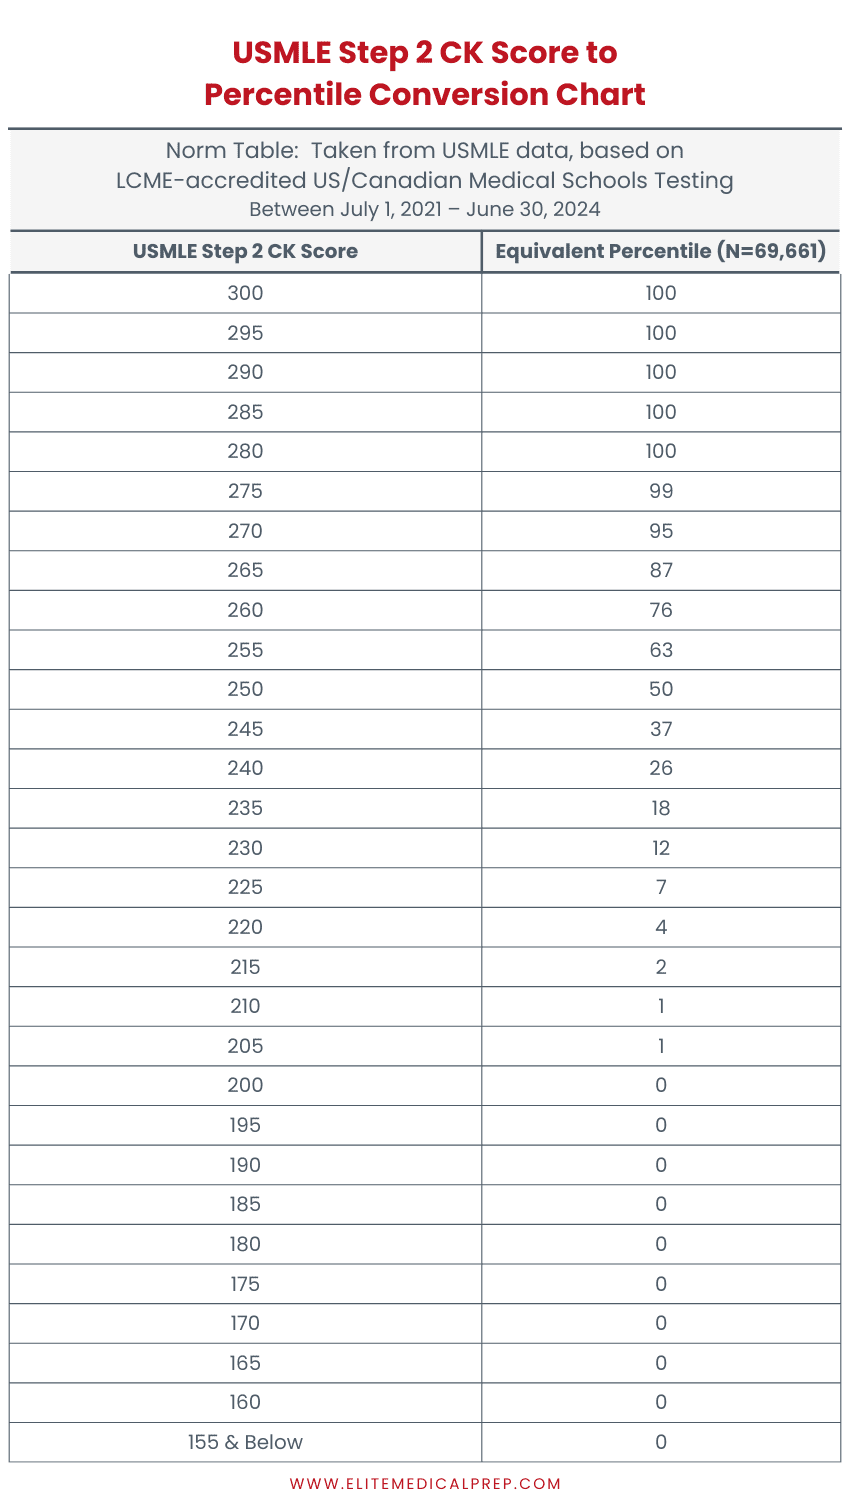
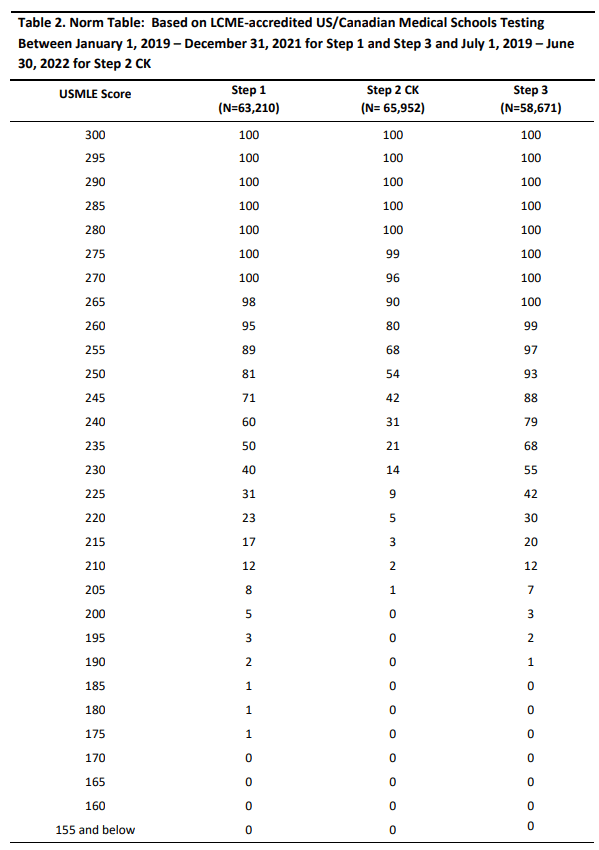
When Step 1 went pass/fail, everyone suddenly realized that Step 2 CK had become the only standardized number programs could compare. That shifted a lot of weight onto one test score, and the percentile charts became the tool people use to figure out where they stand. I still see residents ask about this every match season, usually with a printed score and a link to some percentile calculator on a student blog. Here is what actually happens. Programs receive your numeric score, and somewhere between 100 and 5,000 times per cycle, that number gets compared against a threshold that is either formally stated or quietly enforced. The percentile tells you what fraction of recent test-takers scored below you. That is a ranking metric, not a measure of clinical competence. It is useful because it gives you a rough idea of where you sit relative to the applicant pool, and it is misleading because it says nothing about what any individual program actually requires. The current percentiles (from the most recent available data) look something like this. A score around 246 lands near the 50th to 55th percentile. Around 248 you are near the 65th percentile. Near 252 is roughly the 80th percentile. At 255 you are pushing into the 90th. These numbers shift slightly each year as the overall pool changes, and USMLE does not publish official percentile tables for Step 2 CK the way they used to. The tables you find online are assembled from NRMP data, program director surveys, and student-reported outcomes. They are close enough to be useful but not precise enough to guarantee accuracy.
I had a student email me once with a 246 score who was confident they were above average because the percentile chart they found said 52nd. They did not understand that the 52nd percentile means roughly half of applicants are at or below that number, which is not a strong position for competitive specialties. We ended up looking at program websites, not percentile charts, to figure out where that score would get them reviewed. Sixty percent of dermatology programs we checked had unofficial cutoffs around 250 or higher. Internal medicine was more variable, with many programs reporting a median accepted score in the 248 to 252 range. The percentile chart told them almost nothing about their actual odds. The reason percentiles feel powerful is that they convert a raw number into something that sounds like a ranking system. They are easy to talk about. But the real power is in how programs use them as a filter. Many program coordinators set an automated screen that removes anything below a certain score before a human ever sees the application. A 244 might sit at a decent percentile nationally, but if a program filters at 245, that application disappears regardless of where you fall in the national distribution. Percentiles do not protect you from that. Only knowing your target score protects you from that. There is also a common misunderstanding about score stability. The Step 2 CK has a standard error of measurement around 2 to 3 points. That means a reported score of 250 could reasonably reflect a true ability anywhere from roughly 247 to 253. Retesting to move three points is usually a waste of time and money. The variance overlaps so much that you are not guaranteed improvement, and even if you improve, the percentile shift may be invisible. I told a student this once and they tested again anyway. They went from 248 to 251, which moved them from around the 68th percentile to the 75th. Not nothing, but they had spent four months of study time and about $1,000 for what amounted to a moderate bump. They would have been better off using that time on clinical research or away rotations.
Another thing people miss is that percentiles are cohort-dependent. If the next test cycle brings in a higher-performing group of test-takers, your same raw score drops in percentile. The opposite is also true. During the early pandemic cycles, mean scores dipped slightly because test availability was disrupted and certain demographics took the exam under unusual conditions. Those cohort effects flattened the percentiles and made some scores appear stronger than they would in a normal cycle. Right now, the mean has climbed back toward 247 or 248 depending on who you ask, which compresses the middle percentiles again. If you want a practical way to use this information, here is what I recommend. First, find the score ranges published by the programs you are interested in. The FREIDA database and individual program websites sometimes list accepted score ranges. Second, use the percentile tables only as a rough sanity check, not as a decision-making tool. Third, if your score is near the borderline of a program you want, consider whether an away rotation, strong letter, or research output will matter more than a three-point increase on retest. For most students, that is the higher-leverage move. I know this is a dry way to look at something that feels incredibly personal, but the data does not care about your feelings. A percentile is a descriptive statistic, not a prediction of your match outcome. Programs look at your full application. Your score opens doors, but it does not walk you through them. Use the number to inform your strategy. Do not let it define your entire narrative.
Get the Full Details