What Radiologic Technologists Actually Make
The numbers on job boards are almost never the real number. I've spent over a decade watching techs get excited about posted ranges that don't include shift differentials, call pay, or the fact that travel contracts in certain markets have collapsed since 2023. The salary landscape for radiologic technologists is fragmented enough that anyone giving a single median figure is probably quoting outdated Bureau of Labor Statistics data from 2021 or earlier. Let's just lay out what the actual pay looks like across the different tracks, because the differences are steep and they matter more than the headline number.
The Hidden Pay Scale Unpacking The Real Radiologic Technologist Salary In Todays Market
Staff positions at hospitals and large imaging groups typically run between $65,000 and $95,000 annually for general X-ray techs working day shift. That range shifts dramatically if you add modalities. CT techs command roughly $8,000 to $18,000 more. MRI techs, assuming you have your ARRT certification in MR, tend to be another $5,000 to $10,000 on top of CT. Mammography is somewhere in between, usually around $75,000 to $105,000 depending on volume and whether the facility is unionized. Travel contracts are where the headline numbers get weird. Peak travel pay in 2021 and early 2022 pushed some techs into the $120,000 to $160,000 range for short-term assignments. That has cooled significantly. By mid-2024, typical travel contracts for general radiology in most markets were landing closer to $85,000 to $115,000 all-inclusive, and some rural markets were offering lower. The contracts that still pay well are the ones requiring additional certifications—IR, fluoro, or ultrasound cross-training—and the ones in states with persistent staffing shortages like Arizona, Colorado, and parts of the Pacific Northwest.
Where the Money Actually Hides
Base salary is only part of the equation. The real compensation picture depends on how many items you can stack on. Shift differential is the biggest one most people overlook. Night shift usually adds 10 to 15 percent to your hourly rate. Weekend rotation often carries its own premium, sometimes separate from the night differential. If you're working 8-hour day shift five days a week at a community hospital, you're leaving money on the table compared to someone taking nights or weekends, even at the same base rate. Call pay varies wildly by facility type. Independent imaging centers rarely offer call. Hospital-based departments do, and the structure differs. Some pay a flat draw that you earn back by being called in. Others pay per call with a minimum guarantee. I worked at a mid-size hospital where the call pay was structured as a $25 hourly rate after you were called in, with a two-hour minimum. That doesn't sound like much until you realize you might get called two or three times a month during trauma hours. It added maybe $800 to $1,200 a month to the paycheck. Small amount, but it was money I wasn't getting at my previous outpatient-only position. Overtime availability is another hidden factor. Some departments have steady OT. Others barely touch it. Union contracts often have clearer OT rules and better rates—time and a half after eight hours in a day rather than after forty in a week. That daily overtime threshold makes a huge difference if the department runs short-staffed regularly.
Get the Full Details

Geography Matters More Than You Think
I moved from a metropolitan market in the Midwest to a rural region in the Southwest, and the salary difference alone was about $18,000 a year in my favor going the other direction. But the cost of living adjustment changed the actual purchasing power by maybe $6,000. So the nominal gap was big. The real gap was not as dramatic as it looked on paper. Some of the highest-paying markets for radiologic technologists right now are places like San Francisco, New York City, Boston, Seattle, and Los Angeles. But those salaries get eaten fast by rent and general living costs. The smart money, if you're not tied to a city, is looking at markets where demand is high and housing is still somewhat reasonable. Places like Huntsville Alabama, Boise Idaho, or parts of the Texas Triangle offer solid pay without the coastal squeeze. There's also the rural premium. Some facilities in underserved areas will pay $10,000 to $20,000 more than nearby metro positions just to attract and keep techs. Loan repayment programs through HRSA and state-level initiatives can add another $10,000 to $20,000 in benefit value over a couple of years. I knew a tech who took a position in eastern Kentucky specifically for the loan repayment package. It was a four-year commitment, but she walked away with roughly $30,000 in qualified loan forgiveness by the end of it.
Modalities and How They Move Your Number
General radiography is the entry point. It's also the ceiling for some people, and that's fine. Not everyone needs to specialize. But if you want to push your salary past the nine-figure range, additional certifications matter. Here's the realistic order of return on investment: CT certification gives you the best bang for the buck. Most technologists already have patient care experience. Adding CT usually takes three to six months of dedicated study and on-the-job training. The salary bump is immediate and consistent across nearly every market. MRI certification takes longer and requires more specialized training. The pay bump is real but not as universal. Not every facility has an MRI program, so your mobility as an MRI tech is somewhat more niche depending on where you live. Interventional radiology and fluoro are less commonly certified but can push pay higher in hospital settings. These roles often come with higher physical demands and more exposure risk. The pay reflects that. Vascular interventional techs in busy academic centers can make $110,000 to $140,000 or more, but the schedule is unpredictable and the work is physically taxing.
Ultrasound is a different path entirely. It requires a separate educational program, usually an associate or bachelor's degree in sonography. The pay is competitive, often matching or exceeding CT, but the barrier to entry is higher. If you're already a radiologic technologist, pivoting to sonography is doable but it's a career change, not a certification add-on.

A Problem I Actually Had With Contract Negotiation
A few years ago I was evaluating a travel contract that listed a weekly gross of $2,800. On the surface, that looked excellent. The problem was that $2,200 of it was labeled "tax-free stipend" for housing and meals. The remaining $600 was the taxable hourly wage. The agency was counting on me not reading the breakdown. If I took their recommended housing arrangement, which was a studio apartment they had a partnership with, it would have cost me about $1,900 a month. That left me with almost nothing from the stipend after rent. The effective take-home was nowhere near what the headline number suggested. The workaround was straightforward. I negotiated to receive the entire stipend as taxable income instead. That meant I owed more in taxes, but I could find my own housing for less. I rented a shared house with another traveler for about $800 a month. The math worked out to roughly $4,000 more per month in actual spending money. It required reading the contract carefully and being willing to push back on the agency's default housing setup. Most agencies don't advertise that you can make this choice. They count on people not knowing.
The Benefits Package Can Be Worth As Much As the Salary
A $90,000 salary with great benefits can beat a $100,000 salary with terrible ones. Health insurance premiums, retirement matching, tuition reimbursement, and certification renewal support all factor into real compensation. Some hospital systems offer 100 percent premium coverage for employee-only health insurance. That's easily worth $6,000 to $10,000 a year depending on the market. Retirement matching at 5 to 6 percent is standard at larger systems. A few will match dollar-for-dollar up to 6 percent, which is essentially free money. Paid time off varies enormously. Some facilities give new techs fifteen days a year. Others start at twenty or more. Tenure and union contracts can push this to thirty or more days. If you're comparing two offers that look similar on paper, the one with more PTO and better health benefits is often the better deal financially, especially when you factor in the cost of buying time back through lost wages.
What the Data Actually Shows Right Now
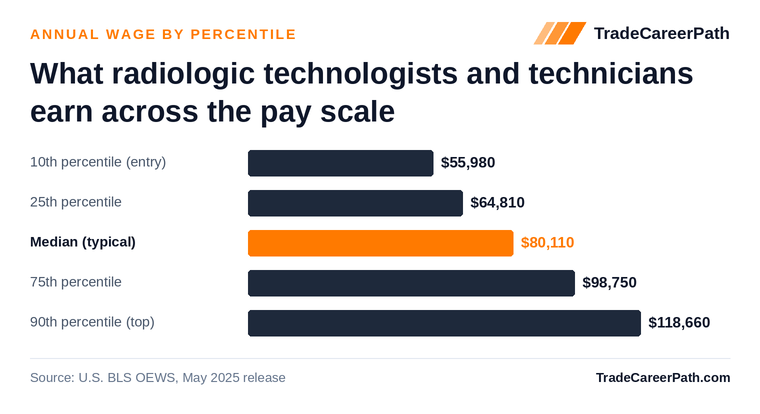
The BLS reports a median annual wage for radiologic technologists around $76,000 as of their most recent detailed survey. That median sits somewhere in the middle of a very wide distribution. The bottom ten percent makes under $50,000, mostly in small outpatient clinics or non-union positions in low-cost regions. The top ten percent pushes past $115,000, and that group skews heavily toward modalities, travel, and unionized hospital positions in high-cost areas. Industry surveys from organizations like the American Society of Radiologic Technologists tend to show slightly higher medians, often in the $80,000 to $85,000 range for full-time staff positions. The discrepancy between BLS data and professional surveys usually comes down to methodology. BLS includes all employment settings and part-time workers. Professional surveys tend to over-sample full-time hospital staff, which skews higher. Travel pay data from staffing agencies is even less reliable. They publish optimistic ranges to attract candidates. Actual placement data for 2024 and 2025 shows a broader distribution than most agencies admit. Some contracts are genuinely strong. Many are mediocre. A few are exploitative. Reading the fine print on every contract matters more than trusting the recruiter's verbal summary.

Union vs Non-Union: The Real Difference
Union contracts provide more transparency and usually better total compensation, but they also come with tradeoffs. Step scales are predictable. You know exactly what you'll make at each year milestone. Overtime distribution is often seniority-based, which means the best shifts go to the longest-tenured people. Non-union facilities may offer more flexibility in scheduling and faster advancement based on performance, but the pay transparency is lower and raises are less predictable. I worked both union and non-union environments over the years. The union hospital had a clearer path to higher pay and better benefits. The non-union imaging center offered more schedule flexibility and a faster route to lead tech responsibilities. Neither was clearly better. It depended on what I valued at the time. The union job was financially stronger by the numbers. The non-union job was less stressful in ways that mattered to my quality of life.
Common Mistakes People Make When Evaluating Offers
The biggest mistake is looking at the annual salary number in isolation. You need to calculate the effective hourly rate including all premiums, then compare that against the actual schedule and workload. A $95,000 position that requires two weekends per month and rotating call might pay less per hour of actual work than an $82,000 position with straight days and no call. Another mistake is undervaluing location independence. If you're willing to relocate for a higher-paying position, you should run the numbers including moving costs, temporary housing during the transition, and any delay in starting the new job. A $15,000 raise can disappear in the first year if you spend $8,000 on relocation and lose two weeks of pay while settling in. The third common error is ignoring the certification renewal requirements. Some states and facilities require continuing education credits, and some employers pay for them while others don't. If you're paying out of pocket for your ARRT recertification every two years, that's an additional $500 to $1,000 expense that eats into your take-home pay. Factor that in when comparing offers.
Where the Market Is Heading
The radiologic technologist labor market is stabilizing after the volatility of the pandemic years. Demand remains strong because the population is aging and imaging utilization continues to grow. But the extreme travel pay premiums have normalized. Entry-level and staff positions are seeing moderate wage growth, perhaps 3 to 5 percent annually in most markets, which tracks close to or slightly above inflation. Automation and AI-assisted imaging are not going to replace technologists soon. The consensus in the industry is that technology will change the workflow, not eliminate the role. Technologists who adapt by adding modalities and developing soft skills around patient communication tend to fare better than those who stay at a single modality indefinitely. The pay gap between general radiography-only techs and multi-modality techs continues to widen, and it likely will for the foreseeable future. Rural and critical access hospitals face persistent staffing challenges. These facilities often cannot compete on salary with urban centers, but they may offer signing bonuses, relocation assistance, and loan repayment that close the gap for people who are willing to work outside major cities. If you're early in your career and not attached to a specific geography, these positions can provide fast experience and financial benefits that compound over time.


