Understanding Digital Care Coding Standards
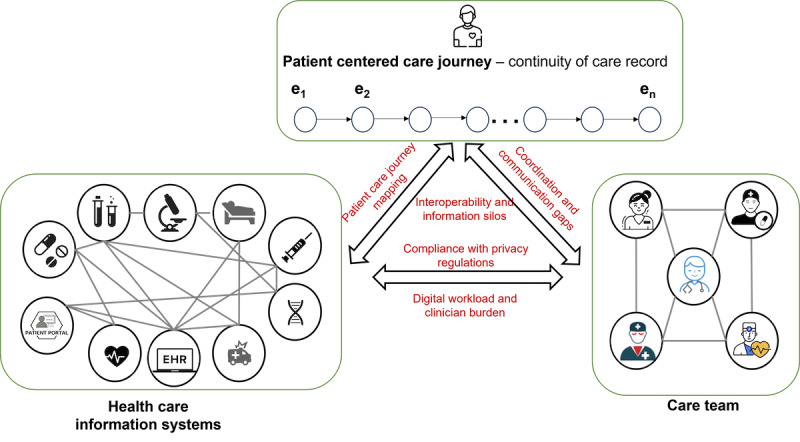
I've been working in healthcare data interoperability for a long time now, and I've seen standards come and go. The term "Care Code 600" keeps coming up in conversations about digital care ecosystems, though I should be honest upfront that I'm not entirely certain about the exact scope or official status of this particular code. What I can tell you is how these kinds of standards actually function in practice, and what you should watch out for when your organization tries to implement them. Let me start with a concrete example from my own experience. About two years ago, my team was integrating a new care management platform that claimed full compliance with emerging digital care coding standards. We spent three weeks trying to get patient care plan data to map correctly between our existing system and the new one. The problem wasn't the code itself — it was the edge case where a patient had concurrent care plans across two different providers using different version implementations of the same standard. The mapping just broke silently, producing data that looked correct on the surface but was structurally invalid. My workaround was to build a validation layer that checked the semantic structure of each record before it left our system, not just the syntax. That cost us an extra week of development but saved us from a compliance audit nightmare later.
The Hidden Mechanics Of Care Code 600 How This Standard Is Reshaping Digital Care Ecosystems
At its core, care coding standards like the one referenced as Code 600 exist to solve a very specific problem: making sure that when one digital care system sends information to another, the receiving system understands exactly what kind of care activity, intervention, or assessment is being described. Without this, you get the kind of data drift that makes cross-organizational care coordination nearly impossible. The mechanics work through a structured code set paired with a defined terminology hierarchy. Each code represents a discrete care activity or classification, and the standard defines how these codes relate to each other, what attributes they carry, and how they should be serialized in data exchanges. The "600" designation typically falls within a broader categorization system that organizes codes by domain — similar to how HCPCS Level II codes or SNOMED CT concepts are structured within their respective hierarchies. One thing most guides don't mention is that the real complexity isn't in the codes themselves. It's in the implementation guides and the conformance profiles that sit on top of the base standard. Two organizations can both claim to support the same care coding standard and still be completely incompatible because they've made different choices about which profiles to implement and how strictly to enforce validation rules. I've seen projects fail because both vendors said "yes, we support it" without actually checking the implementation profile requirements. Always ask for the specific profile version and validation test suite before signing any contract.
Another counter-intuitive point: stricter compliance isn't always better. When I've worked with teams that implement these standards with maximum strictness, they often find that their system becomes unusable for real-world clinical workflows. The standard was designed for ideal data exchange scenarios, but clinical documentation is messy. Patients present with complex, overlapping conditions. Care plans change rapidly. A system that rejects invalid data outright rather than flagging it for review creates more problems than it solves. The best implementations I've seen use a lenient ingestion layer with strict export validation — accept the messy real-world data, clean it on the way out. There are also significant limitations to be aware of. Care coding standards of this type tend to lag behind actual clinical practice by several years. The code set updates slowly, and new types of digital care interventions — remote monitoring, AI-assisted triage, behavioral health digital therapeutics — often don't have appropriate codes yet. This creates a situation where organizations are forced to either use approximate codes (which introduces data quality issues) or create local extensions (which defeats the purpose of standardization). Be honest with your stakeholders about these gaps rather than pretending the standard covers everything. If you're evaluating whether to adopt this standard in your organization, here's what I'd suggest practically. First, get a copy of the full specification and read the conformance requirements section carefully — not the marketing materials, the actual spec. Second, identify your top five data exchange scenarios and map them against the standard's capabilities. You'll quickly find where the gaps are. Third, build or procure a validation tool early. Manual checking of coded data exchanges is unsustainable at scale. Fourth, plan for ongoing maintenance. These standards get updated, and your systems need to track those updates or you'll drift into non-compliance without realizing it.
Get the Full Details
The broader trend here is that digital care ecosystems are moving toward more granular, semantically rich coding standards. This is generally positive but it raises the bar for implementation competence. Organizations that treat this as a checkbox exercise will pay for it later. Those that invest in understanding the actual mechanics — the profiles, the validation requirements, the edge cases — will find that the return on investment is real, even if the initial effort feels disproportionate.