Reading Knee Biomechanics From Plain Radiographs
Most people look at a knee X-ray and see bones. Some gaps. Maybe a scar if they are unlucky. What they are not seeing is the entire load distribution system written in grayscale. I spent roughly eight years reading orthopedic films before I stopped guessing and started actually measuring. Here is what that looks like in practice.The Hidden Map Inside Your Knee How A Normal Xray Reveals The Secret Architecture Of Movement
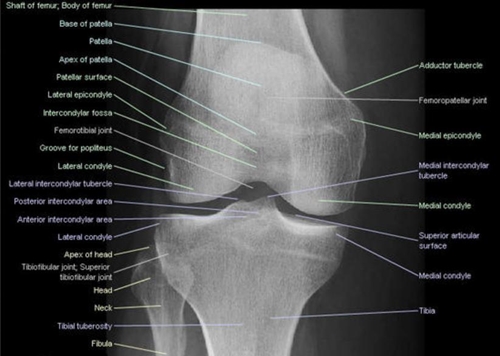
A standard knee X-ray isn't a static picture of structure. It is a snapshot of how weight moves through your leg at a specific angle. The space between the femur and the tibia isn't uniform cartilage. It is a pressure map. When you stand with full weight bearing, the medial compartment compresses to maybe two millimeters while the lateral side stays open. That tells you something about your joint line orientation and whether you carry varus or valgus stress. I learned this the hard way. Early in my residency I had a patient with medial knee pain but a completely normal looking X-ray report from the referring clinic. The radiologist called it within normal limits. I spent about twenty minutes tracing the joint spaces on the PA weight-bearing film and noticed the medial width was 2.1 mm on the left and 3.4 mm on the right, even though the report said bilateral joint spaces were preserved. That asymmetry meant unilateral cartilage loss on the painful side. We scoped him three weeks later. Confirmed partial thickness defibulation of the medial femoral condyle. If I had just read the report and stopped there I would have missed it entirely. The tibiofemoral angle is where most beginners stop, and that is exactly where the useful information begins and ends if you aren't careful. You draw a line through the mechanical axis of the femur from the center of the femoral head to the center of the knee, and another line along the tibial shaft. The angle between them should sit around seven degrees of valgus in a normal adult. Anything less than five degrees and you are likely dealing with varus alignment. Anything beyond nine degrees and you are looking at progressive valgus collapse.
But the mechanical axis doesn't tell the whole story. Look at the Joint Line Convergence Angle. JLCAs are measured differently on each side. On the medial side you measure the angle between the tibial plateau and a perpendicular to the tibial shaft. Normal is below six degrees. On the lateral side, above four degrees is considered abnormal. When both sides are elevated it means your joint line is tilting and the cartilage is getting crushed unevenly. This is a more accurate predictor of osteoarthritis progression than bone spur size or joint space narrowing alone. Patellofemoral tracking is another layer most people completely ignore. Draw a line through the sulcus of the patella, the patellar tangent line, and see where it sits relative to the trochlear groove. If the patella is tilted laterally or sitting high, that changes the force vectors across the kneecap with every step. Patella alta, defined by a Caton-Deschamps index above 1.2, shifts load away from the distal patella and concentrates it on the retropatellar cartilage. You can see it in runners with anterior knee pain who have structurally normal femoral-tibial joints. Here is something that always surprises people. The fibular head position matters more than it should. Track the relationship between the fibular head and the lateral tibial plateau. If the fibula sits too high or too far posterior, you are looking at potential biceps femoris or LCL tension alterations that change lateral compartment loading. I had a case last year where a patient complained of isolated lateral knee pain. Every test pointed to the collateral ligament. The X-ray showed the fibular head was elevated by about four millimeters compared to the contralateral side. MRI revealed a proximal biceps femoris tear. The X-ray gave us the answer before we even ordered the MRI.
Subchondral bone changes are your earliest warning signal. Sclerosis under the weight-bearing surface appears before joint space narrowing becomes visible. It shows up as increased whiteness in the subchondral bone on the X-ray. This is bone adapting to increased pressure. It is your body's way of saying the cartilage underneath is under too much load. Once you see sclerosis, you know the disease process started months or years before the radiologist flagged it as early osteoarthritis. osteophyte location tells you which compartment is failing. Medial spurs mean medial compartment overload. Lateral spurs mean lateral overload. Patellar spurs mean patellofemoral joint stress. The pattern matters more than the count. Three small medial osteophytes with a preserved joint space tell a different story than one massive osteophyte with a joint space of one millimeter. Now the limitations. Plain radiography misses soft tissue almost entirely. Meniscal tears won't show up unless they cause secondary bone changes. Ligament integrity is inferred from alignment but never directly visualized. Early chondromalacia is invisible. A completely normal X-ray does not mean a normal knee. It just means the bones look okay at that moment. If clinical suspicion remains high after a normal film, you move to MRI or diagnostic ultrasound without hesitation.
Get the Full Details

Another blind spot is dynamic instability. Static X-rays capture one position. If the knee subluxates during gait, you won't see it on a standing film. Fluoroscopic dynamic imaging or stress radiographs are needed for that. I use custom-made stress views when I suspect ligamentous laxity. The difference between a 5 mm translation on one side and 12 mm on the other is clinically significant even when the static X-ray looks symmetrical. Here is a practical workflow I use now. First, verify the X-ray is weight-bearing and properly positioned. A non-weight-bearing AP film can overestimate joint space by two to three millimeters. Then measure the mechanical axis, JLCA on both sides, patellar height, and fibular head position. Check for subchondral sclerosis and note osteophyte location. Compare bilaterally whenever possible. Document everything numerically rather than qualitatively. Saying joint space is narrowed is meaningless. Saying medial joint space is 1.8 mm and lateral is 4.2 mm tells someone exactly what is happening. One technique that saved me repeatedly is rotating the film to match the patient's posture. Knee X-rays are usually taken standing, but patients present sitting or lying down. If you rotate the image to the same plane as the pain-generating position, previously hidden asymmetries become obvious. This takes about thirty seconds and has caught more missed pathologies than I care to admit.
The bottom line is that a knee X-ray contains far more information than the report typically provides. The bones aren't just structural columns. They are records of how force has traveled through the joint over time. Every sclerosis patch, every asymmetric joint space, every deviated fibular head is data. Learning to read it takes practice, but once you start measuring instead of estimating, the images become significantly more useful than most clinicians give them credit for being.