What You Actually Need To Know Before You Start Looking At This Area
The occipital bone is a single bone at the back and bottom of your skull. It forms the base of the cranium, creates the foramen magnum where the spinal cord exits, and serves as the primary attachment point for several neck muscles. Most people never think about it until they get a headache that won't quit. Then suddenly it's the most important bone in their body. That reaction is understandable but incomplete. The occipital bone does far more than just sit there holding things together. There are four lobes in the occipital region of the brain, and they are primarily responsible for visual processing. The primary visual cortex, also called V1 or Brodmann area 17, sits along the calcarine sulcus on the medial surface of the occipital lobe. Damage to this area doesn't necessarily cause blindness in the traditional sense. It causes cortical blindness, which means the eyes work fine but the brain can't process the information coming through the optic nerves. That distinction matters clinically. When a patient presents with vision changes after head trauma, checking occipital lobe function comes before referral to an ophthalmologist. The bone itself has several anatomical landmarks that matter for anyone working in manual therapy or surgical fields. The external occipital protuberance is that bump you can feel at the back of your head. The superior nuchal line runs horizontally from it, and the inferior nuchal line sits below that. These are insertion points for the trapezius, sternocleidomastoid, and deep suboccipital muscles. The nuchal lines serve as attachment sites for the nuchal ligament, which helps support the head without constant muscular effort. Understanding where these lines run tells you immediately which muscles are under tension just by palpating the area.
Here's something most anatomy textbooks gloss over. The occipital bone doesn't fuse completely until between ages twenty and twenty-four. There are typically four ossification centers, and they meet at the basilar part, the lambdoid suture, and the squamous part. In adults, those sutures can still show variable patterns on imaging. If you're interpreting CT scans or MRIs and you see what looks like a fracture line running through the occipital bone in an older patient, it might just be a persistent synchondrosis or an incompletely fused suture. Mistaking a normal variant for a pathology on imaging is a real problem, and it happens more often than you'd think in emergency radiology reads.
Suboccipital Tension And The Occipital Nerves
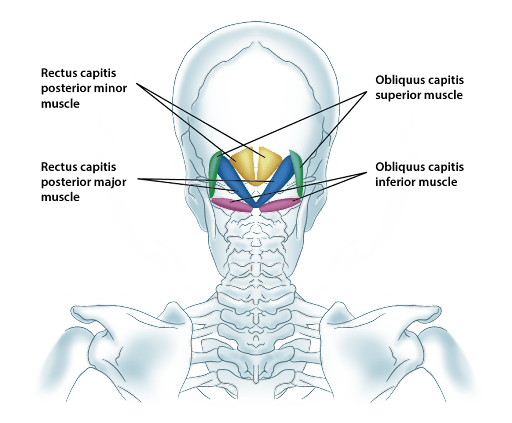
The greater occipital nerve, which is the dorsal ramus of C2, pierces through the semispinalis capitis and then the trapezius near the superior nuchal line. It supplies sensation to the posterior scalp from the hairline up to the vertex. When the suboccipital muscles — the rectus capitis posterior major and minor, the obliquus capitis superior and inferior — become hypertonic, they compress or irritate this nerve. The result is occipital neuralgia, which presents as sharp, shooting, electric-shock-like pain that starts at the base of the skull and radiates upward. It's frequently misdiagnosed as a tension headache or migraine. I dealt with a case involving a patient who had been treated for chronic migraines for three years without relief. The headaches were unilateral, pulsating, and accompanied by photophobia, which is the classic migraine presentation. But the trigger point was palpable right at the C2 level, just lateral to the midline where the greater occipital nerve exits. The pain pattern followed the nerve distribution precisely. We confirmed the diagnosis with a diagnostic block using lidocaine at the suboccipital triangle, and the headache disappeared for the duration of the anesthetic. That's when we knew the occipital bone and its surrounding structures were the actual source, not the vascular changes associated with migraines. She went on to receive regular suboccipital releases and Botox injections at the trigger points, which reduced her headache frequency from daily to maybe twice a month.
Get the Full Details

Cervicogenic Headaches And Clinical Implications
Cervicogenic headache is a secondary headache originating from structures in the cervical spine, and the occipital bone is central to this diagnosis. The International Classification of Headache Disorders has specific criteria for it. Pain must be unilateral, located in the occipital region, and exacerbated by certain neck positions or movements. Palpation of the suboccipital muscles reproduces the headache. The pain often refers forward around to the frontal or temporal region, which is why so many people with cervicogenic headaches are initially treated for sinus issues or temporal tendonitis when the real problem is at the skull base. The atlas-axis complex, C0 through C2, has the greatest range of rotation in the entire cervical spine. Roughly fifty percent of cervical rotation occurs at the atlantoaxial joint alone. When this segment is hypomobile, the occiput compensates by restricting its own motion, which leads to increased strain on the suboccipital musculature. The muscle tension then compresses the greater and lesser occipital nerves. This chain of events is mechanical in origin, which means mechanical interventions are what usually help. Mobilization of the atlanto-occipital and atlantoaxial joints, combined with release of the suboccipital group, addresses the root cause rather than masking symptoms with analgesics. There is a significant limitation to be aware of here. Not every headache that originates near the occiput is cervicogenic. Vertebral artery dissection can present with posterior headache and neck pain, and it is a medical emergency. If the headache came on suddenly, is the worst headache the person has ever had, or is accompanied by neurological deficits like vertigo, ataxia, dysarthria, or unilateral weakness, you do not manipulate the neck. You send them to the ER immediately. Occipital bone pain can mask vascular pathology, and mistaking a dissection for a muscle tension issue has resulted in strokes. Any practitioner working in this area needs to screen for red flags before proceeding with manual therapy or interventions.
Postural Contribution And Long-Term Degeneration
Forward head posture places enormous stress on the occipital region. For every inch the head moves forward from its neutral alignment, the effective weight on the cervical spine increases by approximately ten pounds. A head that weighs about eleven pounds in neutral position can exert force equivalent to forty pounds or more when the head is protracted forward by three or four inches. That force is transmitted through the suboccipital muscles and directly to the occipital bone at its attachment sites. Over time, this leads to adaptive changes. The nuchal ligament thickens. The insertion points on the nuchal lines become enthesopathic. The bone itself can develop calcifications and osteophytes at the muscle attachment sites, which further irritate the surrounding nerves and soft tissues. Chronic compression at the foramen magnum is another consequence of prolonged poor posture. The jugular foramina, which sit on either side of the foramen magnum and transmit the internal jugular veins and cranial nerves IX, X, and XI, can become compromised. Impaired venous drainage from the brain through the jugular system may contribute to intracranial pressure issues that manifest as headaches, brain fog, and dizziness. This is an area where the clinical evidence is still developing, but the anatomical mechanism is sound. Structural compression of venous outflow pathways at the skull base is a plausible contributor to symptoms that patients describe but can't easily localize.
Practical Assessment And Self-Management
Assessment of the occipital region starts with palpation. Locate the external occipital protuberance, then trace the superior nuchal line laterally on both sides. Press firmly along this line and note any areas of tenderness, induration, or asymmetry. The suboccipital triangle is located just below the inferior nuchal line, between the rectus capitis posterior major and the obliquus capitis superior. This is where the greater occipital nerve becomes superficial and is most susceptible to compression. Tenderness here is a strong indicator of suboccipital hypertonicity. Self-management includes gentle mobilization of the upper cervical spine and release of the suboccipital muscles. A tennis ball placed between the occiput and a wall, used with gentle head movements, can provide myofascial release to the suboccipital group. This is different from aggressive foam rolling, which tends to aggravate the area further. The suboccipital muscles are small and deeply seated; they respond better to sustained, gentle pressure held for two to three minutes per point rather than repeated forceful motion. Combining this with chin tucks performed in a seated or standing position, holding each repetition for five seconds and doing ten to fifteen reps, helps retrain the deep neck flexors and reduce the load on the occipital attachment sites. Stretching the upper trapezius and sternocleidomastoid is also relevant since these muscles insert near the occipital bone and contribute to the tension cascade. Side-bending the neck away from the affected side while gently rotating the chin toward the opposite shoulder creates a longitudinal stretch through the SCM and trapezius insertion zone. Holding for thirty seconds and repeating three times on each side, done consistently over several weeks, can measurably reduce occipital nerve irritation in cases where the nerve compression is primarily muscular in origin.

When To Escalate Beyond Self-Care
Most occipital region complaints respond to conservative management within four to six weeks. If there is no improvement after that window, or if symptoms worsen at any point, imaging becomes necessary. A CT scan will show bony detail clearly — any fractures, degenerations, or anatomical variants at the craniocervical junction. An MRI is better for evaluating soft tissue compression of the neural and vascular structures, including the cerebellar tonsils and the upper cervical spinal cord. Chiari malformation, where brain tissue extends into the foramen magnum, is one condition that can present with occipital headache and is best visualized on MRI. It is often discovered incidentally in adults who have been misdiagnosed with tension headaches for years. Interventional options exist for cases that don't respond to manual therapy and self-care. Greater occipital nerve blocks with corticosteroid and local anesthetic can provide relief lasting weeks to months. Radiofrequency ablation of the C2 dorsal ramus offers longer-term disruption of pain signaling from the suboccipital region. In refractory cases where structural compression is confirmed, surgical decompression may be indicated. These are not first-line treatments, but they are established procedures with documented efficacy when appropriately indicated. The occipital bone is structurally simple but functionally complex. It anchors the visual processing center of the brain, protects the craniocervical junction, serves as the primary lever arm for head movement, and houses the neural pathways that transmit sensory information from the scalp and posterior neck. When it becomes a source of pain, the causes are rarely limited to the bone itself. They involve the nerves that pass near it, the muscles that attach to it, and the joints that move with it. Treating only the headache without evaluating the underlying mechanical and neurological factors at the skull base tends to produce temporary results at best.


