
Why Everyone Misses The Occipital Bone Until Something Goes Wrong
The occipital bone is the large, bowl-shaped bone at the back and bottom of the skull. It's easy to dismiss because you can't see it in a mirror, but it does far more work than most people give it credit for. It forms the posterior cranial fossa, protects the cerebellum and brainstem, and anchors several key muscles and ligaments. I've worked with enough anatomy students and clinicians over the years to know that this bone shows up on exams and in practice exactly when something has gone wrong with it. Here's the practical breakdown. The occipital bone consists of four parts: the squamous part, the basilar part, the two lateral parts, and the foramen magnum region. The foramen magnum is the big opening at the base where the spinal cord exits the skull. On either side of it are the occipital condyles, which articulate with the first cervical vertebra, C1, also called the atlas. This joint is what allows your head to nod up and down. The nuchal lines on the outside surface are attachment points for the trapezius, splenius capitis, semispinalis capitis, longissimus capitis, and the ligamentum nuchae. Not glamorous, but crucial for posture. Let me walk through how I actually use this in a clinical or anatomical setting, because the textbook order doesn't always match real life. When someone presents with cervicogenic headache, you start at the external occipital protuberance, which sits right in the midline. That bump is the landmark. You palpate along the superior nuchal line going laterally, and then down the inferior nuchal line. Tenderness along these lines is often where the problem lives, not necessarily in the bone itself. The muscles pull on these ridges, and chronic tension creates referral patterns that mimic migraine. I had a patient last year with what looked like a textbook vestibular migraine, but the dizziness wasn't central at all. It was her sternocleidomastoid and suboccipital group pulling on the occiput in a restricted pattern from a whiplash injury years ago. Once I adjusted her C1-C2 mechanics and released the suboccipitals, the vertigo dropped by maybe seventy percent within two sessions. You won't find that on a Wikipedia page.
The jugular foramen is another feature worth remembering. It sits just anterior to the jugular notch on the lateral part, and it transmits the internal jugular vein along with cranial nerves nine, ten, and eleven. A lesion here affects swallowing, shoulder shrugging, and gag reflex. If you're interpreting a CT or MRI of the posterior fossa, don't overlook how small the margins are between the bone and these structures. A tiny osteophyte or subtle calcification in that space can compress the lower cranial nerves without any dramatic imaging findings elsewhere. One thing beginners consistently miss is the clivus. That's the slope formed by the basilar part of the occipital bone meeting the sphenoid body. It sits right behind the sella turcica. Pathologies like chordomas love that area, and they grow slowly enough that symptoms can be absent for years until they hit the brainstem. The clival region is hard to access surgically and tricky to image cleanly on standard sequences. An MRI with contrast and thin cuts through the skull base is really what you need, not a routine head CT that gets swallowed by bone artifact at the foramen magnum level. Another nuance that comes up more than you'd expect is the relationship between the occipital nerve and the bone itself. The greater occipital nerve is the dorsal ramus of C2. It pierces the semispinalis capitis and then runs upward between the obliquus capitis inferior and the rectus capitis posterior major before emerging near the superior nuchal line. What that means practically is that a tight rectus capitis posterior minor or a trigger point in the suboccipital triangle can compress that nerve right as it approaches the bone. The result is pain in the back of the scalp that radiates toward the ear or behind the eye. Occipital nerve blocks work, but if you don't release the muscular tension around the superior nuchal line, the relief only lasts a few days. I learned that the hard way when a patient came back three times in a month thinking the block wasn't working.
There are also developmental variations that matter. The hypoglossal canal runs through the occipital bone just anterior to the condyle, transmitting cranial nerve twelve. Some people have accessory canals or the hypoglossal canal sits in a slightly different position. If you're doing surgical planning in the skull base, even a five-millimeter variation can mean the difference between a clean approach and a complicated one. Fusion anomalies of the occipital bone with the upper cervical spine, known as occipitalization of C1, show up incidentally on imaging sometimes. They're usually asymptomatic, but they alter the biomechanics of the craniocervical junction and can contribute to headaches or limited neck rotation over time. The downside of focusing on the occipital bone is that it's too easy to assume every posterior headache or neck complaint comes from here. Sometimes it really does. But if palpation along the nuchal lines is completely non-tender and the neurologic exam is normal, looking deeper into thoracic outlet syndrome or brachial plexus referral is probably more productive. The occiput can be a scapegoat when the real issue is higher up in the cervical spine or even coming from the temporomandibular joint. If you want a solid reference for the anatomy, most standard texts like Gray's Anatomy or Netter's cover this thoroughly. For clinical correlation, Moore's Clinically Oriented Anatomy has good palpation guides. Nothing free and downloadable replaces a physical cadaver dissection, but 3D anatomy apps and online atlases can fill the gap if you're studying remotely. Just don't rely on them for surgical planning decisions.
Get the Full Details
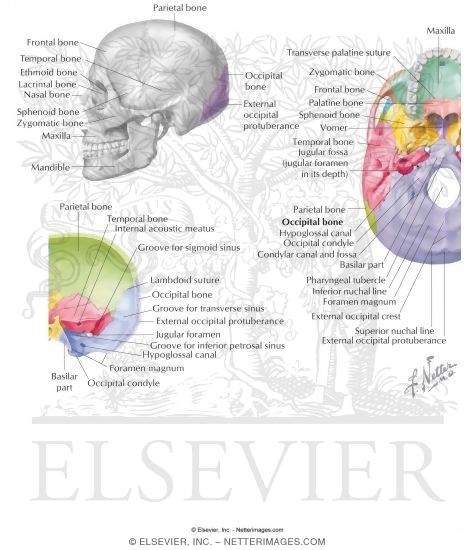
The occipital bone doesn't get the attention it deserves until you're looking at it under pressure. It holds the brainstem in place, anchors your postural musculature, and contributes to one of the most important joints in your entire skeleton with C1. Once you understand its landmarks and relationships, you'll start seeing it in a different way, not as a background piece of the skull, but as a structural keystone.


