What Spondylosis Actually Is
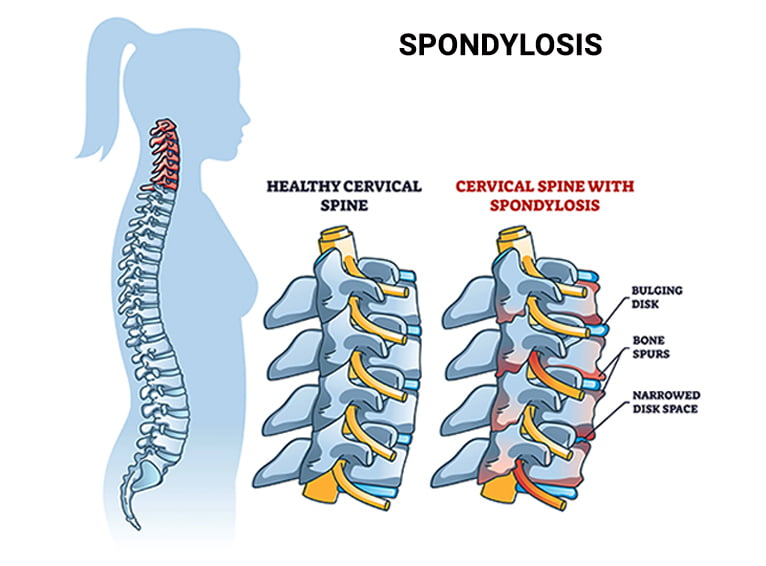
Spondylosis is a broad term for age-related wear and tear on the spinal columns, including the intervertebral discs and the joints in the vertebrae. It affects the cervical, thoracic, and lumbar spine. Most people with spondylosis never know they have it because imaging studies frequently reveal degenerative changes in asymptomatic individuals. The term itself just means degenerative joint disease of the spine. It is not a disease in the traditional sense, and it does not automatically mean pain or disability. I spent years reading MRI reports and watching patients get scared by terminology that looked worse than their actual condition. The disconnect between radiology language and clinical reality is one of the biggest problems in spine care. A report might describe "severe multilevel spondylosis with neural foraminal narrowing" and suddenly the patient is convinced they are going to need surgery. In most cases, conservative management works fine and the degenerative changes seen on imaging simply represent normal aging.
The Hidden Dangers Of Spondylosis A Guide To Understanding The Medical Term And Its Impact
The real concern with spondylosis is not the condition itself but what happens when degenerative changes actually compress nearby structures. Nerve root compression causes radiculopathy, which presents as radiating pain, numbness, or weakness along the affected nerve pathway. Spinal canal compression leads to myelopathy, which is far more serious and involves dysfunction of the spinal cord itself. Cervical spondylotic myelopathy is the dangerous endpoint most clinicians watch for. It develops slowly, often over years, and patients frequently attribute their symptoms to general aging. Gait disturbances, hand clumsiness, and loss of fine motor control are common early signs. A patient might complain about buttons being harder to manage or walking feeling uneven, and these clues get missed for months or even years while the compression progressively worsens. Thoracic spondylosis is relatively uncommon compared to cervical and lumbar involvement, but when it does cause myelopathy it can be devastating because the thoracic spinal canal has less room for compensation. Lumbar spondylosis typically causes nerve root symptoms rather than cord symptoms since the spinal cord ends around the L1-L2 level, but cauda equina syndrome from massive central disc herniation with superimposed spondylotic changes remains a surgical emergency.
Why Imaging Findings Do Not Equal Problems
This is where most people get tripped up. A 2017 study published in Spine found that approximately 38 percent of asymptomatic adults under 40 showed evidence of lumbar spondylosis on MRI. By age 60, that figure rises to roughly 90 percent. The vast majority of those people never develop symptoms. This means imaging should never drive treatment decisions on its own. I recall a specific case from my practice that illustrates this clearly. A patient in her early forties came in with mild lower back discomfort that had been present for about two weeks. She had previously undergone an MRI elsewhere that reported "advanced L4-L5 spondylosis with severe facet arthropathy and moderate neural foraminal narrowing bilaterally." She was convinced her spine was falling apart and had been referred for specialist consultation. Her actual examination revealed normal strength, intact sensation, and only mild paraspinal tenderness with no neurologic deficits. The MRI findings were consistent with her age and activity level, but they were not the cause of her brief, self-limited back complaint. We avoided unnecessary referrals and procedures by correlating the imaging with the clinical exam, which is exactly what should happen.
Get the Full Details

When Spondylosis Becomes Symptomatic
Symptomatic spondylosis develops through a combination of mechanical compression and inflammatory processes. Degenerated discs lose height and hydration, which changes load distribution across the motion segment. This triggers reactive bone formation at the facet joints and produces osteophytes along the vertebral margins. These structural changes narrow the spaces through which nerves and the spinal cord travel. Cervical radiculopathy from spondylosis typically follows a dermatomal pattern. C6 nerve root compression causes pain and numbness radiating into the thumb side of the forearm and hand. C7 affects the middle finger. C8 involves the ring and little fingers. Lumbar radiculopathy commonly presents as sciatica, with L5 root involvement causing lateral leg and dorsum foot symptoms, and S1 root involvement affecting the posterior leg and lateral foot. The onset is usually gradual, though acute exacerbations can occur after minor trauma or even without an identifiable trigger. Morning stiffness lasting less than thirty minutes is common. Symptoms often worsen with prolonged static postures and improve with positional changes and movement. This pattern helps distinguish mechanical spondylotic pain from other causes like infection or malignancy, which typically produce constant pain that worsens at night and does not change with position.
Diagnostic Approach That Actually Works
History and physical examination remain the foundation of diagnosis. Neurologic assessment should include motor testing, sensory evaluation, reflex comparison, and gait observation. Special tests like Spurling maneuver for cervical radiculopathy and Lasègue sign for lumbar nerve root irritation provide additional clinical data. If myelopathy is suspected, checking for Hoffmann sign, clonus, and the presence of a hyperreflexic state is essential. MRI is the imaging modality of choice when neurologic symptoms are present or when conservative treatment has failed after six to eight weeks. X-rays can demonstrate alignment issues, disc space narrowing, and osteophyte formation but cannot visualize nerve compression directly. CT myelography serves as an alternative when MRI is contraindicated. Electromyography and nerve conduction studies help differentiate radiculopathy from peripheral neuropathy, which is a common diagnostic challenge since both can present with similar sensory and motor complaints. I have seen too many patients undergo unnecessary procedures because the treatment was driven by imaging rather than clinical findings. The corollary is equally true: some patients with significant compression on MRI who are asymptomatic do not need any intervention at all. Treat the patient, not the scan.
Conservative Management As First-Line Treatment
Most spondylotic conditions respond well to non-surgical approaches. The evidence base supports physical therapy focused on core stabilization, posture correction, and targeted strengthening as a first-line intervention. A structured program lasting six to twelve weeks typically shows meaningful improvement in functional outcomes and pain scores. Patient education about the benign nature of most degenerative findings reduces anxiety and improves adherence to treatment. Pharmacologic options include NSAIDs for short-term pain control, oral corticosteroids for acute radicular flares, and neuropathic agents like gabapentin or duloxetine for persistent nerve pain. Muscle relaxants may help during acute episodes but carry sedation risks that limit long-term use. Topical treatments provide modest benefit with minimal systemic side effects. Epidural steroid injections offer targeted anti-inflammatory delivery for radicular symptoms that do not respond to oral medications. Cervical epidural injections carry slightly higher risk than lumbar approaches due to proximity to critical vascular structures, so experienced operators and proper technique matter significantly. The evidence for repeated injections beyond two or three is limited, and diminishing returns should prompt reevaluation of the treatment plan.

Surgical Indications and Outcomes
Surgery becomes necessary when there is progressive neurologic deficit, intractable pain despite adequate conservative management, or myelopathy. Cervical myelopathy generally does not improve with conservative treatment and often requires surgical decompression to prevent further deterioration. The timing of surgery in myelopathy cases remains somewhat controversial, but delaying intervention in progressive myelopathy carries real risk of permanent dysfunction. Anterior approaches like ACDF and corpectomy provide direct decompression of anterior pathology with spinal fusion for stability. Posterior approaches including laminectomy and foraminotomy address posterior compression without the morbidity associated with anterior dissection. Cervical disc replacement remains an option for select patients with single-level disease who want to preserve motion, though long-term outcomes compared to fusion show comparable results with potentially less adjacent segment stress. Lumbar surgery for spondylosis typically involves decompression through laminotomy or laminectomy, with fusion added when instability is present or created during the procedure. Microsurgical techniques have reduced tissue trauma and shortened recovery periods considerably compared to open approaches. Patient selection remains the most important predictor of surgical success.
What This Condition Cannot Do
It is important to state clearly what spondylosis does not cause. It does not progress to cancer. It does not automatically lead to paralysis in the absence of severe myelopathy. It does not shorten lifespan in the vast majority of cases. It does not require surgical intervention in most patients. The degenerative changes visible on imaging are often far more dramatic than the clinical significance they actually have. Conversely, spondylosis does have limitations in how well it responds to treatment. Advanced myelopathy with established spinal cord damage may not reverse completely even after surgical decompression. Some patients develop chronic pain syndromes where the original structural compression has been addressed but central sensitization maintains symptoms. Adjacent segment disease remains a recognized long-term complication after spinal fusion, occurring at a rate of approximately 2 to 3 percent per year, which means cumulative risk increases significantly over decades.
Long-Term Considerations
Regular follow-up is important for patients with known significant stenosis or myelopathy, even when asymptomatic. Progression can be insidious, and regular neurologic monitoring allows earlier intervention before irreversible damage occurs. Lifestyle modification focusing on maintaining healthy body weight, regular low-impact exercise, and proper body mechanics provides the best long-term management strategy for most patients. The overall prognosis for spondylosis is favorable when the condition is understood correctly and managed appropriately. Most people live full active lives with degenerative spinal changes that require no specific treatment beyond basic preventive measures and occasional symptomatic management during flare episodes.