What TTP Actually Is And Why It Gets Missed
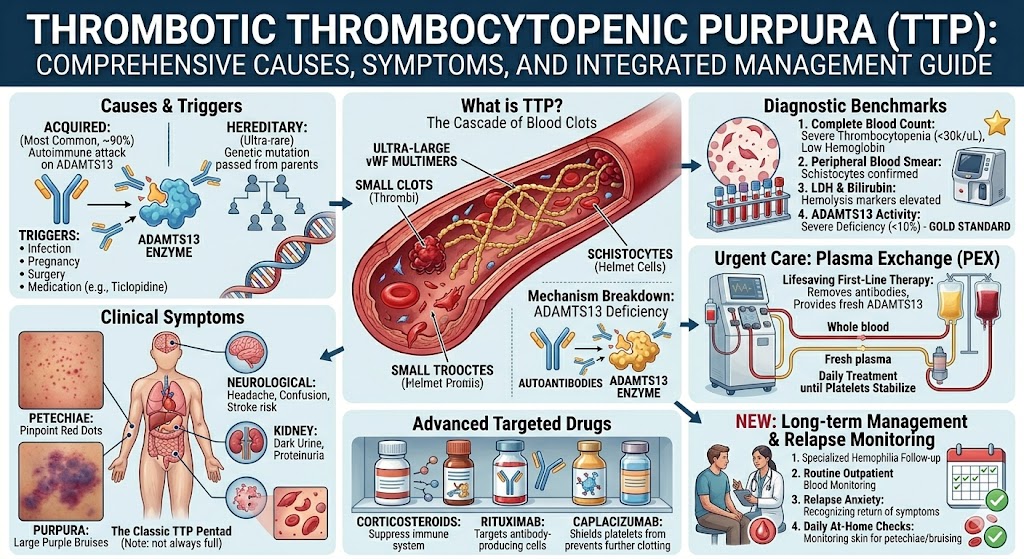
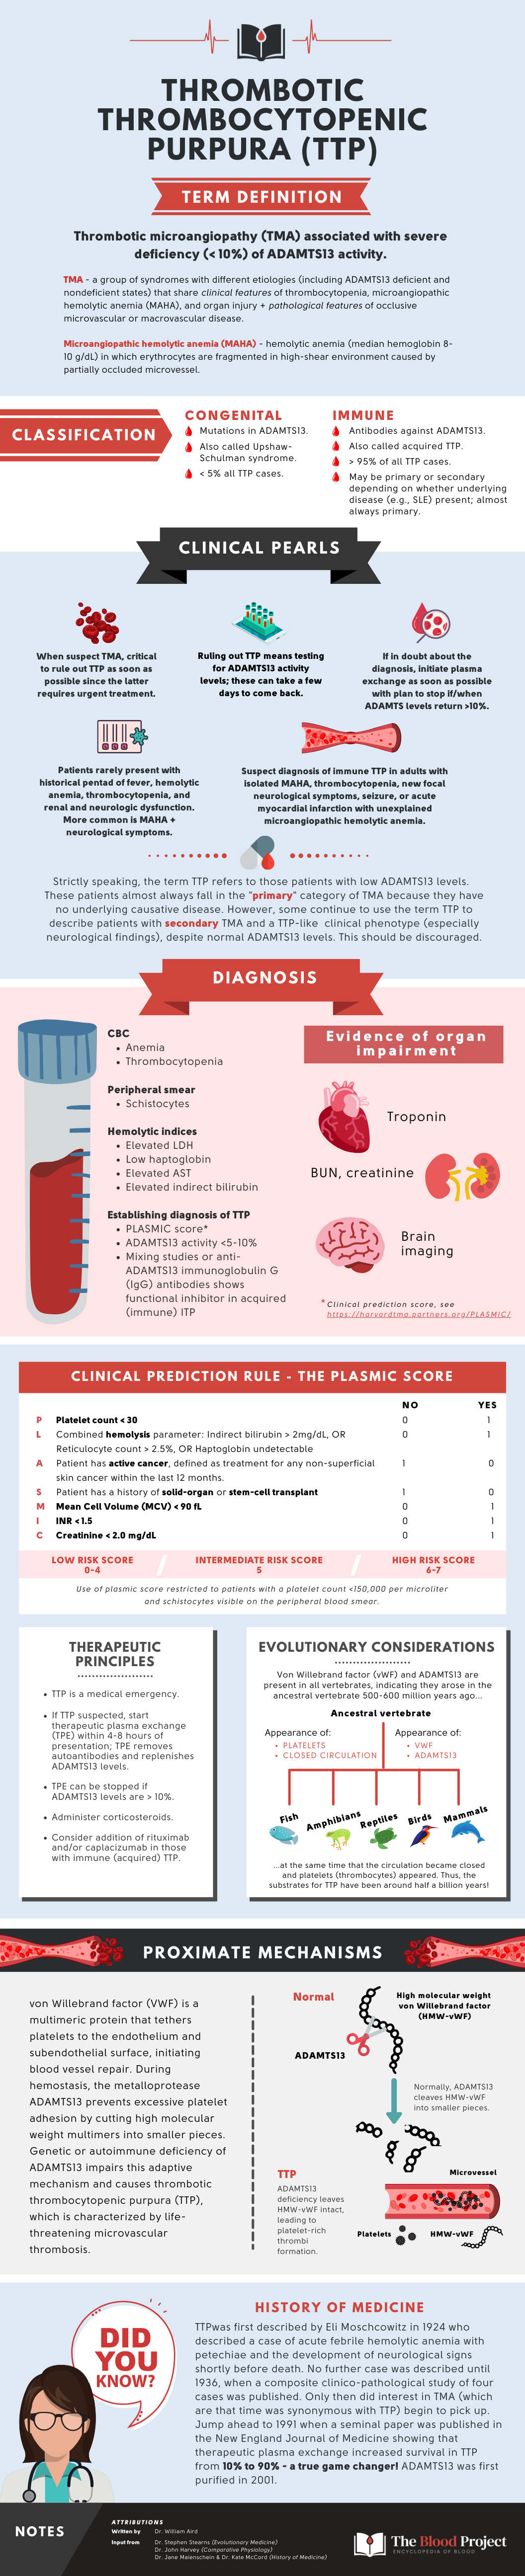
Thrombotic thrombocytopenic purpura is a blood disorder where tiny clots form throughout the body's small blood vessels. Those clots use up platelets faster than your body can replace them, which means you're simultaneously dealing with dangerous clotting and a bleeding risk from low platelets. It's rare, maybe one or two cases per million people each year. The problem isn't just that it's uncommon. It's that the symptoms overlap with a dozen other conditions, so patients often bounce between doctors before anyone connects the dots. Liz Luttig's case is one of the more public examples of how quickly this can go wrong. She was a healthy woman in her forties who developed flu-like symptoms that were initially dismissed. By the time the diagnosis was confirmed, she had already suffered significant organ damage. She died in 2003. Her husband Michael Luttig later became an advocate for raising awareness about TTP, which is understandable given what happened, but the takeaway here is clinical: the early presentation is almost always nonspecific. Medical textbooks teach the "classic pentad" of TTP symptoms: fever, low platelets, microangiopathic hemolytic anemia, kidney problems, and neurological changes. In practice, you rarely see all five. Most patients present with only two or three. What you'll actually see in the ER is someone who looks like they have a bad case of the flu or food poisoning. The platelet count might be low, the hemoglobin is dropping, and there's schistocytes on the peripheral smear. If you order the right test at the right time, you can catch it.
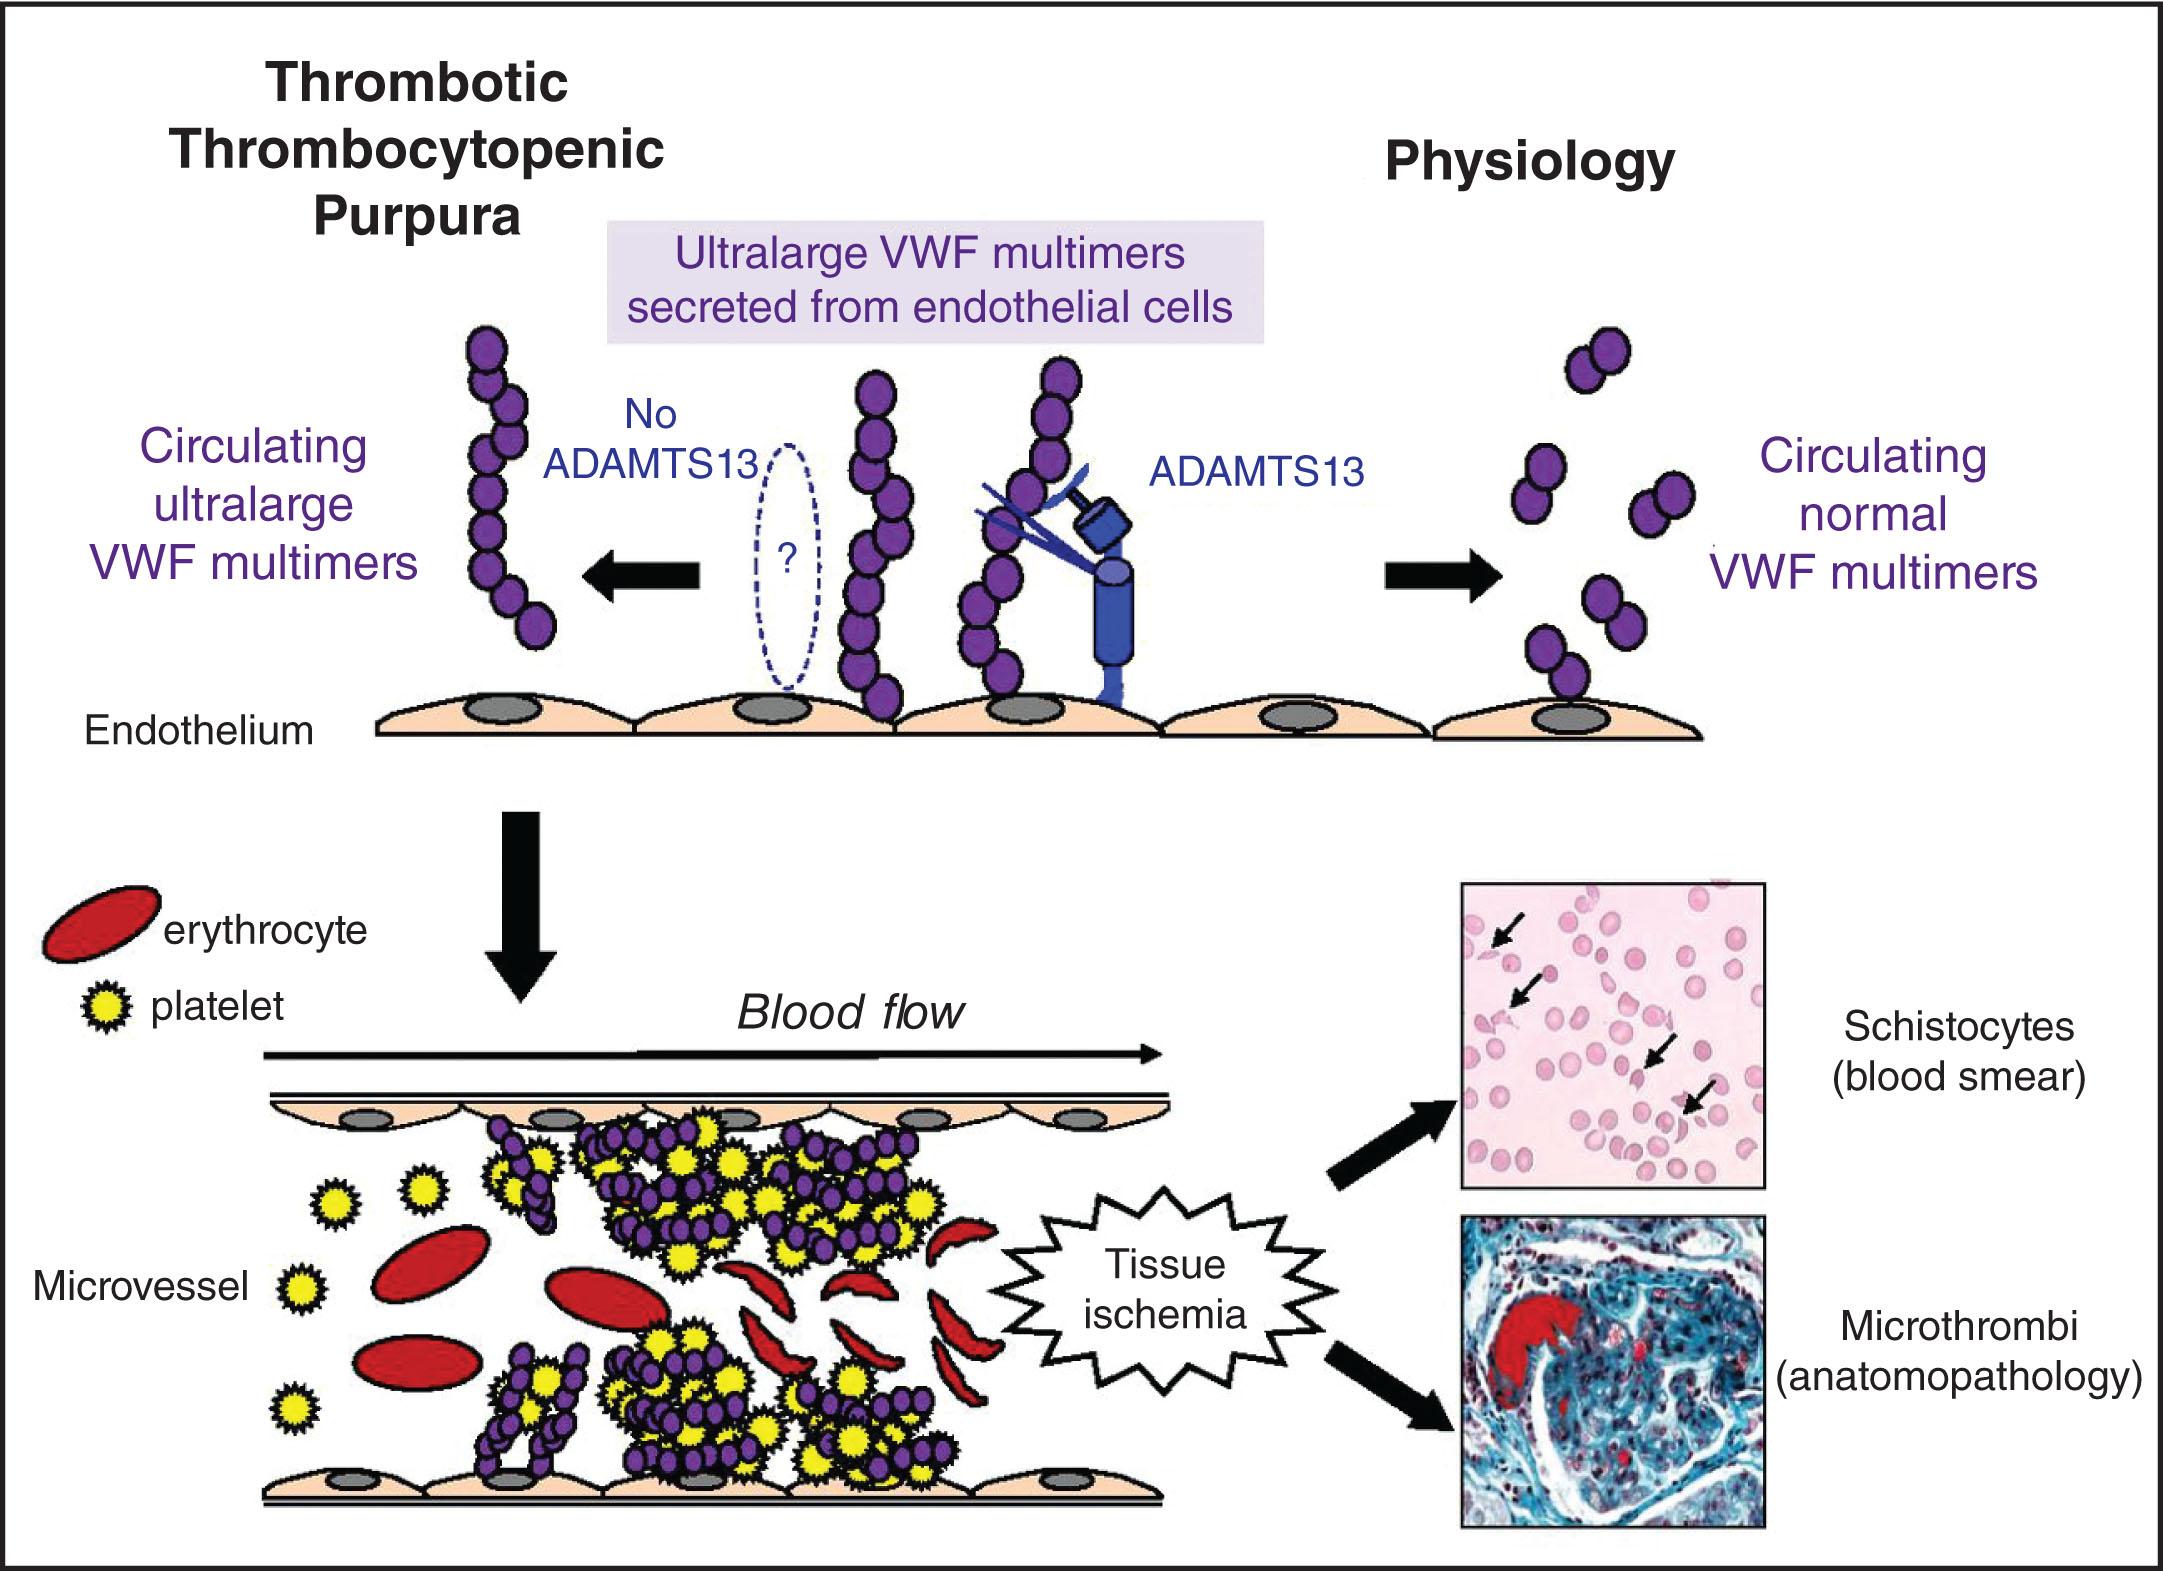
The ADAMTS13 test is the gold standard for diagnosis. It measures the level of a specific enzyme that normally chops von Willebrand factor into manageable pieces. In TTP, that enzyme is either missing or severely reduced, usually below ten percent of normal activity. I've seen cases where the ADAMTS13 result came back borderline at fifteen percent and the clinical picture still fit, so don't rule it out just because the number isn't rock bottom. Clinical judgment matters more than a single lab value.
Why Plasma Exchange Isn't As Simple As You'd Think
The standard treatment is therapeutic plasma exchange, or TPE. You remove the patient's plasma and replace it with donated plasma. This gets rid of the uncleaved von Willebrand factor and replaces the missing ADAMTS13 enzyme. The earlier you start, the better the outcome. Mortality was over ninety percent before plasma exchange became standard. Now it's somewhere around ten to twenty percent if treated promptly. Here's what the guidelines don't always emphasize: you don't wait for the ADAMTS13 result to start treatment. If you suspect TTP clinically, you start plasma exchange immediately. Every hour you wait while waiting for lab confirmation increases the risk of permanent organ damage. I've been in situations where the clinical team hesitated because the platelet count was only moderately low, around sixty thousand, and the patient wasn't critically ill yet. That hesitation cost us. The patient deteriorated overnight. Don't let a seemingly reasonable platelet count lull you into delaying treatment when the rest of the picture fits. Corticosteroids are usually added alongside plasma exchange. The typical regimen is prednisone at one milligram per kilogram per day or sometimes intravenous methylprednisolone for the acute phase. This helps suppress the immune response in acquired TTP, which is the more common form in adults.
Get the Full Details
Rituximab Has Changed The Game
For acquired or immune-mediated TTP, which accounts for the vast majority of adult cases, rituximab has become a standard part of the treatment protocol. It targets the B-cells producing the antibodies against ADAMTS13. The timing matters here. Starting rituximab early in the course, ideally within the first week, reduces the risk of relapse significantly. Some centers give it as a single dose of three hundred seventy-five milligrams per square meter. Others use a different schedule. The data supports early administration either way. Caplacizumab is a newer addition to the treatment landscape. It's an anti-von Willebrand factor nanobody that blocks the interaction between von Willebrand factor and platelets. Essentially, it prevents the microclots from forming in the first place. It's not a replacement for plasma exchange but an adjunct that can reduce the time to platelet count recovery. The tradeoff is bleeding risk, especially mucosal bleeding. I've seen patients on caplacizumab develop significant nosebleeds and GI bleeding that required additional intervention. It's a useful tool but it's not risk-free.
When Plasma Exchange Isn't Available
This is a practical problem that doesn't get discussed enough. Plasma exchange requires specialized equipment and trained staff. Not every hospital has it. If a patient presents at a small community hospital and TTP is suspected, the standard recommendation is plasma infusion while arranging transfer to a center that can do exchange. A rough guideline is two hundred fifty to three hundred milliliters of fresh frozen plasma, which can temporarily supplement the missing enzyme. This buys time, usually six to twelve hours, but it's not a substitute for definitive plasma exchange. HUS, or hemolytic uremic syndrome, is the main condition you need to distinguish from TTP. They share the same basic mechanism of microangiopathic hemolytic anemia and thrombocytopenia. The key difference is that HUS typically presents with more severe kidney involvement and less prominent neurological symptoms. Typical HUS is often preceded by a diarrheal illness, usually E. coli O157:H7. Atypical HUS is complement-mediated and treated differently, often with eculizumab rather than plasma exchange. Getting this distinction wrong leads to the wrong treatment. Disseminated intravascular coagulation, or DIC, is another mimic. In DIC, you're consuming clotting factors as well as platelets, which shows up as a prolonged PT and PTT along with elevated D-dimer. In TTP, the PT and PTT are typically normal. That's one of the quick differentiators you can check at the bedside with basic coagulation labs.
Relapse Is More Common Than You'd Expect
Even after successful treatment, TTP can come back. The relapse rate for immune-mediated TTP is somewhere around ten to thirty percent, usually within the first few months but occasionally years later. Patients need to understand this and know the warning signs. Any recurrence of fatigue, dark urine, unusual bruising, neurological changes, or fever after a TTP diagnosis should trigger immediate medical evaluation and a repeat ADAMTS13 test. Some patients develop chronic or relapsing TTP that requires long-term management. This might involve periodic plasma exchange, ongoing rituximab therapy, or prophylactic caplacizumab. There's no single protocol that works for everyone. It's managed case by case based on the patient's history and response to treatment.
What Survivors Face After Treatment
Recovery from TTP isn't clean. Even patients who survive the acute episode can have lasting effects. Kidney function may not fully return. Neurological deficits, including cognitive changes and memory problems, are not uncommon. Some patients require long-term rehabilitation. The psychological impact is significant too. Going through a life-threatening illness like this changes people. Support groups and counseling help, but they're often underutilized. The Luttig case highlighted another issue that doesn't get enough attention: the diagnostic delay. Liz Luttig saw multiple doctors over several days before being admitted to a hospital that could diagnose TTP. Each visit resulted in a different diagnosis and a discharge with symptomatic treatment. By the time she was admitted, the disease had progressed to a point where organ damage was irreversible. This isn't an unusual story. It happens frequently enough that every emergency medicine physician should have a high index of suspicion for TTP in any patient presenting with unexplained thrombocytopenia and hemolytic anemia, regardless of how stable they appear initially.