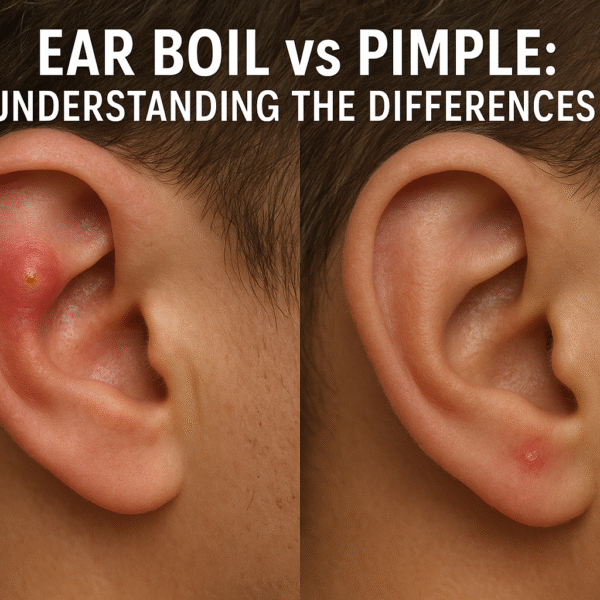
Why Your Ear Is Not Just Another Spot On Your Face
I spent three years working in an outpatient dermatology clinic before I got tired of the same patient every week—someone who had squeezed a bump inside their ear canal and ended up with an infected hematoma that required incision and drainage under local anesthesia. It happened so frequently that I stopped counting the visits. The pattern was always identical: small red bump, ignored until it grew, popped with a tweezers or fingernail, swelling follows within 24 hours, and then the inevitable trip to urgent care. Here is what most people do not realize about pimples in the ear. The skin in and around the ear canal is fundamentally different from facial skin. It is thinner, more vascular, and sits directly over cartilage with very little subcutaneous fat to absorb inflammation. When you introduce bacteria through a tear in that skin, the infection does not stay localized the way it might on your chin or forehead. It tracks along the cartilage and into the confined space of the ear canal, where swelling has nowhere to expand.
The Hidden Dangers Of Ear Pimple Popping Why You Should Stop Now
The dangers are not abstract. They are mechanical and anatomical. The ear canal is roughly seven centimeters long in adults and curves twice before reaching the eardrum. Any object you push in there—tweezers, cotton swabs, your own fingers—has to navigate that S-shaped passage blind. You cannot see what you are doing. The moment you puncture a pimple inside that canal, you have created an open wound in a warm, dark, moist environment that is essentially a bacterial incubator. I had a patient once who popped a pimple in the concha, the bowl-shaped area just outside the canal opening. She used a sterilized needle, which sounded responsible until I examined her. The abscess had tracked backward along the posterior wall of the canal. By the time she came in, she could not hear out of that ear. The swelling had occluded the entire canal. It took two weeks of oral antibiotics and daily wet compresses to bring it down. She had lost three days of work and spent about $600 on the urgent care visit. The specific complications you need to understand are these:
Perichondritis. This is infection of the tissue surrounding the ear cartilage. It is not rare and it is not trivial. The cartilage has no blood supply of its own—it draws nutrients from the perichondrium. When bacteria invade that layer, the cartilage begins to die. The result is cauliflower ear, the same deformity seen in wrestlers and boxers, except in this case it comes from a pimple you squeezed with dirty fingers. Treatment requires intravenous antibiotics and sometimes surgical debridement. I have seen it treated too late, resulting in permanent structural damage to the external ear. Otitis externa progression. A simple pimple in the ear canal can seed a full-blown case of swimmer's ear. The canal skin is already prone to microtears from cleaning attempts. Popping a pimple adds a second breach. Within 48 hours you are dealing with diffuse inflammation, discharge, and pain that makes chewing or sleeping impossible. Topical antibiotic drops help, but only if caught early. Once the swelling closes the canal completely, drops cannot reach the infected area and you need systemic treatment. Cavernous sinus thrombosis. This is the extreme end of the risk spectrum and it is rare but real. The venous drainage from the face and ears connects to the cavernous sinus inside the skull. Bacteria from an untreated ear infection can travel through valveless veins and reach that sinus. The mortality rate from cavernous sinus thrombosis is significant even with modern treatment. It takes weeks to develop, so most people do not connect their popped pimple to the neurological symptoms that follow. I mention it because it is the reason ENT surgeons take ear infections seriously enough to admit patients for IV antibiotics.
Get the Full Details

What To Do Instead Of Popping
Warm compresses. This is the standard recommendation and for good reason. Apply a clean washcloth soaked in warm—not hot—water to the affected area for ten to fifteen minutes, three to four times a day. The heat increases blood flow to the area, which brings immune cells to fight the infection naturally. It also softens the skin and can help a pimple come to a head and drain on its own without manipulation. Over-the-counter benzoyl peroxide gel at two point five percent concentration works for surface pimples in the outer ear. Apply a tiny amount with a cotton swab, being careful not to push it into the canal. Do not use this inside the ear canal. The skin there is far more sensitive and benzoyl peroxide can cause severe irritation and chemical burns in that location. I had a patient who applied Acnefree inside her canal and came in with contact dermatitis that mimicked an infection. It took a week of topical steroids to resolve. Saline rinses are effective for keeping the area clean without introducing new bacteria. Mix one quarter teaspoon of non-iodized salt in eight ounces of distilled or boiled water. Apply with a clean syringe or cotton ball to the outer ear only. Never inject or squirt solution into the canal unless a physician has confirmed your eardrum is intact.
If the pimple is painful, swollen, and located inside the canal, stop trying home treatments and see a doctor. Oral antibiotics are often necessary at that stage. Waiting too long because you hope it will resolve on its own is how perichondritis develops. I have prescribed a twelve-day course of cephalexin for cases that could have been caught earlier with a single urgent care visit instead of three days of escalating symptoms.
When To Stop Hesitating And Seek Care
Fever. This is the clearest sign that a localized skin infection has become systemic. Any temperature above one zero point zero degrees Fahrenheit with an ear lesion warrants same-day evaluation. Swelling that spreads beyond the immediate area of the pimple. Red streaks moving outward from the site. Increased pain when you pull on the outer ear or press on the tragus—these are classic signs of otitis externa or perichondritis. Discharge that is yellow, green, or bloody. Hearing loss in the affected ear. All of these indicate the infection has progressed beyond a simple comedone and requires professional intervention. I keep a rule in my clinic that changed early in my career. If a patient presents with an infected ear lesion and admits to popping it, I do not lecture them. I document it, treat it, and make sure they understand the specific risks before they leave. The shame around picking at skin is real and it keeps people from seeking care until complications develop. The data does not lie: patients who present within the first twenty-four hours of visible infection respond to oral antibiotics alone. Those who wait forty-eight to seventy-two hours often require incision and drainage plus a longer antibiotic course. The difference is almost entirely about timing. The ear pimple itself is usually harmless. It is the intervention that creates the problem. Keep your hands out of your ear canal. Use warm compresses for the outer ear only. Seek medical attention if anything inside the canal becomes inflamed. The anatomy does not forgive careless manipulation and the consequences are permanent when they occur.