Controlling Chain Infection in Real-World Settings
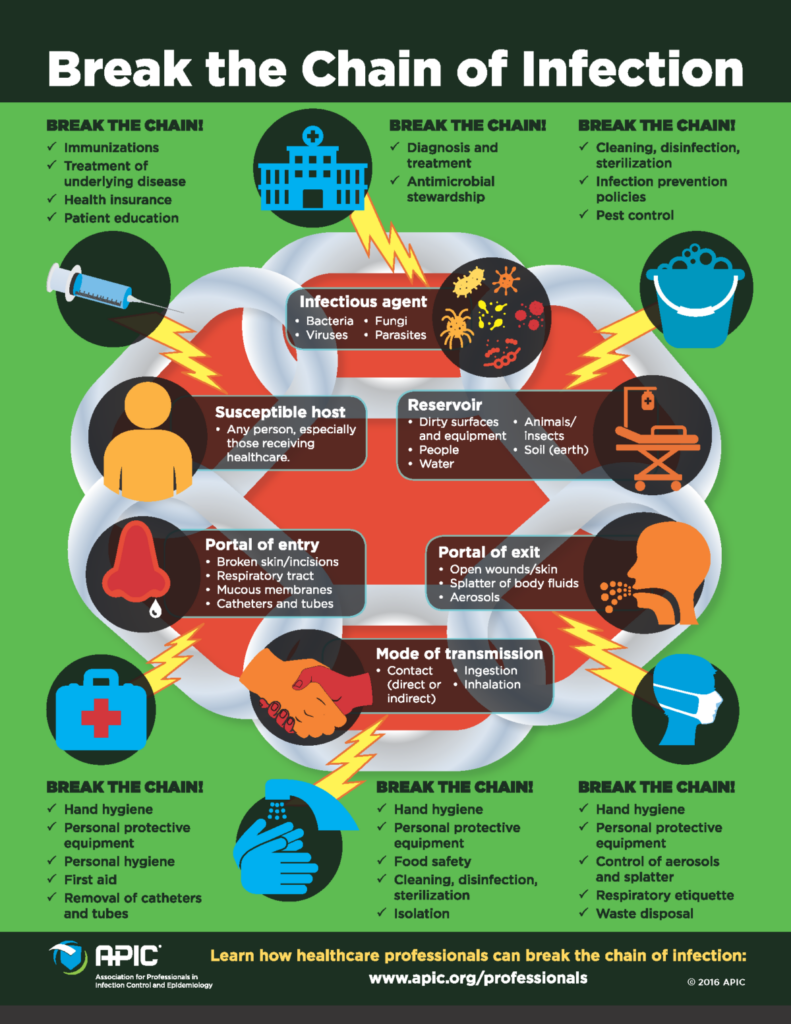
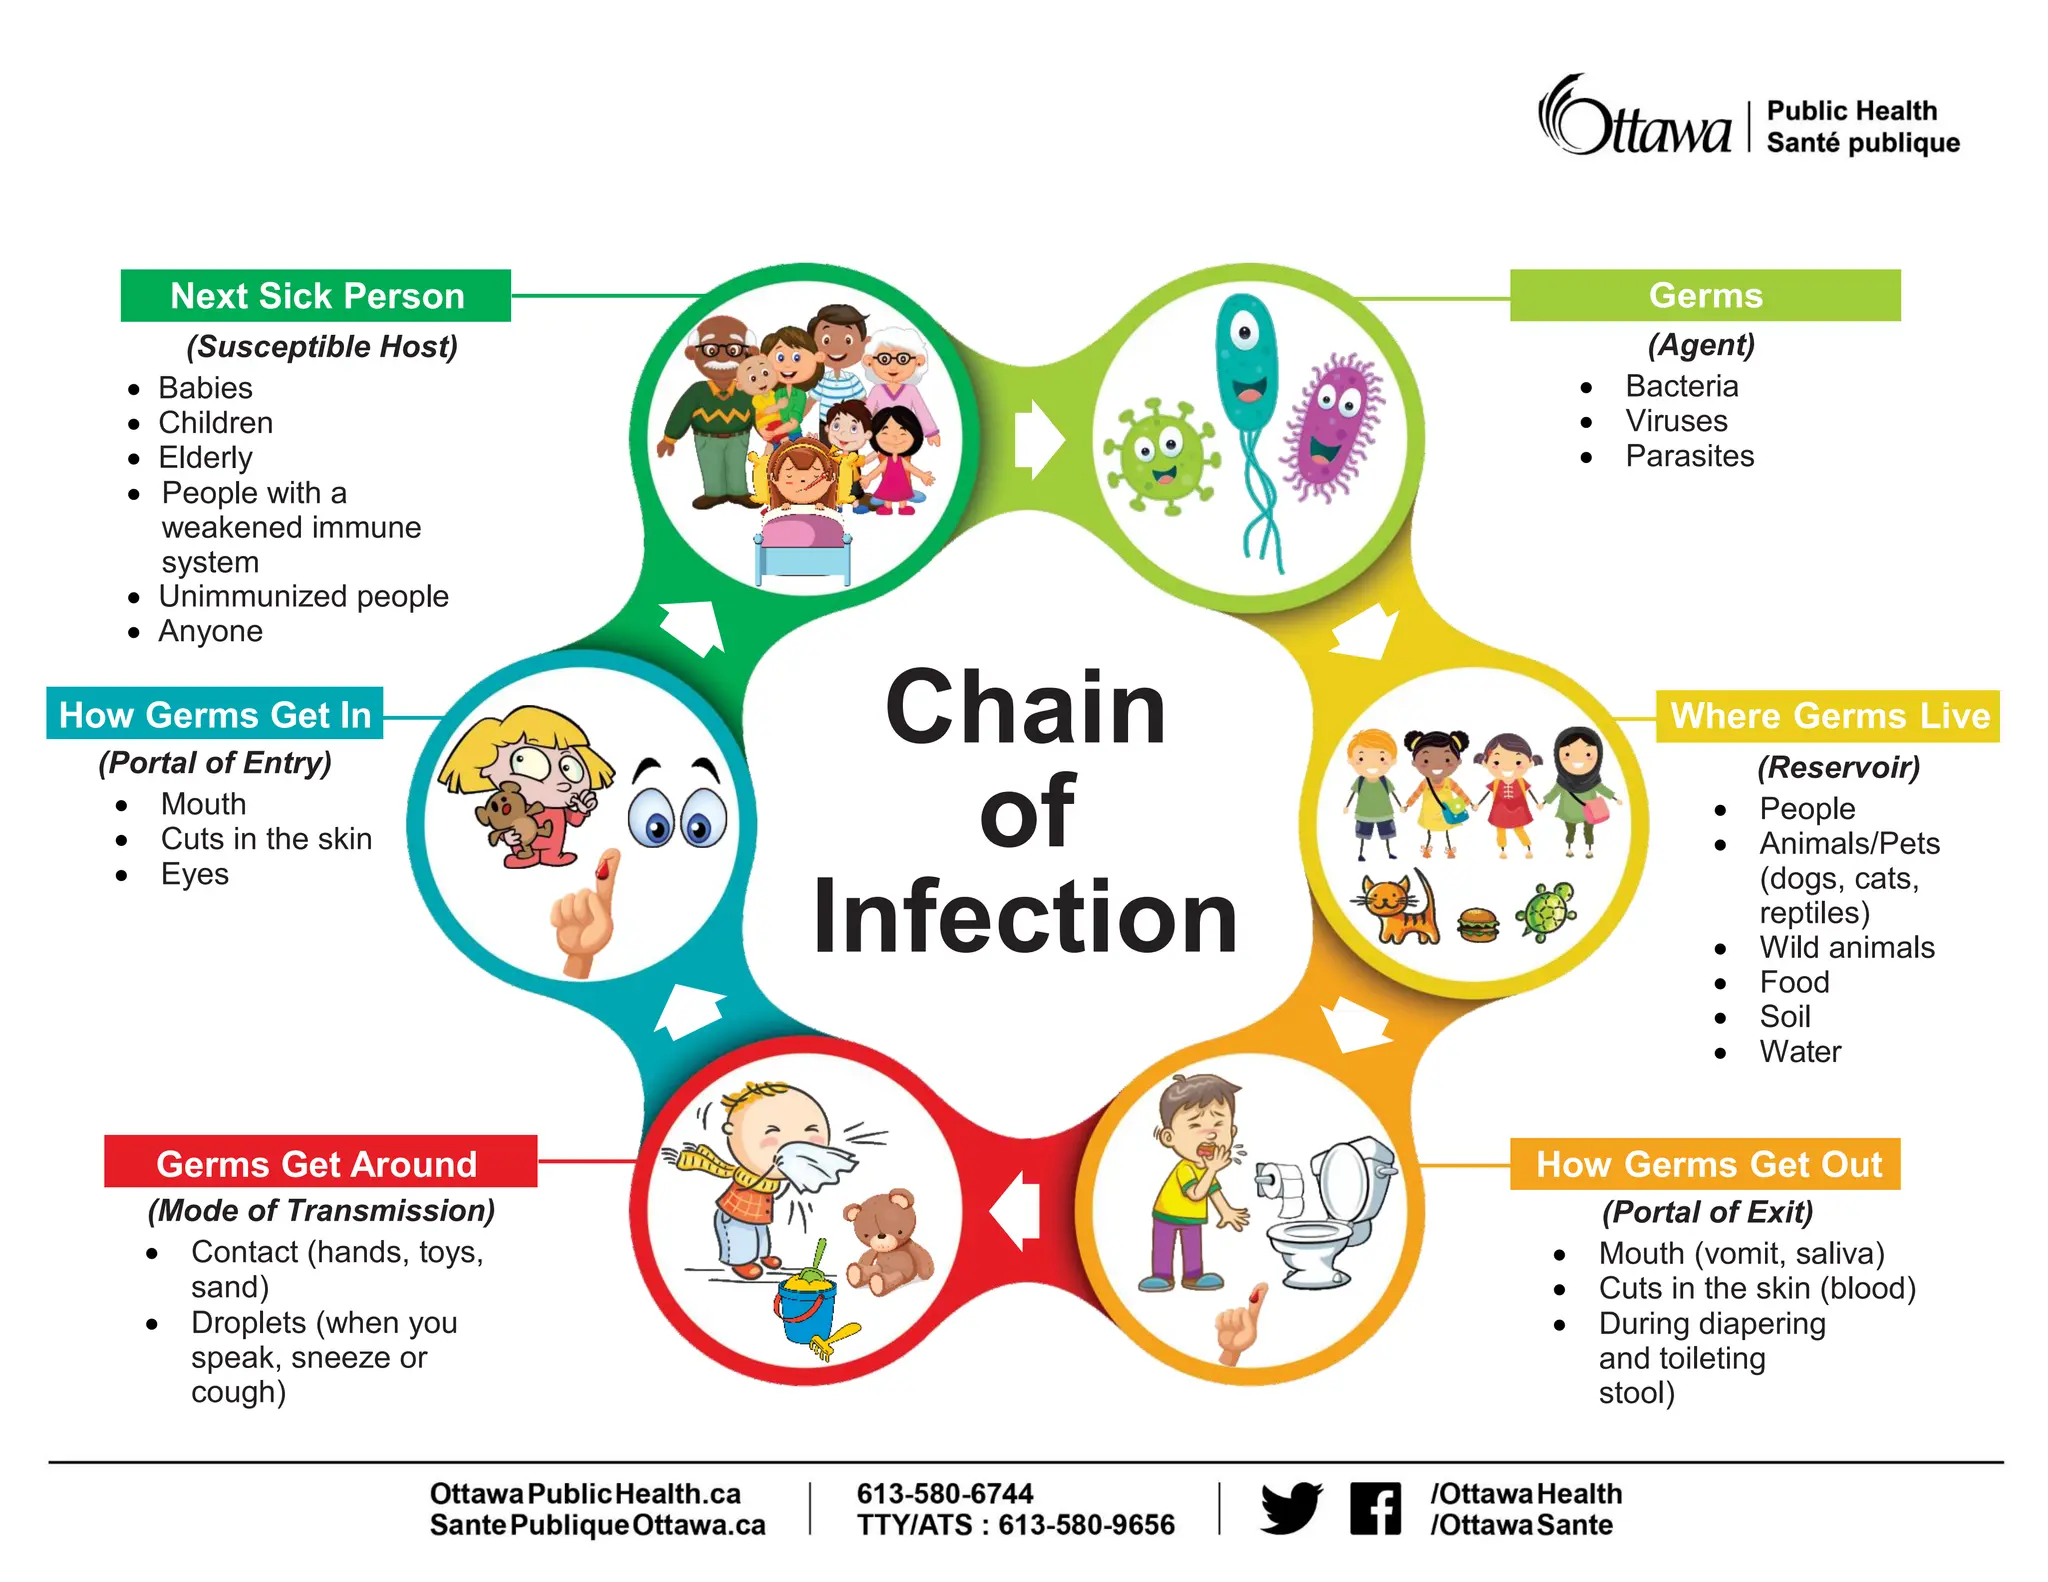
I spent three years troubleshooting infection clusters in long-term care facilities, and the single most frustrating thing about chain infection isn't that it's hard to define. It's that every chain breaks at a different link, and your standard protocol usually targets the wrong one. Let me explain how it actually works. A chain infection is a sequence where a pathogen moves from a reservoir through a portal of exit, into a mode of transmission, then gains entry through a new portal and infects a susceptible host. That's the textbook version. The version you see in practice involves patients, surfaces, airflow, and enough variables that no two chains look identical. I've watched a norovirus outbreak stall completely after someone stopped using cloth towels in a bathroom, and I've watched C. diff spread through a room despite terminal cleaning because the endoscope used for a colonoscopy hadn't been properly reprocessed between patients. The standard model treats these six links as equally breakable. They aren't. In hospital settings, the mode of transmission link — usually contact or airborne — accounts for roughly 60 to 70 percent of preventable infections. Focusing your intervention budget there gives you the most return. But many facilities still pour resources into educating staff about hand hygiene compliance, which only addresses the portal of exit and entry. Compliance rates look good on paper. The numbers don't move. I saw a facility hit 94 percent hand hygiene compliance and still run a MRSA cluster for eleven months because the real problem was shared blood pressure cuffs and pulse ox probes between rooms.
Here's the part nobody emphasizes enough: the reservoir link is often invisible. It's not a person. It's the sink drain in the ICU bathroom, the solution port on an IV pole, the fabric headrest in a imaging room. These reservoirs can maintain viable pathogen populations for weeks. I once tracked a Klebsiella outbreak back to the water trap under a sink that had never been disinfected because maintenance flagged it as "not a clinical surface." The sink was three feet from where nurses prepared medications. Took us six weeks and a full environmental culture audit to prove it.
How to Actually Break the Chain
Start by mapping the chain specific to your situation instead of applying a generic bundle. Every outbreak or cluster tells a different story. Map it before you intervene. I use a simple approach: identify the confirmed or suspected pathogen, trace the epidemiological link between cases by time and space, then test the likely reservoir and transmission route with environmental cultures. This usually takes a facility about two to four days depending on lab turnaround. Skipping this step and going straight to enhanced PPE or universal masking wastes time and rarely stops the chain. Once you know which link is actually passing the pathogen, you target it directly. If it's contact transmission via equipment, that means dedicated or properly reprocessed devices per patient. If it's airborne, that means negative pressure isolation and N95 fit testing, not just surgical masks. If the reservoir is the environment, that means cleaning and disinfection protocols matched to the organism's resistance profile. C. diff spores require sporicidal agents. Routine quaternary ammonium compounds won't touch them. I've seen facilities use the wrong disinfectant for three weeks during an active C. diff surge and wonder why the incidence kept climbing. Surveillance is where most places fall short. Routine passive reporting misses clusters until they're already large. Active surveillance culturing high-risk patients on admission and weekly thereafter catches the chain earlier. The added lab cost is real but modest. In my experience, the cost of one detected outbreak — lost beds, isolation rooms, potential public health notification — dwarfs the surveillance expense. A typical mid-size hospital might spend an extra $8,000 to $15,000 annually on active surveillance and save six figures in outbreak containment costs.
Get the Full Details

Where This Approach Falls Apart
Chain infection analysis assumes you can identify the pathogen and trace contacts accurately. That breaks down with asymptomatic carriers, slow-growing organisms with long incubation periods, or when patient movement between units isn't documented. I worked a case where a patient transferred from a community hospital carried an unfamiliar ESBL-producing organism. The receiving facility didn't know until day five, by which time three other patients on the same floor had developed positive cultures. Contact tracing was useless at that point. The workaround was implementing targeted genomic sequencing for unusual pathogens, which reduced identification time from days to hours, but not every facility has that capacity or budget. Another limitation: chain analysis doesn't account for behavioral drift. Protocols work when implemented consistently. They stop working when staff are short-staffed, when turnover is high, or when the protocol requires more steps than people have time for. I've seen perfectly designed isolation protocols fail because donning and doffing PPE took eight minutes and nurses were already behind on their assigned patients. The chain wasn't broken by bad science. It was broken by workflow reality. The most reliable way to reduce chain infections long-term isn't a single intervention. It's layered. Engineering controls like proper ventilation and sink design. Administrative controls like staffing ratios and isolation protocols. PPE as the last line, not the first. When you rely on PPE alone, you're betting that every person follows every step correctly, every time. They don't. The data supports that. Layering reduces the chance that any single failure lets the chain through.