Anterior MI Isn't Just Another Heart Attack
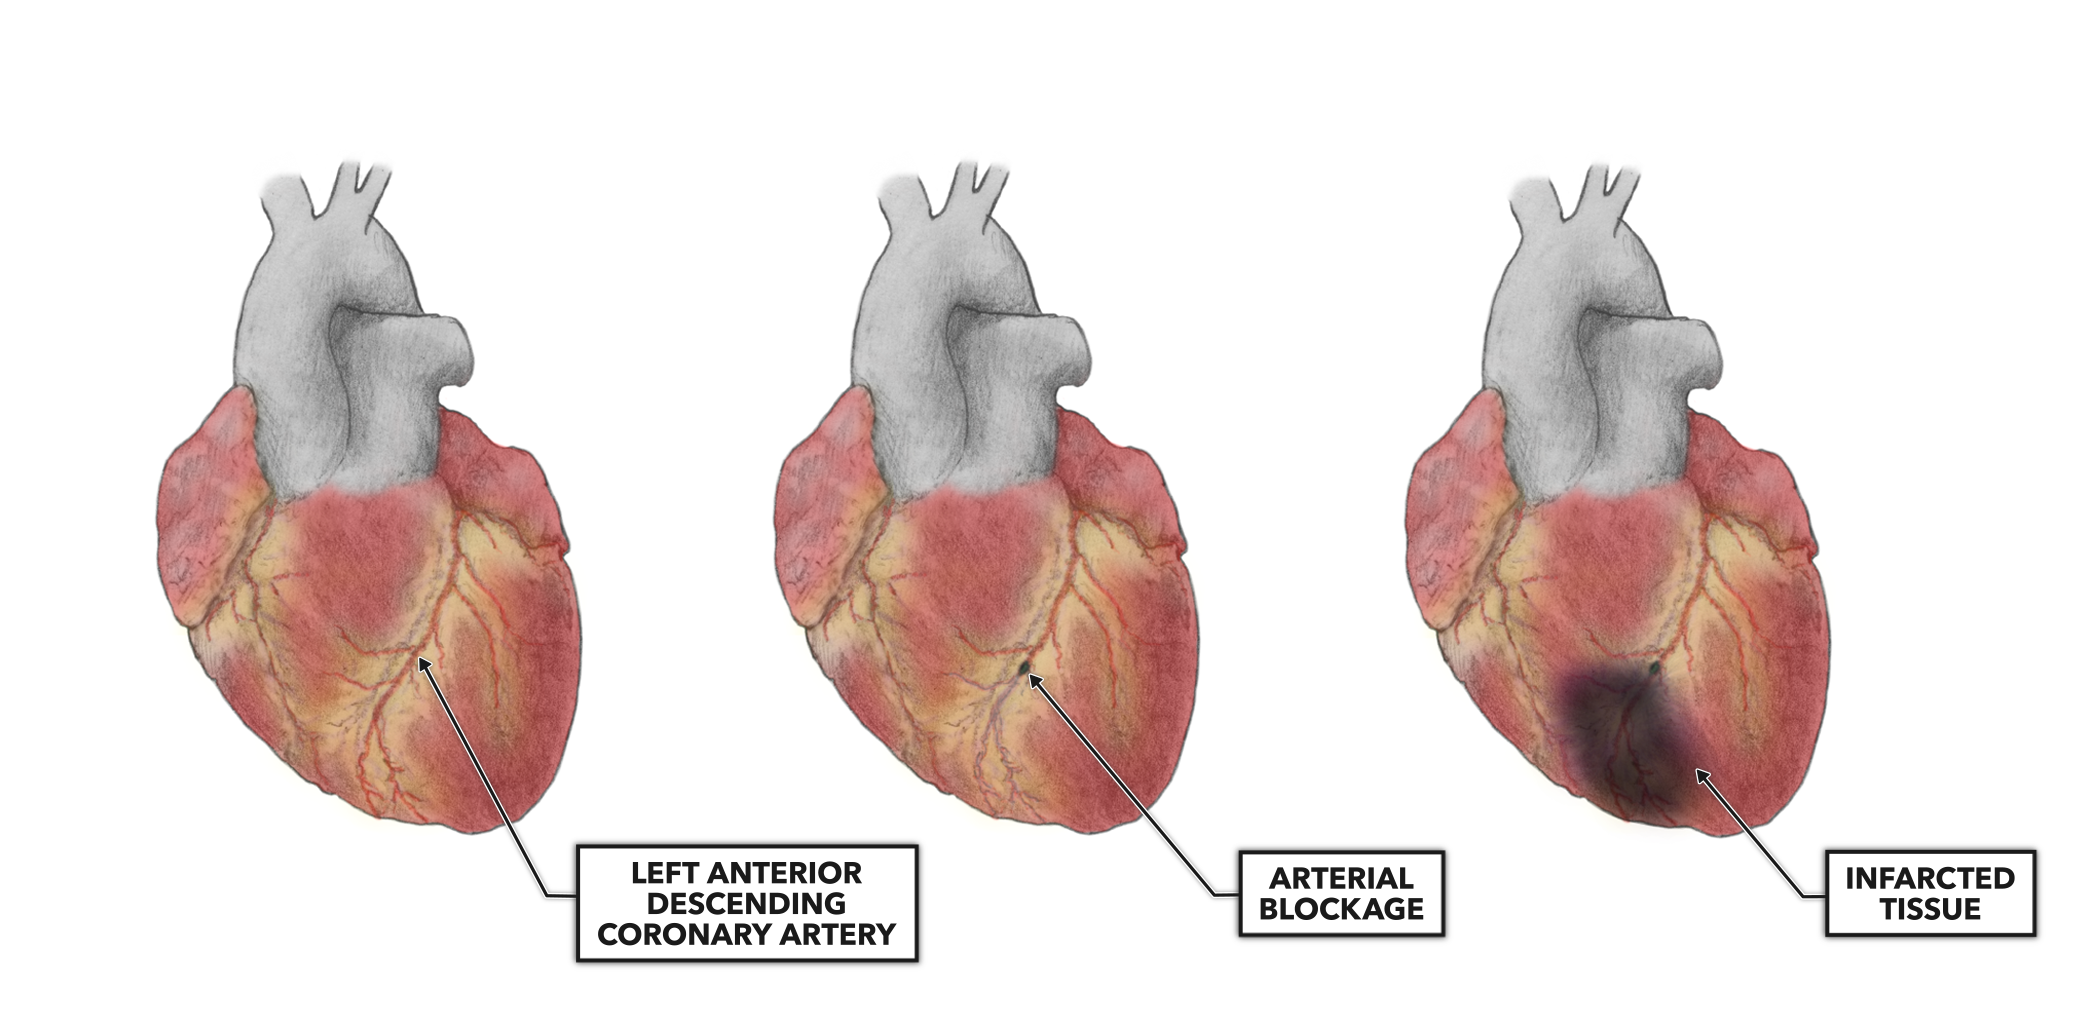
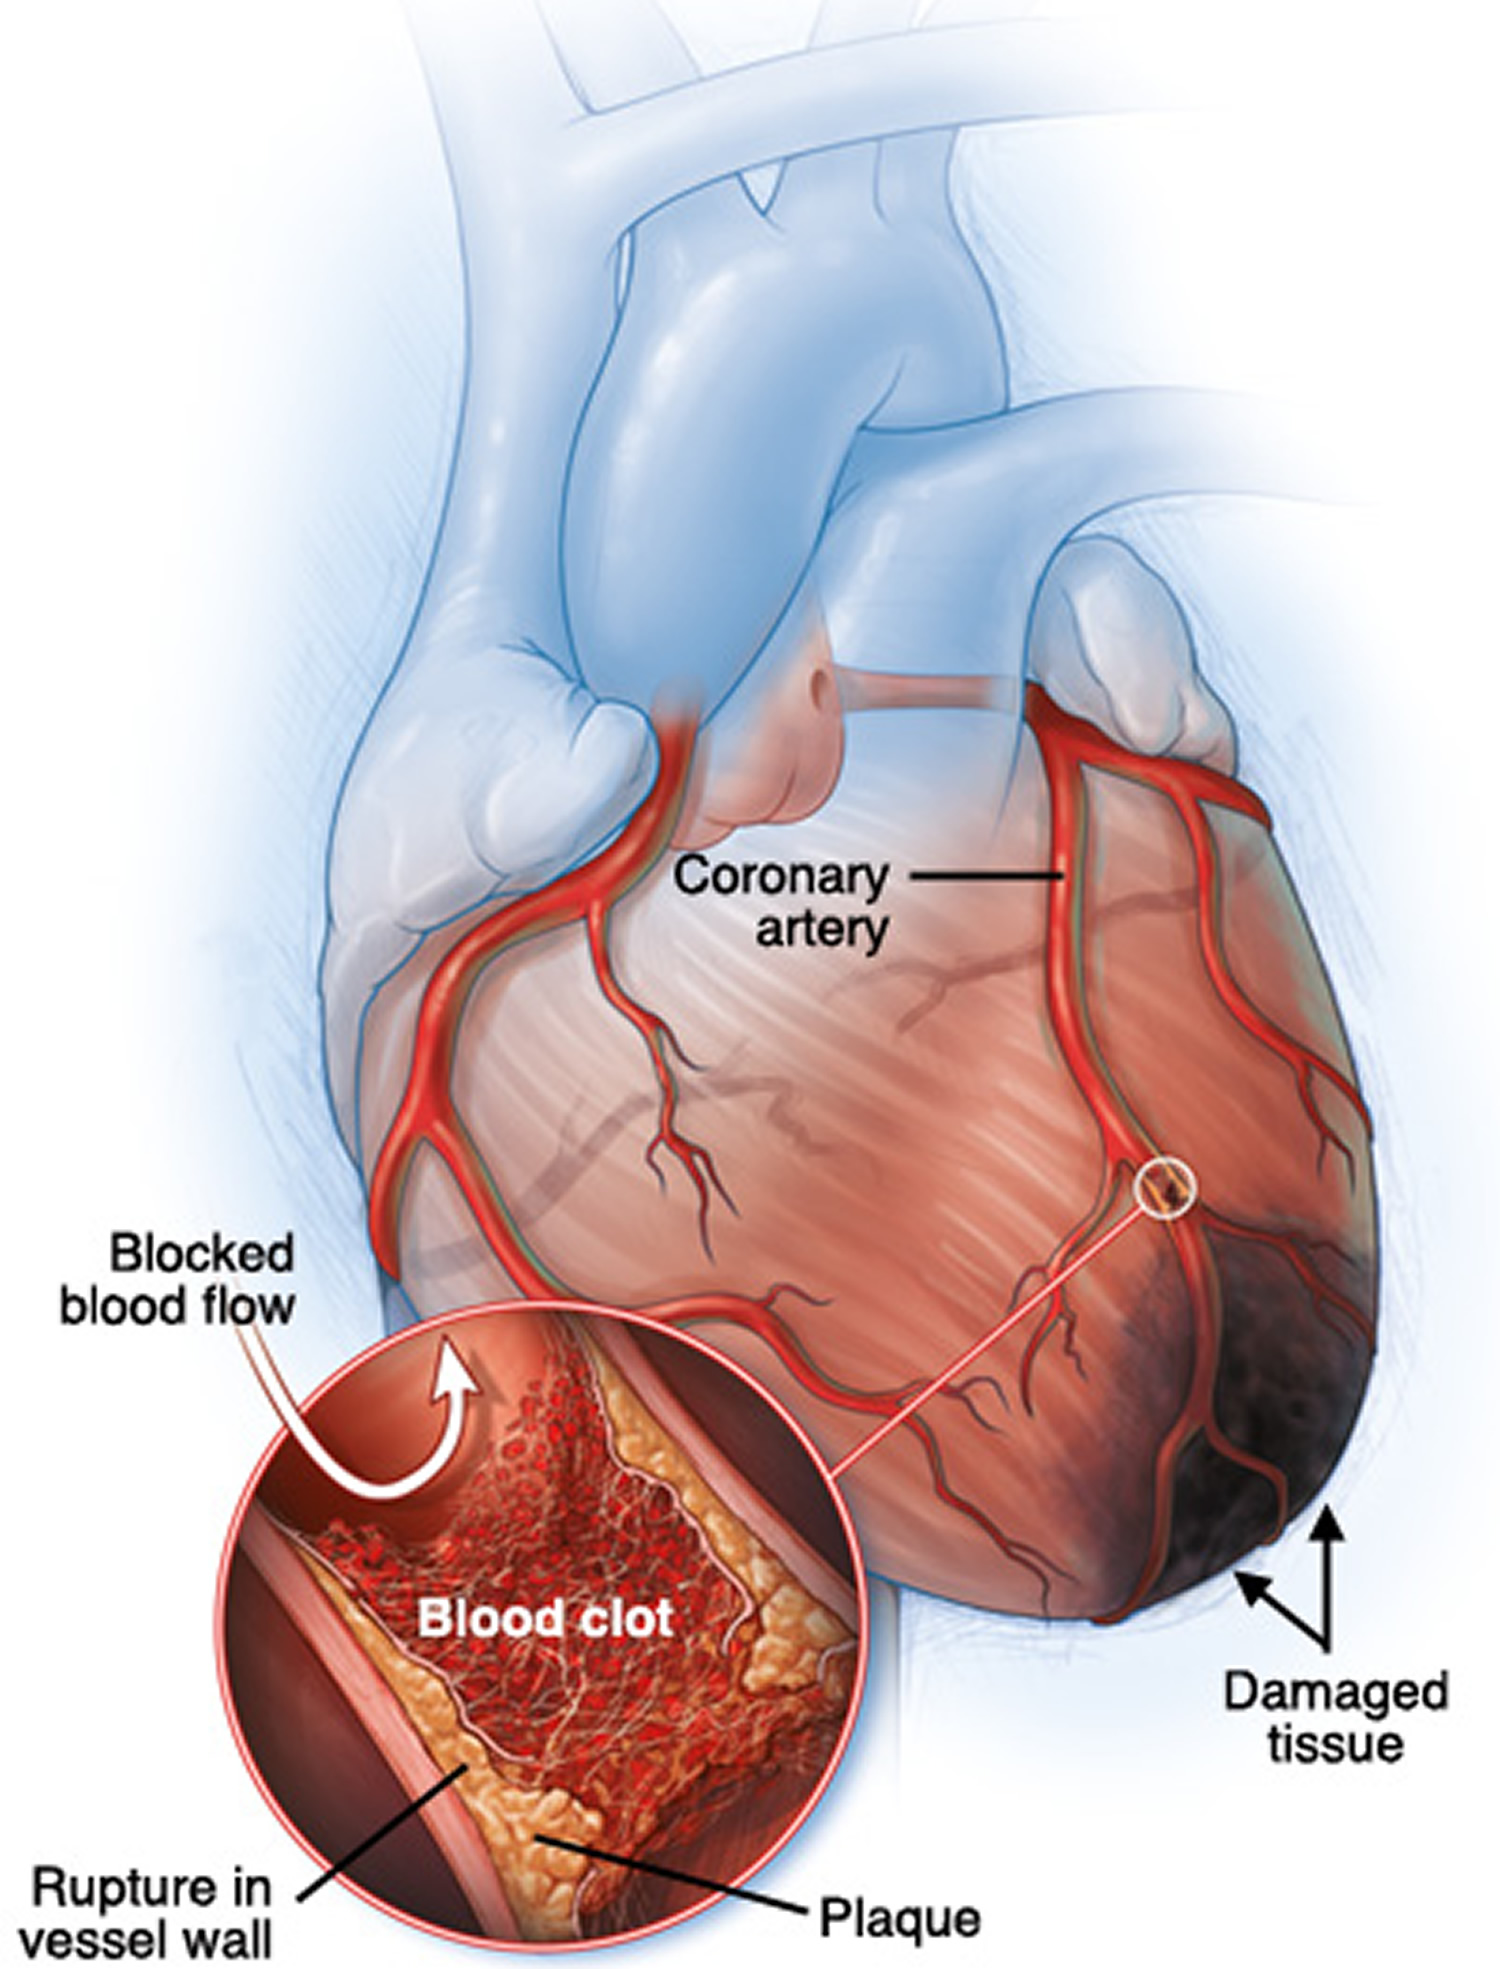
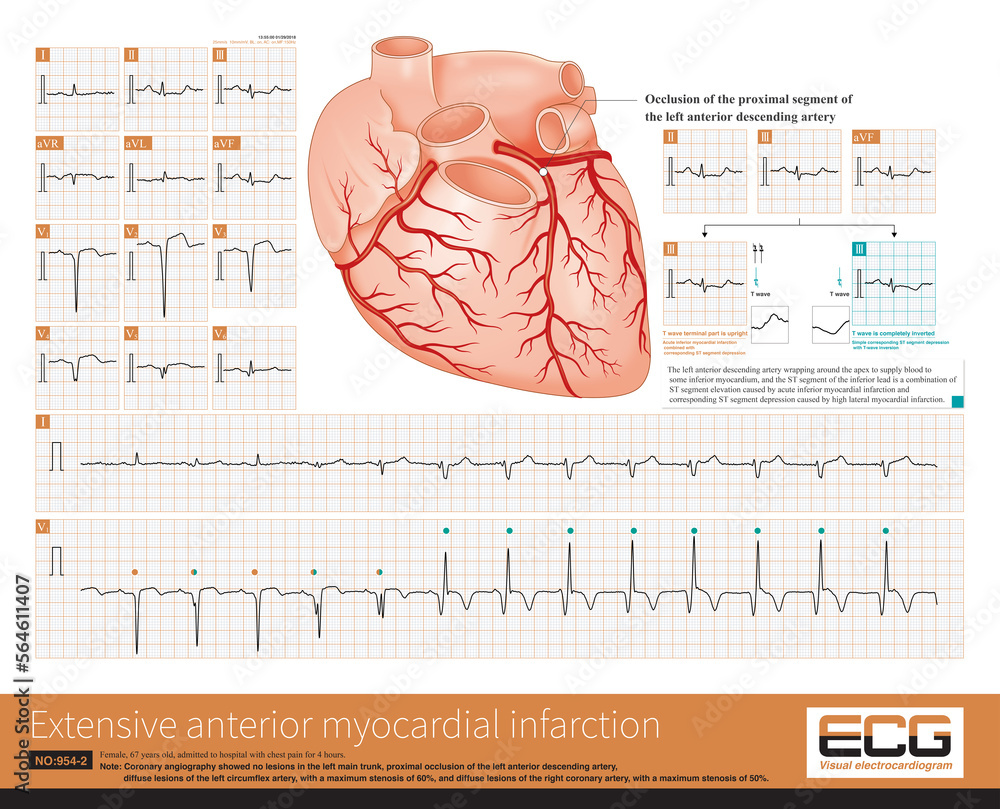
I've seen enough anterior MIs to know they tend to make trouble for people faster than inferior or lateral ones. The LAD feeds a big chunk of the left ventricle. When it shuts down, the mechanics of pumping take a serious hit. You don't always get the textbook chest pain either. Some patients present with just diaphoresis and nausea, or shortness of breath that they blame on anxiety. That's the part that gets people into trouble. The ECG pattern is usually ST elevation across leads V1 through V4, sometimes extending into V5 and V6 depending on how proximal the occlusion is. Proximal LAD lesions are worse because they knock out more myocardium. Distal occlusions can look milder on the surface but still cause significant dysfunction if they hit a critical septal branch. I had one patient last year where the ST changes were subtle in V2 and V3, barely meeting the formal criteria, but the troponin was already climbing fast. We took them straight to the cath lab anyway. The LAD was 99% blocked with a thrombus that looked like it had been there for hours. The lesson here is that formal ST criteria are a guideline, not a gate. Complications are where anterior MI earns its reputation. Right ventricular involvement is rare since that's usually a right coronary artery problem, but posterior MI can occur with LAD disease and complicate the picture. Cardiogenic shock happens in roughly five to ten percent of cases, higher if reperfusion is delayed. Arrhythmias are common too. Ventricular fibrillation in the first hour is a real risk, which is why rapid identification matters more than perfect ECG interpretation by the time limit.
One thing people miss is that wall motion abnormalities on echo after an anterior MI tell you more than the initial ECG alone. If you're seeing hypokinesis or akinesis of the anterior septum and apex, you're looking at significant damage even if the patient stabilizes after PCI. I usually get a bedside echo in the cath lab after they open the vessel, and that information changes how aggressively I manage fluids and inotropes going forward. Patients with preserved EF afterward still need close follow-up because late complications like LV aneurysm or mural thrombus can develop weeks later. The real hidden danger is outpatient complacency. People feel better after the procedure, the stent is sitting nicely on angiography, and they assume they're done. Anterior MIs carry a higher long-term heart failure risk than many other MI types. I've had patients return months later with worsening exertional tolerance and mild leg swelling because their ejection fraction declined gradually. The initial infarct size matters, but so does remote myocardial remodeling, and that's something that doesn't show up on discharge summaries. If you're managing a patient with anterior STEMI, don't wait for all the lab values to come back before activating the cath lab. Door-to-balloon time under ninety minutes is the benchmark, and every delay beyond that adds dead myocardium. Thrombolytics are an option if PCI isn't available within that window, but they're less effective for completely occluded LADs compared to some other vessels. I've seen lytic therapy fail in proximal LAD occlusions where the thrombus was dense and organized, and the patient ended up with a larger infarct than if they'd gone straight to the lab.
Medication-wise, dual antiplatelet therapy is standard, but the choice between ticagrelor and clopidogrel matters more than most guidelines suggest. Ticagrelor works faster and more reliably in anterior MIs where high platelet reactivity is common. Clopidogrel resistance is a real problem, especially in diabetic patients who often present with these infarcts. I check platelet function in high-risk cases when I can, though that's not always practical in smaller hospitals. Beta blockers should be started early unless there's a contraindication like bradycardia, hypotension, or active heart failure. ACE inhibitors are non-negotiable for anterior MIs regardless of EF, because they slow remodeling. I've seen too many patients leave the hospital without an ACE inhibitor and then struggle with progressive dilation over the next six months. Statins belong in the mix too, high intensity, started before discharge. The follow-up plan needs to be specific. Echocardiogram within two weeks to establish baseline function. Cardiac rehabilitation referral is essential, not optional. And patients need to understand that returning to normal activity too quickly after a large anterior MI isn't smart, even if they feel fine. Sudden physical stress in the first month can trigger arrhythmias in the healing myocardium.
Get the Full Details
There's no perfect predictor for who will do well and who won't after an anterior MI. Troponin peak, TIMI flow after intervention, and EF on discharge echo give you a rough idea, but individual variation is huge. Some patients with massive anterior infarcts recover remarkably well, while others with smaller infarcts develop significant dysfunction. The best approach is careful monitoring, early evidence-based treatment, and honest conversations with patients about what the recovery trajectory might look like.