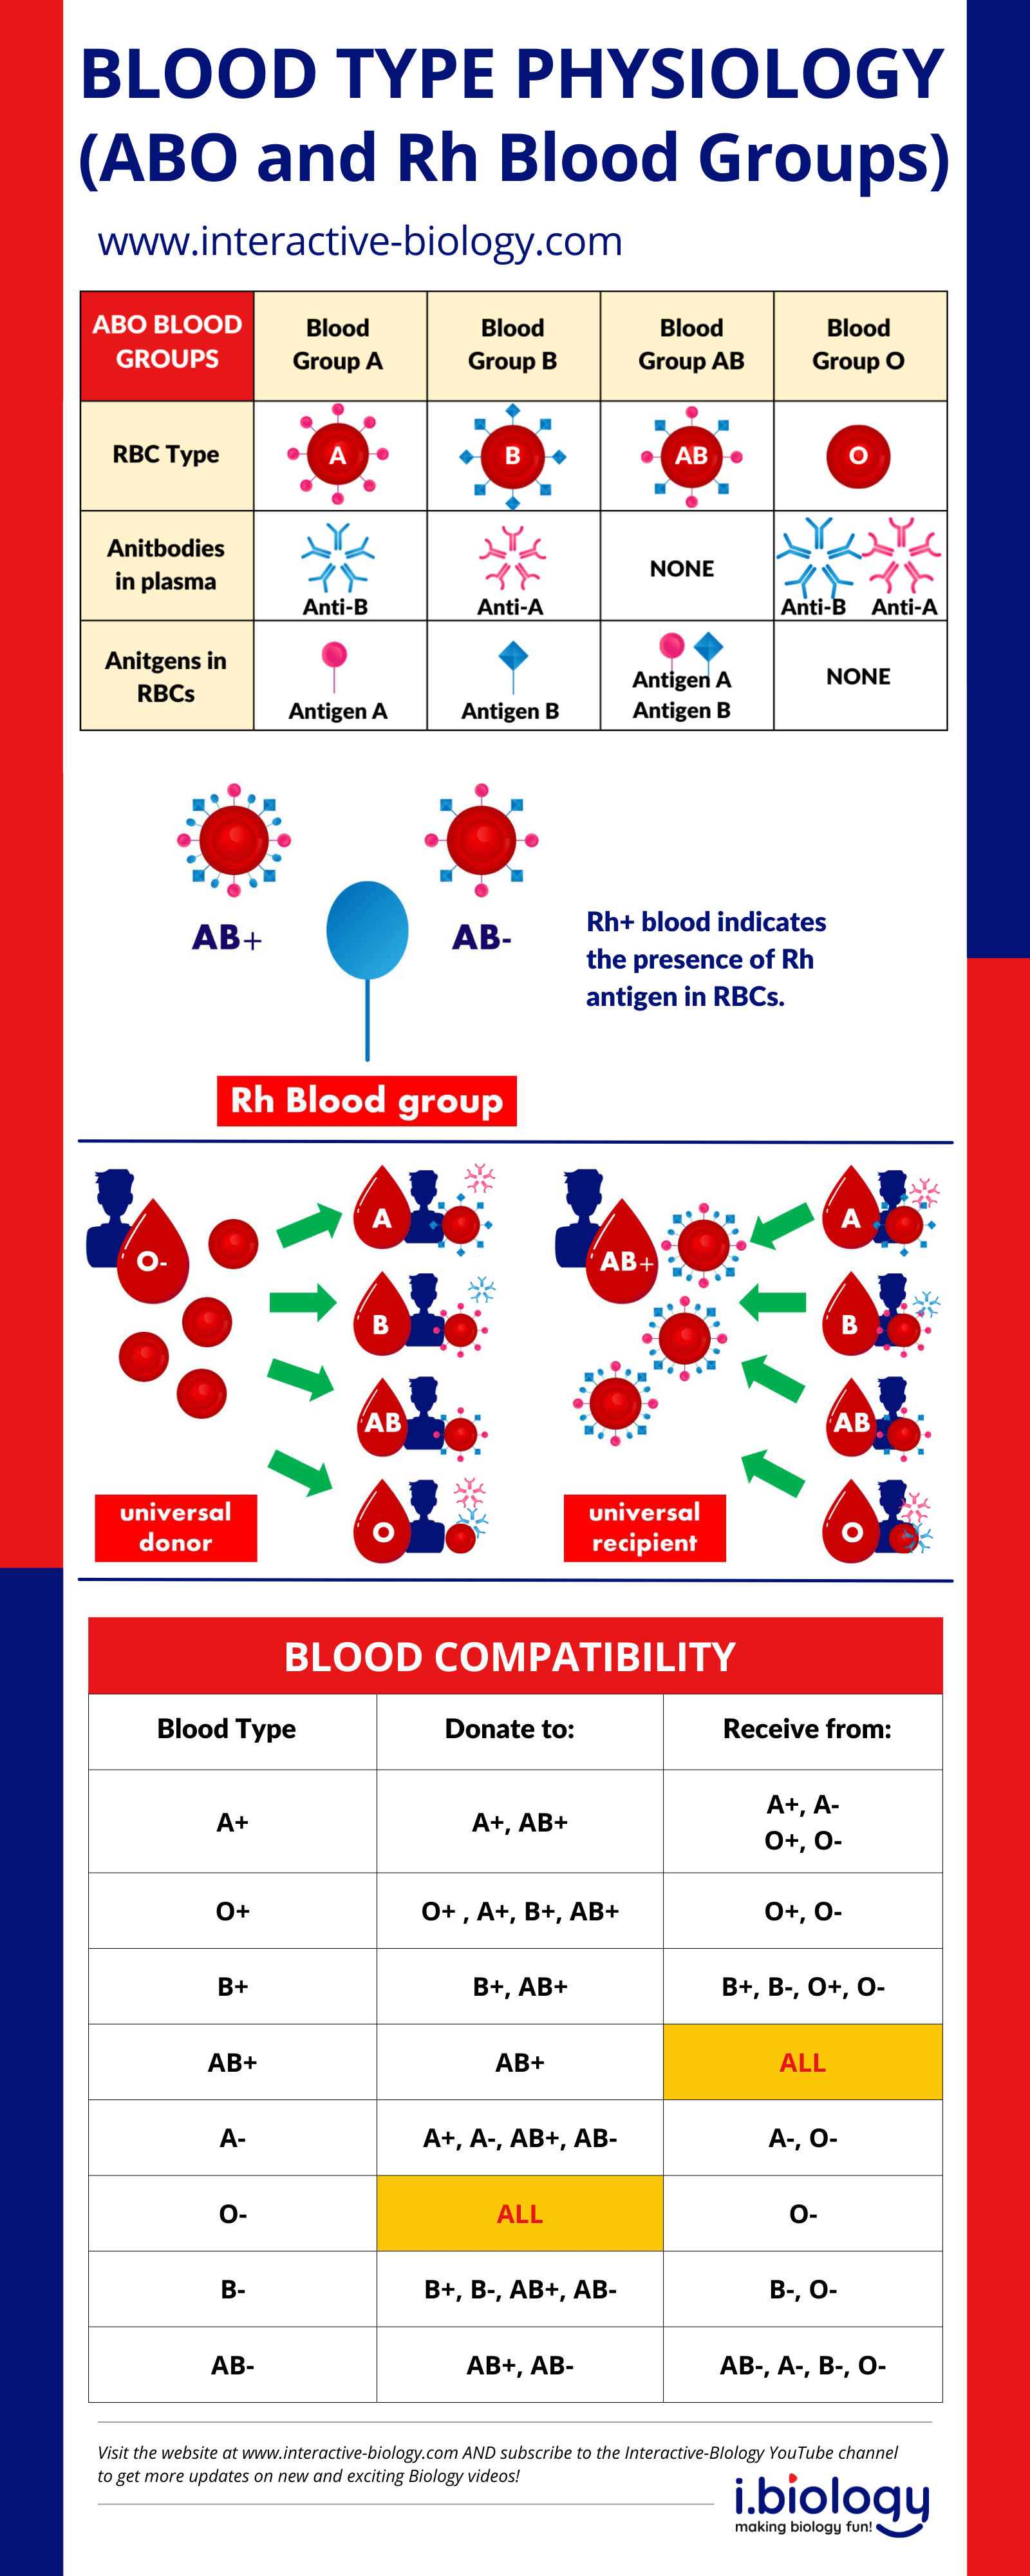
What Actually Happens When We Talk About Blood Groups
Blood typing isn't some mysterious science. It's a straightforward antigen test that has been around since 1901, when Karl Landsteiner figured out that red blood cells carry surface markers your immune system will happily attack if they don't match. The whole system boils down to two main types — ABO and Rh — and the way they interact in practice is less clean than textbooks make it look. I spent about eight years working in a transfusion medicine lab before moving into diagnostics consulting. The stuff that matters isn't in the basics. It's in the edge cases that show up at 2 AM when someone needs a transfusion and the screening doesn't line up the way everyone expected.
The Hidden Code In Our Blood Understanding Blood And Blood Groups
That phrase sounds dramatic but it's just shorthand for what we already know: your blood type is encoded genetically, inherited from your parents, and it determines compatibility for transfusions and transplants. The ABO system has three main alleles — A, B, and O — while the Rh system centers on the D antigen. That's the core. Everything else is variation and exceptions. Standard forward typing uses anti-A, anti-B, and anti-D reagents on a patient's red cells. Reverse typing checks the patient's plasma against known A and B red cells. If both sides agree, you have your type. Done. In practice, you're looking for agglutination — visible clumping that tells you which antigens are present or which antibodies are circulating. Strong reactions are easy to read. Weak or partial reactions are where things get real.
What People Miss About Blood Typing
Most guides stop at A positive, B negative, and so on. They don't tell you about subgroups. A people aren't all the same. A2 and A2B are common variants that can cause problems during crossmatching. An A2 individual can form an anti-A1 antibody, which means transfusing A1 red cells into them could trigger a hemolytic reaction. You'd only catch that if you were specifically testing for it, not from a routine type-and-screen. Another thing nobody emphasizes enough: weak D. Some people carry a variant RhD gene that produces a weakened version of the D antigen. Standard typing might call them Rh negative, but they're technically positive. If they receive Rh positive blood, they can develop an immune response. If they're pregnant and classified as negative when they should be positive, they won't get Rhogam when they need it, and a subsequent pregnancy with an Rh positive fetus could result in hemolytic disease of the newborn. Testing with an anti-D immunoglobulin reagent at the indirect antiglobulin phase catches these cases about 95 percent of the time.
Get the Full Details

A Real Problem I Handled
We had a patient who was typed as O positive on routine testing. Her screen was negative. Everything looked fine until we needed to transfuse and the crossmatch came back incompatible. Three different units, all reactive. We traced it to a warm alloantibody against a high-frequency antigen in the Kidd system — anti-Jk3. This person had been exposed through a prior pregnancy or transfusion and had no compatible blood in our inventory because the antigen is present in roughly 99.7 percent of the population. The workaround was calling our regional reference lab in New York. They ran a molecular panel and identified the exact antibody. We then sourced phenotyped donor units from the American Red Cross special donor registry. It added about five hours to the process. In an emergency situation like that, you don't have five hours. You have to weigh the risk of a delayed hemolytic reaction against giving the patient something with a minor incompatibility. That call is never comfortable.
Phenotyping And Genotyping Are Different Things
Phenotyping looks at what antigens are actually on the red cell surface. Genotyping looks at the DNA. Most blood banks do phenotyping because it's faster and cheaper. But genotyping is catching up, especially for patients who've been transfused multiple times and whose cells are coated with donor blood. When you're mixed field positive or your phenotype doesn't match your history, genotyping cuts through the noise. It tells you what the patient's genetics actually are, independent of what's currently floating in their bloodstream. One nuance worth knowing: genotyping can't detect acquired or weak expressions that phenotyping picks up. So the best approach is usually both. Sequence the DNA, then confirm with serology. It takes longer and costs more, but it prevents the kind of mismatch that shows up only after a transfusion reaction.
Limits Of What Blood Typing Can Tell You
It can't predict how well a transplant will be accepted. It can't identify every antibody in a patient's serum. It can't guarantee compatibility beyond the major ABO and Rh systems. And it absolutely cannot account for the minor antigen systems — Duffy, Kell, MNS, Kidd, and about a dozen others — without additional specialized testing. If someone is telling you a standard blood test covers all compatibility concerns, they're wrong. There's also the issue of acquired B antigen. Some patients with gastrointestinal issues or certain bacterial infections develop an enzyme that modifies their A antigens, making them appear as B. Standard reverse typing would show an unexpected reaction, and you could misidentify the patient as AB instead of A. This is rare but it happens, and it's caused enough wrong-type transfusions to be worth tracking.

What To Do If You're Getting This Done Personally
If you're a patient being pre-transfused or preparing for surgery, ask whether extended phenotyping is part of your workup. Most hospitals do ABO and Rh plus a screen for common antibodies. Extended panels cover about twelve clinically significant antigens. That's better than nothing but still incomplete for people with sickle cell disease or thalassemia who get transfused regularly. Those patients need full antigen matching, ideally across all major systems, to prevent alloimmunization. Don't assume a home test kit gives you the full picture. The ones sold over the counter only check ABO and Rh. They won't catch weak D, subgroups, or any of the antibodies that matter in a real transfusion scenario. If you have a complex blood history, go through a proper lab. It's not a cost saving to cut corners here. The genetics are straightforward. The immunology behind it is not. That gap between the simple explanation and the actual clinical reality is where most problems come from.