Understanding Bone Architecture and What It Actually Does for You
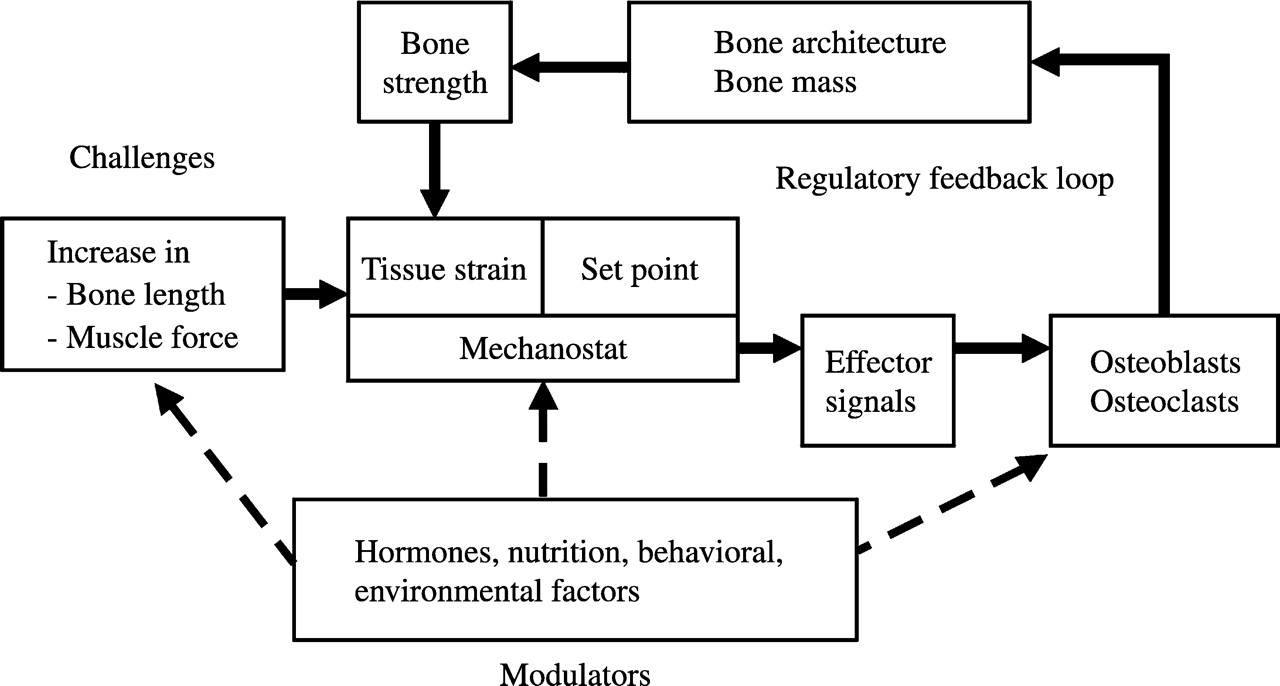
Most people think bone is just a scaffold. A rigid frame that holds everything up so you can move around. That's technically correct but wildly incomplete. Bones are dynamic organs. They remodel constantly, respond to mechanical stress, and their internal architecture is what determines whether you'll snap a hip at forty or make it to eighty without a fracture. I've spent years looking at CT scans and biomechanical models, and the thing that surprises most people is how much individual variation exists in trabecular orientation. Two people can have the same bone mineral density on a DEXA scan, and one of them will fracture under normal stress while the other walks away fine. The architecture underneath is what matters. Bone has two main structural components. Cortical bone is the dense outer shell. Trabecular or cancellous bone is the spongy interior found at the ends of long bones and within vertebrae. Wolff's Law describes how bone adapts to the loads placed upon it. This isn't new information, but the way these two structures interact mechanically is something I see misunderstood constantly in clinical practice. The trabeculae inside your bones orient themselves along lines of principal stress. This was documented by Wolf back in the 1800s, and modern micro-CT imaging has only confirmed it with much higher resolution. When you load a bone repeatedly in a particular direction, the trabecular struts thicken along those vectors. Remove the load, and they resorb. This is why astronauts lose bone mass in space, and why bedridden patients deteriorate so quickly. The architecture isn't fixed. It's a living record of the mechanical forces your body has experienced.
Here's where it gets counter-intuitive. Higher bone mineral density doesn't always mean stronger bone. I had a patient last year, sixty-two years old, with a DEXA T-score of negative two-point-one. By every standard metric, she was osteoporotic. But her quantitative CT scan showed well-preserved trabecular connectivity and good orientation patterns in her lumbar spine. She hadn't fractured. Meanwhile, I had a different patient with a borderline T-score who had degraded trabecular structure due to long-term corticosteroid use. The microarchitecture was compromised, and she went on to sustain multiple vertebral compression fractures over eighteen months. The density number told only half the story. This distinction between bone quality and bone density is the single most important concept in understanding osseous adaptation. Density is easy to measure. Quality requires advanced imaging that most clinics don't have access to. Trabecular bone score, or TBS, is one workaround that analyzes the texture of DEXA images to estimate microarchitecture, but it's an indirect measure with limitations. Direct assessment through high-resolution peripheral quantitative CT, or HR-pQCT, gives you actual trabecular number, thickness, and separation data. It's available at research centers and a growing number of specialty clinics, but it's expensive and not universally covered by insurance. The mechanical properties of bone depend on several architectural parameters. Number of trabeculae per millimeter. Their thickness. How connected the network is. Orientation alignment relative to the primary loading axis. When any of these degrade, fracture risk increases independently of what the density scan says. Corticosteroids are particularly brutal on trabecular connectivity because they preferentially affect the trabecular plates that run perpendicular to the main stress lines. This creates a specific vulnerability pattern that's different from what you see in age-related osteoporosis. Understanding this difference matters for treatment decisions.
I've also seen too many athletes and fitness enthusiasts approach bone loading with a one-size-fits-all mindset. Impact loading stimulates bone formation, yes, but the adaptation is highly site-specific. Running improves bone density in the lower extremities and spine. It does almost nothing for the proximal humerus. If you want comprehensive skeletal adaptation, you need multiplanar loading. Something like Olympic weightlifting or even martial arts training produces ground reaction forces and muscular pull from multiple directions, which drives trabecular reorientation across more anatomical regions than repetitive single-plane activities. There's a practical bottleneck here that people running into this topic usually hit. You can't consciously direct where your bone strengthens beyond what the loading pattern naturally dictates. The architecture responds to the stress environment it's in. You can influence that environment through training selection, but you can't micro-manage trabecular growth in a specific region without directly loading it. This is why cross-training isn't just a general health recommendation. It's a targeted skeletal adaptation strategy. Another overlooked factor is the role of marrow cavity size and endosteal remodeling. As people age, the medullary cavity expands through resorption on the inner cortical surface. This increases the moment of inertia disadvantage because bone material moves farther from the neutral axis but the total cross-sectional area decreases. The net effect is reduced resistance to bending and torsional loads. This happens even when cortical density appears stable on standard imaging. The geometry change alone compromises strength significantly.
Get the Full Details

For anyone working through this topic practically, the actionable takeaway isn't dramatic. Maintain mechanical loading across multiple planes throughout adulthood. Prioritize activities that challenge your skeleton from more than one direction. Get a bone density test if you're in a risk group, but understand its limitations. If your results are borderline or you have specific risk factors like steroid use, ask about complementary assessments. Trabecular bone score from your existing DEXA is a reasonable first step. HR-pQCT or quantitative CT with trabecular analysis is more informative if accessible. And if you're designing a training program around skeletal health, stop thinking about it as something you do for six weeks and expect permanent results. Bone adaptation tracks with sustained loading over years. Miss a few months, and the gains partially reverse. Maintain consistent multiplanar stress, and the architecture holds. That's the actual mechanism, not some quick fix or supplement regime. The bone will tell you what it needs through adaptation, but only if you keep giving it the right signal consistently.