What Actually Happens When You Type This Sentence
Your fingertip is doing something ridiculous right now. You probably never noticed it. A tiny nerve ending packed into a circle of skin — one of those Meissner corpuscles — is sending signals back to your brain at roughly 30 meters per second. At the same time, a flexor tendon running from your forearm is holding your fingertip against the keyboard with maybe two newtons of force, and a piece of bone no bigger than a grain of rice is transmitting pressure to receptors deep inside the joint. All of this happens before your conscious brain even registers what key you just pressed. I spent about six months working through cadaver dissections and then another few years in a hand therapy clinic trying to understand why some people recover fine motor control after tendon repair while others never get it back, even when the surgery looked perfect. That question — the gap between anatomical success and functional reality — is where the real architecture lives.
The Hidden Architecture Of Your Fingertips How Bone Nerve And Tendon Create Human Dexterity
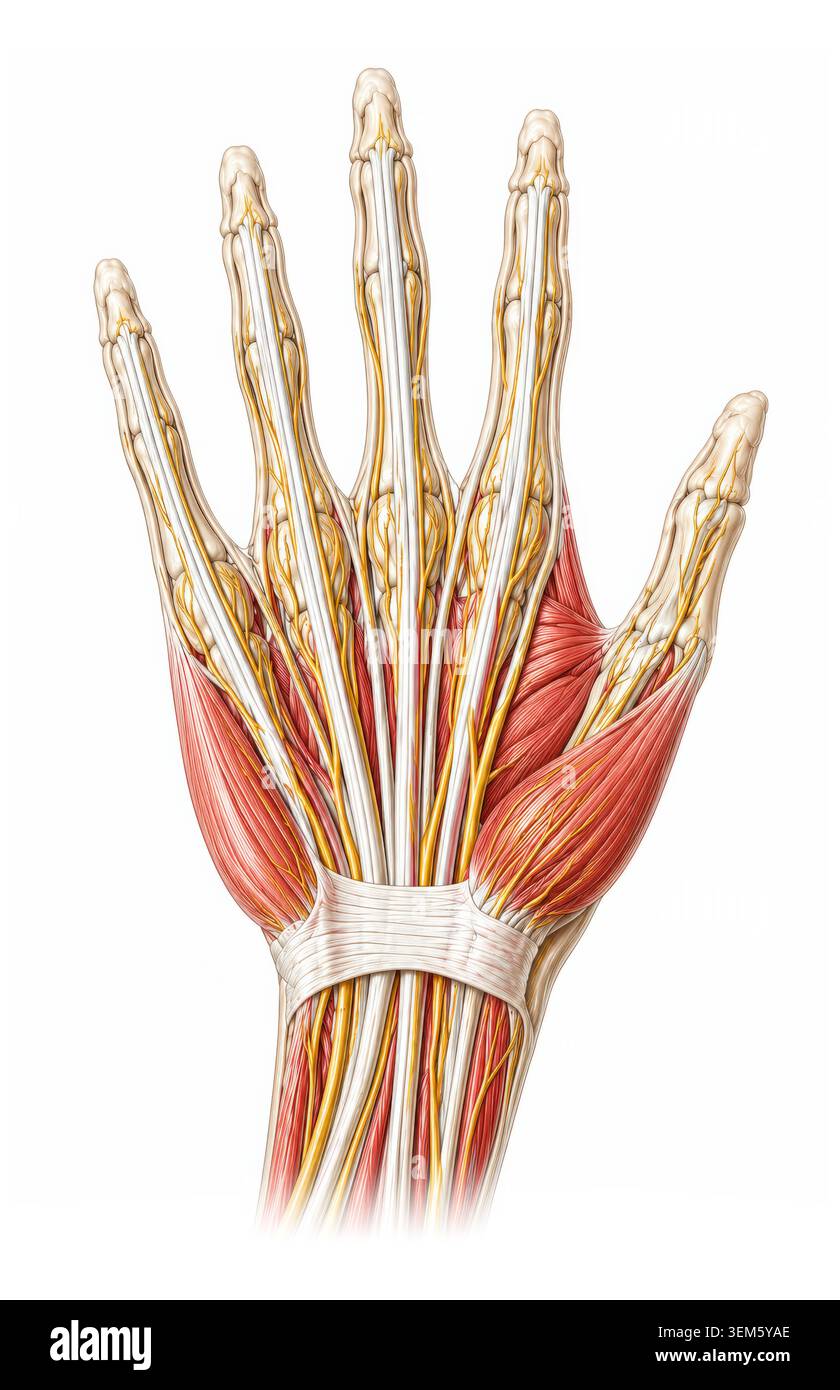
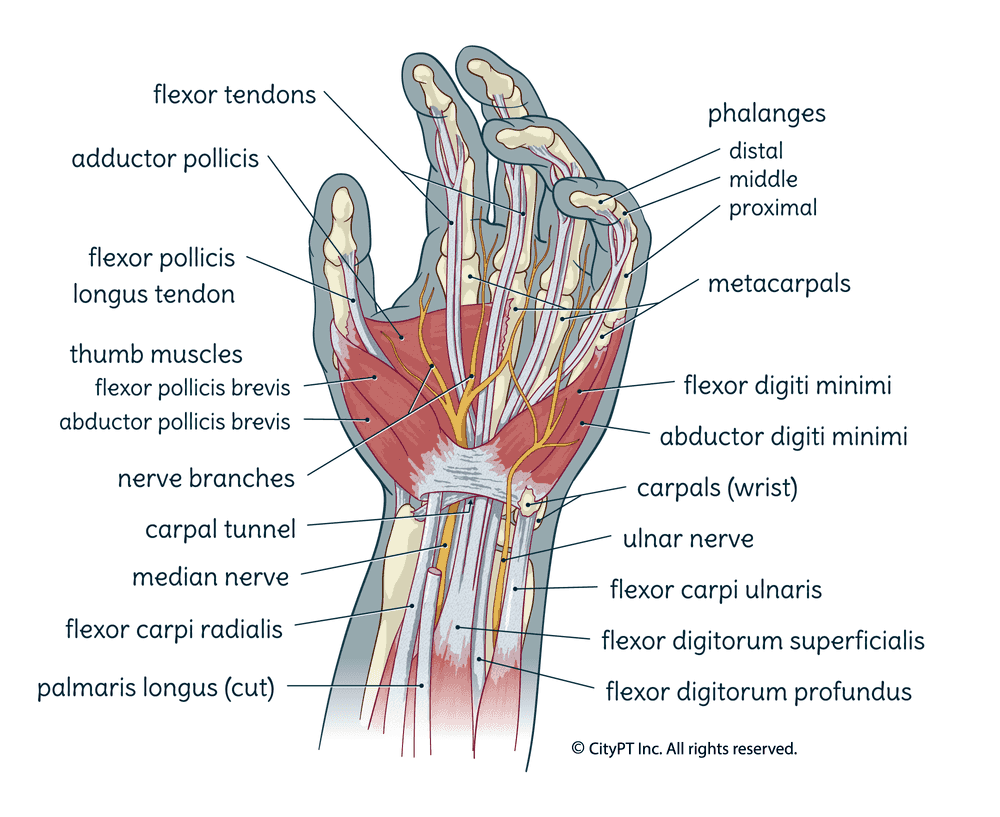
The bones in your fingers are short, rigid levers. The distal phalanx — the tip bone — is roughly 15 millimeters long in an adult. It has a broad, flat underside covered in dermal ridges. Those ridges aren't just for grip. They're structured to amplify vibrational signals. When your fingertip slides across a surface, the ridges create micro-vibrations at frequencies between 200 and 500 hertz that your nerves are specifically tuned to detect. This is why you can read braille. The ridges act as mechanical pre-processors, shaping the signal before it ever reaches the nerve endings. The tendons tell a different story. There are two main flexor tendons per finger. The flexor digitorum profundus runs all the way to the distal phalanx and bends the tip joint. The flexor digitorum superficialis attaches to the middle phalanx and bends the middle joint. They don't operate independently in most everyday movements. I ran into this repeatedly in clinic — patients who had isolated superficialis repairs would complain that their fingers felt "wrong" when they tried to make a full fist. The tendons share a common synovial sheath in the palm and lower finger. When one swells, it restricts the other. It's not intuitive. Most textbooks present them as separate systems. The extensor mechanism is even more complicated than people realize. The extensor tendon doesn't just attach to the back of the finger like a simple rope. It fans out into a complex arrangement of central slips, lateral bands, and oblique fibers that coordinate extension across all three joints simultaneously. If you've ever seen a mallet finger — where the tip of the finger droops because the central slip ruptured — you're looking at what happens when one tiny fiber in that fan loses its connection. The whole coordination breaks down.
I once had a patient who could type perfectly fine but couldn't pick up a penny from a table. The difference is pure biomechanics. Typing is a repetitive, open-chain motion with limited force requirements. Picking up a penny requires simultaneous pinch force, proprioceptive feedback, and coordinated flexion at the interphalangeal joints. The nerve density in your fingertip is about 100 sensory units per square centimeter. That's comparable to the lips. Your brain devotes roughly the same cortical area to your thumb and index fingertip combined as it does to your entire trunk. That's not a metaphor. It's the sensory homunculus, and it exists because dexterous manipulation is computationally expensive. Here's something most people don't know: the pulley system in your fingers. There are five annular and cruciate pulleys along each finger that hold the flexor tendons close to the bone. Without them, your tendons would bowstring — pull away from the finger when you flex, dramatically reducing your grip strength. A single A2 pulley rupture can reduce grip strength by up to 50 percent. I've seen athletes lose season-long grips from hook-style holds on climbing walls where the force on that pulley exceeds 120 newtons. The workaround isn't surgery always — sometimes it's taping the finger in a slightly flexed position to offload the pulley during healing. Straightening the finger completely puts maximum tension on the already-damaged pulley. That's counter-intuitive and it costs people months of recovery. The nerve supply comes from the median and ulnar nerves. The median nerve covers the thumb, index, middle, and half of the ring finger. The ulnar nerve covers the little finger and the other half of the ring finger. But the coverage isn't uniform. The tips have the highest concentration. Move two millimeters up toward the nail bed and density drops significantly. This is why finger numbness from repetitive strain or compression — say, from a poorly adjusted mouse — manifests as loss of fine discrimination first. You can still feel touch. You just can't tell if something is smooth or textured anymore.
Get the Full Details
One practical issue I dealt with constantly: patients with Dupuytren's contracture. The palmar fascia thickens and pulls the fingers into flexion. Early on, people try stretching exercises. They don't work well because the contracture is in the fascia, not the tendon. The tendons themselves are fine. The problem is the structural shortening of the connective tissue plane underneath the skin. What actually helps is needle aponeurotomy or collagenase injection — breaking down the affected fascia directly. Stretching a contracted Dupuytren's finger is like stretching a rubber band that's been left in the sun too long. It won't regain its original length because the material itself has changed. Another thing worth noting is the relationship between joint capsule integrity and dexterity. The joint capsules in your fingers are relatively loose to allow full range of motion, but that looseness means they rely heavily on the surrounding tendons and ligaments for stability. I've seen cases where people with hypermobility syndromes — things like Ehlers-Danlos — have perfectly functional hands until they develop early osteoarthritis in the distal interphalangeal joints. The capsules are so loose that the joints migrate slightly with repeated use, and that changes the tension lines of every tendon attached to them. Fine motor tasks become harder not because the nerves or muscles failed, but because the mechanical geometry shifted. If you're dealing with finger stiffness after an injury or surgery, the old advice was rest and elevation. That's mostly wrong now. Early controlled motion within pain limits produces better outcomes than immobilization for most flexor tendon repairs. The tendon glides through its sheath, preventing adhesion formation. The problem with complete immobilization is that the tendon fuses to the surrounding tissue. Once that happens, the tendon can't slide. No sliding means no flexion. Breaking those adhesions later usually requires another surgery. The tradeoff is that early motion risks re-rupture if you push too hard. The sweet spot is protocol-driven — usually starting with passive motion in the first week, then active motion around week three, and full resistance not before week six. Skipping steps is the most common mistake I see.
The blood supply to the fingertips runs along the sides of each phalanx in digital arteries. These are end arteries, meaning there's minimal collateral circulation. If one gets compromised — through trauma, vasospasm, or conditions like Raynaud's — the tissue distal to the blockage is at real risk. I worked with a patient who had significant numbness and color changes in his index fingertip after a seemingly minor laceration that he'd treated himself. He'd missed the artery. The wound healed. But the digital nerve and artery on the radial side of his index finger were damaged. He lost protective sensation in a strip about four millimeters wide along the side of his fingertip. He didn't know it until he burned himself on a stove and didn't feel it. That's the kind of damage that doesn't show up on a standard exam unless you're specifically testing single-discrimination two-point sensitivity. There's also the matter of the nail and its relationship to fingertip function. The nail isn't just armor. It acts as a counterforce against the fingertip pad. When you press your pad against an object, the nail prevents the pad from over-compressing, which maintains structural rigidity and improves precision. Remove the nail — medically, through avulsion — and you'll notice immediately that fine pinch tasks degrade. You can still grip. You just can't do the same level of precise manipulation. People don't think about this until it's gone. The intrinsic muscles of the hand — the lumbricals and interossei — are small but disproportionately important. They originate from the flexor tendons in the palm and insert into the extensor mechanism on the back of the fingers. Their job is fine-tuning: stabilizing the metacarpophalangeal joints while allowing the interphalangeal joints to flex and extend. Without them, you'd have to compensate with gross forearm muscle activation, which is slower and less precise. These muscles are what let you play piano or tie a knot. Loss of intrinsic function — from ulnar nerve damage, for example — produces the classic claw hand deformity where the ring and little fingers curl involuntarily. The balance between extrinsic and intrinsic muscles is disrupted.
I should mention the role of temperature. Fingertip dexterity drops noticeably below 20 degrees Celsius. Cold causes vasoconstriction in those end arteries I mentioned, reducing blood flow and slowing nerve conduction velocity. Each degree below normal body temperature slows conduction by about one to two meters per second. In practical terms, your typing speed and precision degrade measurably when your hands are cold. This is why musicians and surgeons worry about hand warmth. It's not superstition. It's physics. For anyone working through finger rehabilitation or trying to understand why their dexterity isn't returning after an injury, the most useful thing you can do is track specific functional milestones rather than relying on pain or swelling as indicators. Pain doesn't mean the tendon has healed. Swelling subsiding doesn't mean the pulley is intact. Standard tests like the Strahan extension test for flexor tendon integrity, or the pinch gauge measurement for tip strength, give you actual data. Anything less is guesswork. The whole system — bone levers, tendon pulleys, nerve endings packed into dermal ridges, joint capsules, intrinsic muscles — operates as one coordinated unit. You can fix one piece and the rest will expose the weakness elsewhere. That's why fingertip dexterity is such a fragile accomplishment and why it takes so long to rebuild after injury.