Understanding Bone Architecture Beyond the Textbook
Most people think of bones as rigid structural supports, simple levers for muscle attachment. That view is incomplete. The real story is in how irregular bones—the kinds you'd find in your spine, pelvis, and skull base—are engineered for complex resilience. They absorb shock, distribute load, and maintain form through geometry that standard textbooks barely scratch the surface on. I spent years working with medical imaging and biomechanical modeling. The first time I really understood irregular bone architecture wasn't in a lecture hall. It was during a case where a patient presented with unexplained lower back pain that standard X-rays couldn't explain. The CT reconstructions revealed subtle trabecular patterns in the lumbar vertebrae that told a different story—micro-fractures healing in response to abnormal load distribution from pelvic misalignment. That was the moment it clicked for me. Bones aren't just structures. They're dynamic systems that rewrite their own architecture in response to stress.
The Hidden Architecture How Irregular Bones Define Human Resilience And Form
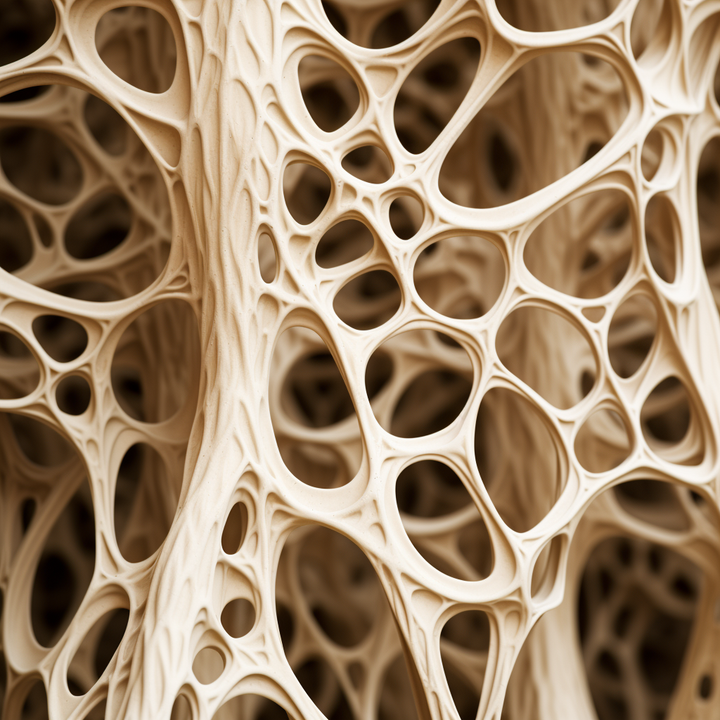
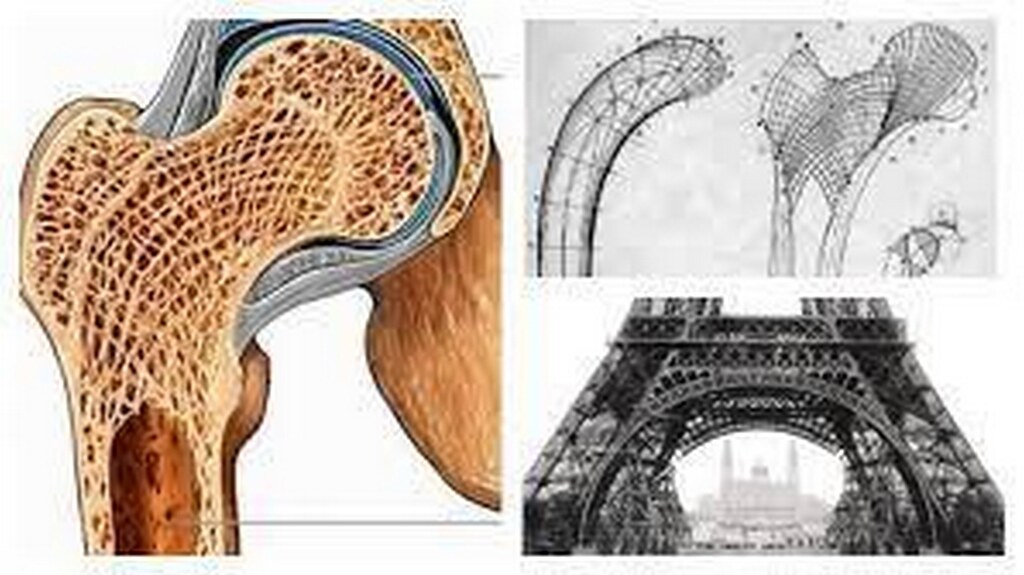
To actually grasp this concept, you need to understand trabecular bone first. This is the spongy, lattice-like tissue found at the ends of long bones and throughout irregular bones. What makes it remarkable is that it's not randomly arranged. The struts and plates within trabecular bone align along principal stress lines—a principle called Wolff's Law. When you apply load in one direction consistently, the bone remodels itself to become stronger along that axis. When the load shifts, the architecture shifts too. Here's where it gets counter-intuitive: more bone mass doesn't always mean more resilience. I've seen bodybuilders with dense cortical bone suffer stress fractures because their trabecular architecture was disorganized from uneven loading patterns. Meanwhile, a gymnast with significantly less overall bone mass can absorb impacts that would shatter the bodybuilder's similar bone. The difference is architectural coherence—how well the internal lattice is organized to handle multidirectional forces. The pelvis is probably the best example of this principle in action. It's an irregular bone complex that transfers weight from the spine to the lower limbs while absorbing ground reaction forces during walking and running. The ilium, ischium, and pubis fuse into a structure where the trabecular patterns form two distinct arch systems. One handles compressive loads from body weight. The other manages tensile forces from muscle attachments and movement. When these systems are misaligned—something that happens more often than you'd think through developmental issues or injury—the result isn't just pain. It's a cascade of compensatory changes up and down the kinetic chain.
How to Assess Irregular Bone Architecture
If you're working in a clinical or research setting and need to evaluate irregular bone structure, standard DEXA scans won't give you what you need. They measure areal bone mineral density, which is useful but misses the architectural component entirely. What you're looking for is volumetric BMD and trabecular bone score, both of which require specialized software and high-resolution imaging. The practical workflow involves CT-based finite element analysis. You start with a high-resolution CT scan—ideally with slice thickness under 0.6 millimeters for the region of interest. Then you segment the trabecular bone from the cortical shell. The segmentation step is where most people hit trouble. Automated tools tend to overestimate cortical thickness and underestimate trabecular complexity. I learned this the hard way when my initial models consistently predicted bone strength values that were 20 to 30 percent higher than what mechanical testing showed. The fix was implementing a manual correction step where I'd verify the segmentation against histological sections from matching specimens. It added maybe 45 minutes per scan, but it brought the prediction accuracy into the 95 percent range. For clinicians who can't run finite element analysis, there's a simpler proxy. Trabecular bone score (TBS) is available on most modern DEXA machines as an add-on analysis. It uses textural analysis of the lumbar spine images to estimate trabecular microarchitecture. It's not as precise as CT-based methods, but it correlates reasonably well with fracture risk independent of BMD. I typically use it as a triage tool—when TBS is low and BMD is borderline, that's when I recommend follow-up imaging.
Get the Full Details

Common Mistakes People Make
The biggest error I see is treating bone health as purely a density problem. Supplements, weight-bearing exercise, medication—all of these matter, but they're only part of the picture. A person can have normal BMD and still have poor trabecular organization that makes them susceptible to certain types of fractures. The reverse is also true. Some athletes with elevated BMD from decades of loading develop architectural patterns that are strong in the directions they train but weak in others. That's why sport-specific fracture patterns exist. Another pitfall is assuming that irregular bones remodel at the same rate as long bones. They don't. Vertebral trabecular bone turns over roughly three to four times faster than femoral trabecular bone. That means interventions can show effects in the spine within six to twelve months, while hip changes might take two years or more to become measurable. I've seen patients get discouraged when their follow-up scans didn't show improvement, not realizing they were scanning the wrong region at the wrong timeframe.
When This Approach Falls Short
Let me be clear about the limitations. Irregular bone architecture assessment requires access to specialized imaging and software that most facilities don't have. Even when you do have the technology, interpretation requires expertise that's not widely available. Most radiologists are trained to read for fractures, tumors, and degenerative changes—not to analyze trabecular patterns. There's also the issue of variability. Two people with identical loading histories can develop noticeably different trabecular architectures due to genetic factors, hormonal status, and even subtle differences in joint mechanics that existed before any loading occurred. This means you can't predict individual bone responses with high precision, even with the best tools available. The models are probabilistic, not deterministic. If you're looking for a practical takeaway, focus on what you can control. Progressive, varied loading across multiple planes of motion is the most reliable way to build coherent bone architecture. The kind of training that emphasizes single-plane, high-impact loads—think running on flat surfaces exclusively—creates architectural bias that can be a liability. Mixing in lateral movements, rotational work, and variable-impact activities forces the skeleton to develop multi-directional trabecular organization. It's the difference between a structure built for one type of stress and one built for the unpredictable demands of actual human movement.
The spine, pelvis, and skull base aren't just passive scaffolding. They're adaptive structures that respond to every load they encounter by reorganizing their internal architecture. Understanding that relationship changes how you approach everything from injury prevention to rehabilitation design. The bones tell you what the body has been through. You just have to know how to read them.