Why This Simulation Actually Matters
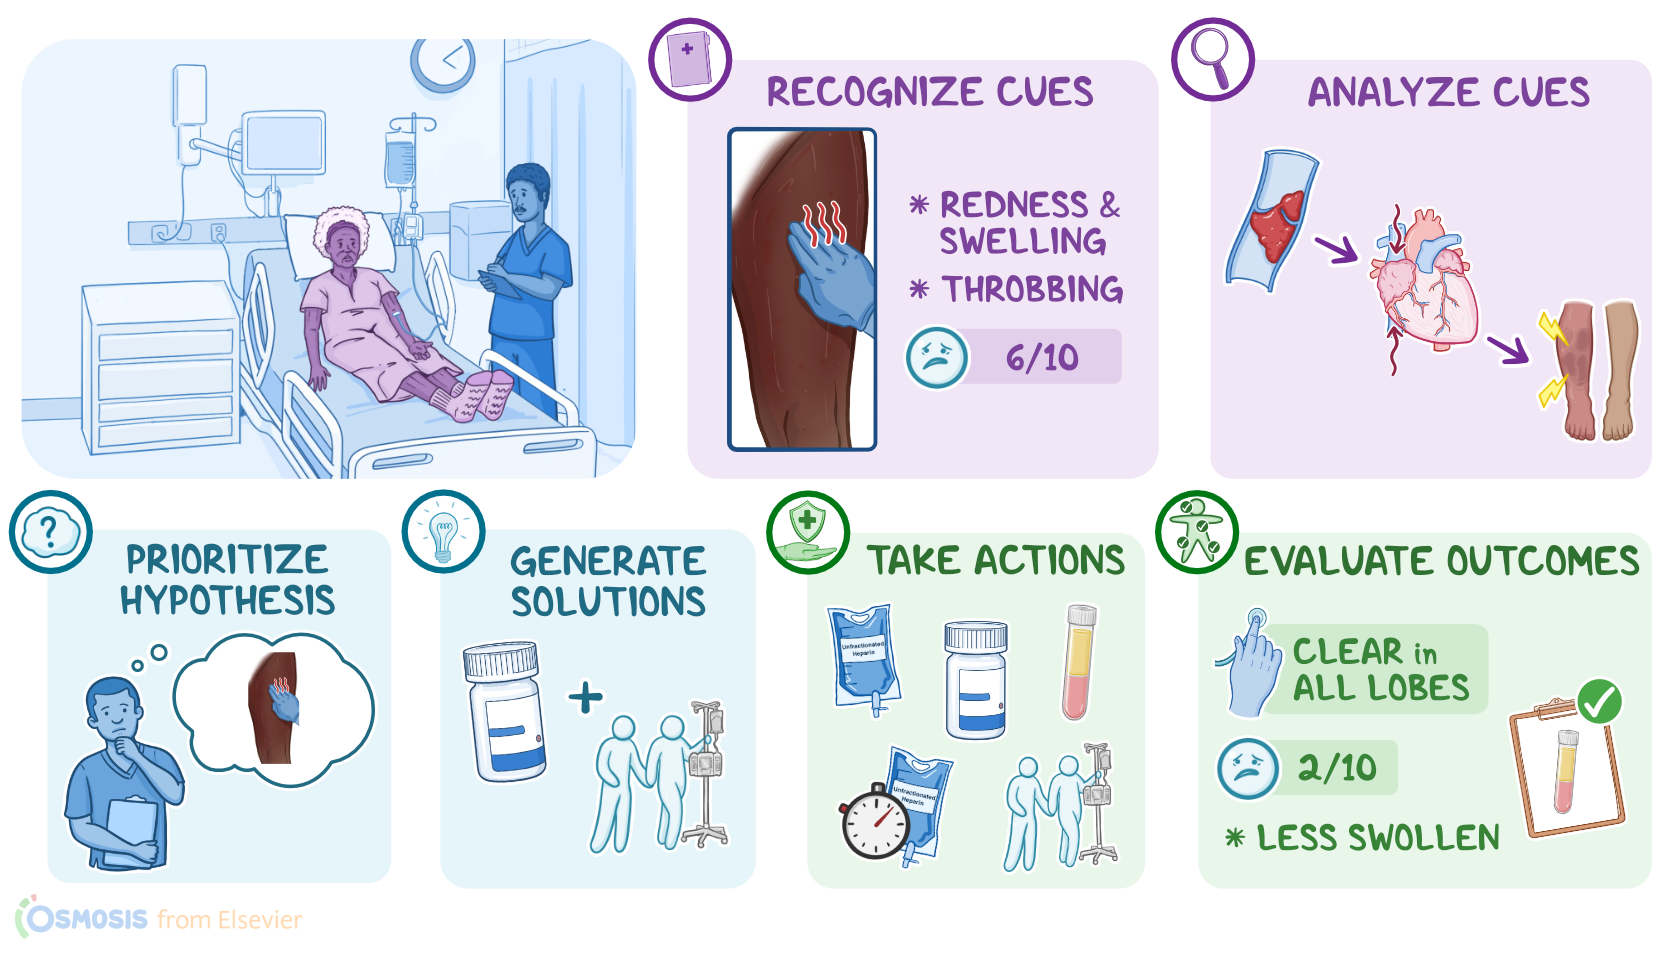
I spent nine years teaching Med-Surg rotations. The majority of my students failed to catch early DVT signs during case studies until they ran into this particular HESI exercise. They had the textbook knowledge. They just could not apply it under pressure. The Hesi Case Study Deep Vein Thrombosis A Clinical Simulation Blueprint For Recognizing And Managing Dvt is structured differently from standard nursing school case studies. It forces you through assessment decisions before giving you the diagnosis. Most programs skip that step. They tell students what the patient has, then ask for interventions. This one makes you figure out which symptoms matter and which ones are noise.
The Hesi Case Study Deep Vein Thrombosis A Clinical Simulation Blueprint For Recognizing And Managing Dvt
Here is how it works in practice. You get a patient profile with vital signs, subjective complaints, and lab results spread across multiple tabs. You do not get a clear diagnosis upfront. You have to decide what to assess next, what interventions to prioritize, and when to escalate. The system tracks whether your assessment choices led you toward the correct path or down a rabbit hole. I remember running this with a group of third-semester students last spring. One student kept charting a lower extremity assessment but never documented calf circumference measurements. She noted the leg looked swollen and moved on. The simulation flagged it because she missed the objective data point that would have confirmed asymmetry. She argued that she had assessed the leg. She had not. Not thoroughly enough for the case study to accept it as valid. The workaround was straightforward. I had her go back and measure both legs at the same anatomical landmark, mid-calf, and record the difference. Two centimeters or more was the cutoff in this scenario. Once she included that number, the simulation unlocked the next decision branch. It felt arbitrary at first. Then I realized that in real clinical practice, if you do not document the measurement, you have no baseline to track progression or response to treatment.
The Assessment Logic Behind It
DVT presentation is intentionally inconsistent. That is the whole point of this case study. About thirty percent of patients with confirmed DVT have no classic symptoms. Another large subset presents with vague complaints that sound like musculoskeletal strain or cellitis. The simulation builds this uncertainty into the scenario deliberately. The key assessment priorities this case study tests are: Unilateral leg swelling with pain on dorsiflexion. This is the classic Homans sign, though it is neither sensitive nor specific enough to rely on alone. The case study expects you to note it but not treat it as definitive proof.
Get the Full Details

Recent immobility or hospitalization history. The simulation tracks whether you review surgical history, prolonged travel, or cancer diagnosis. These are the real risk multipliers that separate DVT from a pulled muscle in an otherwise healthy twenty-four-year-old. Prior DVT or family history of thrombophilia. Students frequently overlook this. The case study flags it when you miss it. Warmth, redness, and tenderness along the deep vein pathway. Superficial thrombophlebitis can look identical at first glance. The simulation pushes you to differentiate based on extent of involvement and presence of systemic signs.
Intervention Sequencing
This is where most students lose points. The case study requires you to sequence interventions correctly, not just list the right ones. Anticoagulation is the treatment, but ordering it without completing the diagnostic workup first is marked as incorrect prioritization. The proper order runs like this. Assess and document the full lower extremity exam. Apply warm compresses if ordered per protocol for comfort. Avoid deep massage of the affected limb. Notify the provider. Obtain the order for diagnostic imaging, typically a Doppler ultrasound. Once the diagnosis is confirmed, administer anticoagulants as prescribed. Monitor aPTT or INR depending on which agent is used. Monitor for bleeding complications throughout. I caught a pattern with my students. They wanted to jump straight to heparin because they recognized the diagnosis from textbooks. The case study punished that instinct. You do not start therapeutic anticoagulation on a patient who has not had a platelet count checked or a bleeding time evaluated. HIT, or heparin-induced thrombocytopenia, is the reason. Starting heparin without knowing the baseline platelet count is a genuine clinical error, and this simulation makes you feel that consequence.
When a student ordered heparin before the platelet count in this case study, the scenario introduced a complication. Platelets dropped sharply. The student then had to manage an adverse reaction they could not have prevented if they had followed the correct sequence. It was an expensive lesson in terms of simulation time, but it stuck. I have not seen that mistake repeated in clinical settings since.

Common Pitfalls to Avoid
The case study includes distractor symptoms. Patients often report anxiety, shortness of breath from pain, or fatigue. These are real symptoms but they are not the primary focus. Students who chase every symptom simultaneously end up overwhelmed and miss the core assessment actions. Another pitfall is over-relying on Doppler results as instantly available. In many hospital scenarios depicted by this case study, the ultrasound technician is not in the building yet. You may need to position the patient, explain the procedure, and wait. The simulation tracks whether you prepared the patient appropriately during that waiting period. Documentation of patient education scores here. A less obvious issue involves discharge planning. Students routinely complete the acute management portion and then stall on the teaching component. The case study requires you to address activity restrictions, medication adherence, signs of bleeding to report, and follow-up timing. Skipping this section lowers your overall score even if your clinical decisions were correct. It is a reminder that DVT management extends well beyond the initial treatment window.
Limitations and Where It Falls Short
This case study is not a complete preparation tool. It covers one common DVT scenario, typically involving a post-surgical patient. It does not address pelvic DVT, upper extremity DVT from central lines, or DVT in pregnant patients. If your program only uses this simulation, your students will be unprepared for those variants. The scoring also tends to favor textbook-ideal responses over pragmatic clinical judgment. A real nurse might recognize a high-risk patient and communicate urgently with the provider before completing every single documentation field. The simulation sometimes treats incomplete documentation the same way it treats incorrect clinical decisions. That is a valid design choice for an academic setting, but it can feel disconnected from how fast-moving hospital floors actually operate. For a more comprehensive approach, I pair this case study with additional resources covering pulmonary embolism recognition, anticoagulant reversal protocols, and extended discharge teaching frameworks. No single simulation covers the full scope of DVT management adequately.
Practical Takeaway
The value of this case study is not in memorizing the correct answer sequence. It is in experiencing the frustration of incomplete assessment and watching how that directly causes downstream errors. The simulation does not coddle you. It lets you make the wrong call, shows you the consequence, and then makes you live with the corrected outcome. That is harder to forget than any lecture slide. If you are working through it, slow down on the assessment section. Measure both legs. Check the history thoroughly. Wait for the labs before escalating treatment. The rest follows from there.