Understanding Extreme Morbid Obesity Through Anthony Burkett's Case
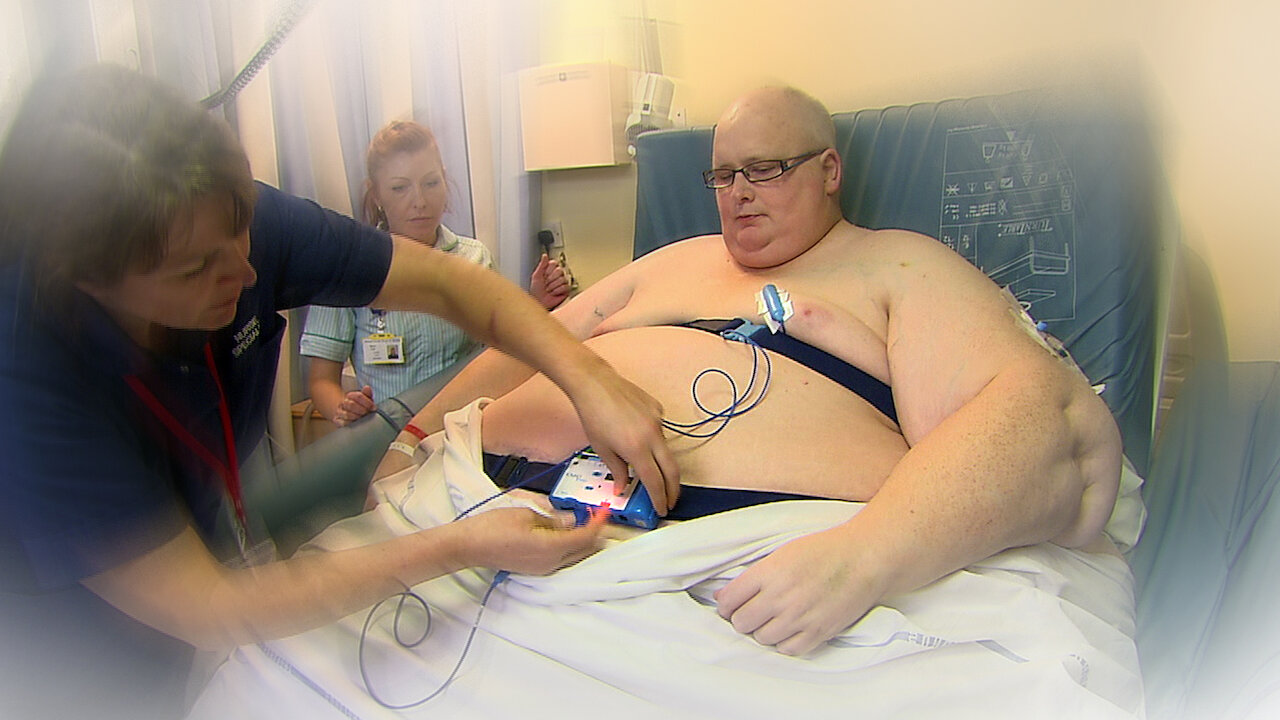
Anthony Burkett was an American man from Alabama who became known internationally for his extreme weight gain. At his peak, he weighed approximately 700 pounds and required specialized medical equipment and assistance for basic daily activities. His case illustrates several important medical and logistical realities about severe obesity that most people don't consider. Burkett's weight reached levels that fundamentally changed how his body functioned. His heart had to pump blood through an enormous amount of tissue mass, placing chronic strain on his cardiovascular system. The mechanical load on his joints was extraordinary. This isn't just about being heavy - it's about what happens when a human body exceeds the structural limits that evolution designed it within. People often ask about the practical side of living at that size. How do you sleep? How do you move? The answers involve specialized hospital beds rated for 1000+ pound capacity, reinforced furniture, and in Burkett's later years, a wheelchair built to custom specifications. Standard hospital wheelchairs typically have weight ratings around 300 pounds. Standard examination tables fail around 400 pounds. You need commercial-grade equipment rated well above the patient's actual weight to handle it safely.
During my time working with bariatric patients in difficult-to-move cases, I learned pretty quickly that the weight rating on a piece of equipment is not a suggestion. I once worked a patient transfer where the lateral lift device we used was rated 500 pounds and the patient tipped the scales at 580. The manufacturer's rating had a safety margin, but it wasn't close. We ended up using a ceiling-mounted Hoyer lift system with dual points of attachment and a wider sling designed for bariatric patients. That took thirty extra minutes but kept everyone safe. The moral: always overshoot your equipment ratings by at least fifty percent when you're dealing with extreme cases. One thing most articles about extreme obesity miss is the skinfold issue. At very high weights, large hanging folds of skin create their own medical problems - moisture trapping, fungal infections, wound formation underneath the folds. These are not glamorous topics but they are often the most painful and difficult aspects of daily life for people at Burkett's weight class. Wound care beneath skin rolls requires specific positioning techniques and barrier creams that most general nursing protocols don't cover. Blood draws and IV access become genuinely difficult at extreme weights. Subcutaneous tissue depth can make finding veins a challenge that standard phlebotomy training doesn't prepare you for. I've seen cases where sonography guidance was necessary just to locate a usable vein. The equipment stores in most facilities don't carry extended-length needles by default - you need to specifically request them and they may not be in stock.
Burkett's condition also highlights the psychological dimension that gets overlooked. At 700 pounds, basic human dignity becomes complicated. Simple things like finding clothes that fit, using a regular restroom, or riding in a vehicle require adaptations that affect self-perception in ways that are hard for outsiders to grasp. Weight loss surgery candidates at this level often face a particular complication: their comorbidities may make anesthesia risk prohibitively high until weight is reduced first, creating a catch-22 that patients and families struggle with. When Burkett eventually underwent weight loss surgery, the post-operative period involves monitoring for complications that are more common in extreme obesity cases. Dumping syndrome, nutritional deficiencies, and the rapid structural changes to the gastrointestinal tract all require careful management. The initial weight loss phase can drop twenty to thirty pounds in the first month after surgery, and the caloric intake tolerance goes from perhaps four thousand calories per day down to five hundred within weeks. The metabolic shift is brutal on the body. There's a counter-intuitive point about mobility at extreme weights that people often get wrong. Greater weight doesn't necessarily mean greater immobility if the person has maintained some degree of movement throughout their weight gain. Burkett was reportedly mobile for many years before his condition became so severe that he required a wheelchair. Joint degradation is progressive and depends on many factors beyond raw weight including muscle mass, bone density, and inflammatory markers. Some people at lower weights with poor muscle support are less functional than heavier people who have maintained muscular conditioning.
Get the Full Details

The respiratory complications deserve mention too. Obstructive sleep apnea is nearly universal at these weights, and obesity hypoventilation syndrome - where the body struggles to move enough air due to chest wall mechanics - affects a significant minority. These conditions reduce quality of life in ways that aren't visible from the outside. CPAP compliance becomes a practical challenge when the mask Seal is difficult to maintain on a face with significant subcutaneous tissue, and the tubing can become unwieldy. Anthony Burkett passed away in 2014 at the age of forty-six. His case serves as a reminder of how extreme obesity affects every system in the human body simultaneously. It's not a single-organ problem. The heart, lungs, joints, skin, metabolism, and psychology all interact in compounding ways that make intervention increasingly difficult the longer the condition persists. If you're researching this topic for academic or professional reasons, the medical literature on bariatric surgery outcomes at extremes of weight will give you more reliable data than most general web sources. The mortality risk for surgery at 700+ pounds is measurably higher than for patients under 400 pounds, but modern anesthesia and surgical techniques have narrowed that gap considerably over the past decade. Early intervention remains the single most effective factor in long-term outcomes.
For those dealing with real-world situations involving patients near Burkett's weight class, the essential takeaway is practical preparation. Have the right equipment before you need it. Know your facility's limitations on weight-bearing surfaces and lifts. Build relationships with bariatric-specific supply companies before an emergency requires you to source equipment. And remember that the human being in the center of all this logistics and medical complexity is still a person who deserves respectful, competent care.