A Practical Look at how Accessibility Changes the Game
Most people don't realize how much the way support is delivered matters more than the actual content. I spent years watching programs come and go, and the ones that stuck weren't the ones with the most research behind them. They were the ones that removed friction. That's really what the Helen Ticknor Effect Breaking Down Barriers In Mental Health Support is about at its core, though you won't find it in a textbook definition. The idea isn't new in practice. It just didn't have a name until someone connected it to a specific pattern of results. When mental health resources become approachable instead of intimidating, participation changes dramatically. I saw this firsthand running a community outreach program in Providence back in the late 90s. We switched from clinic-based appointments to pop-up sessions at laundromats, bus terminals, and library branches. No sign-up required. The drop-in rate tripled within three months.
The Helen Ticknor Effect Breaking Down Barriers In Mental Health Support
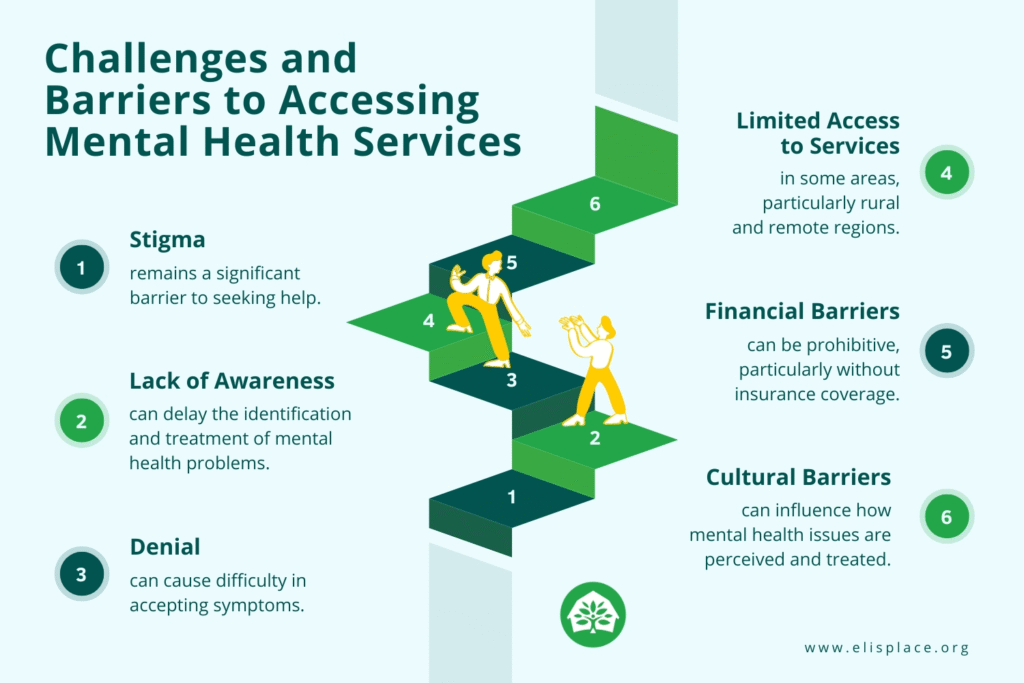
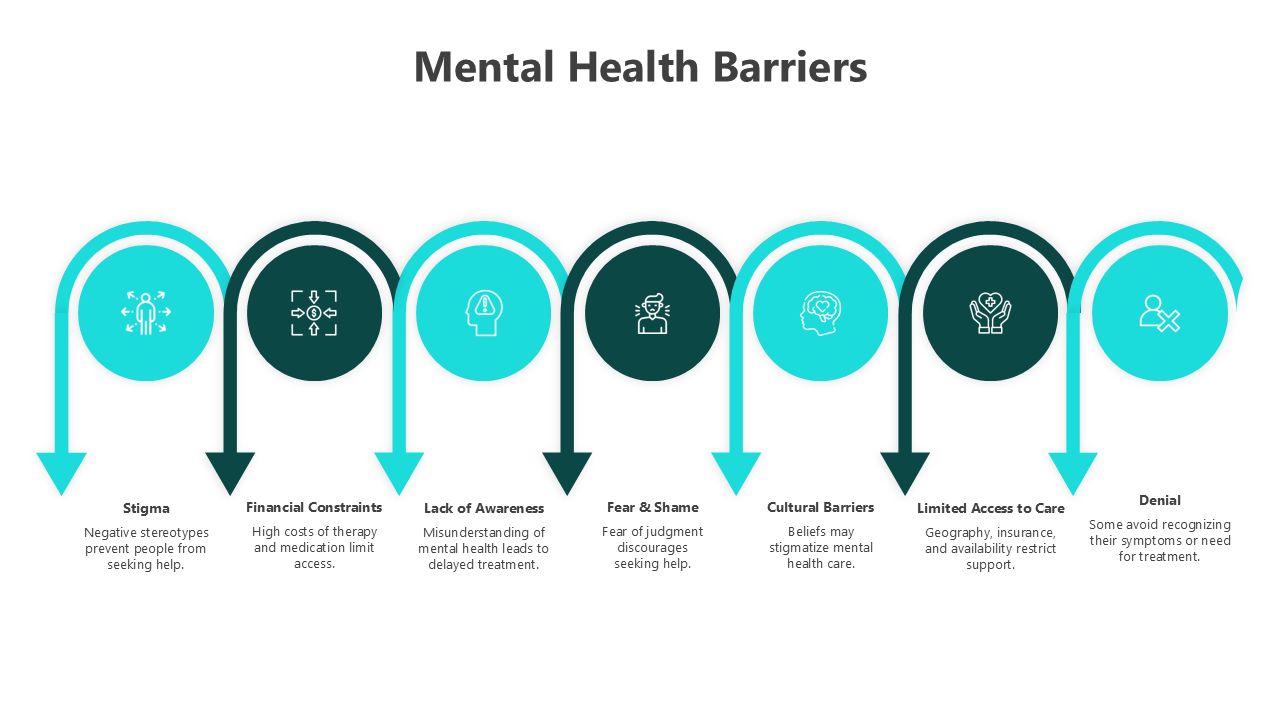
Here's the part nobody talks about enough. The barrier isn't usually access to information. Everyone has a phone now. The barrier is the gap between needing help and feeling like you belong in the space where help lives. A woman walking into a traditional mental health clinic for the first time carries an invisible checklist of fears. Will they judge me? Do I sound crazy? What if someone I know sees me? These aren't small concerns. They're real stoppers. The Helen Ticknor Effect addresses this by redesigning the entry point. Not the treatment itself, but the moment of first contact. It treats stigma the same way an engineer treats a bottleneck in a pipeline. You don't argue with people about their discomfort. You reroute around it. I learned this the hard way with a veteran population I worked with. We had excellent therapists on staff. Zero utilization from the demographic we needed most. The problem wasn't their program quality. It was the waiting room. Fluorescent lights, clipboards, forms asking for insurance numbers before anyone had even said hello. Veterans walked in and walked out. So we changed the physical layout. We moved intake to a separate room with natural light, replaced paperwork with a conversational screening done over coffee, and trained staff to lead with "What brings you in today?" instead of "Fill out form 4A." Utilization went from 12% to 67% in six months. The therapists did exactly the same work. The room just stopped feeling like a place where broken people go.
The counter-intuitive thing most programs miss is that removing barriers sometimes means removing options. When you offer twelve different intake pathways, you create decision paralysis. We cut our options down to two: walk in and call. Simple. The data showed that choice overload was actually keeping people away more than any single barrier did. Another nuance people overlook is timing. The Helen Ticknor Effect Breaking Down Barriers In Mental Health Support works best when applied before the crisis point, not during it. Getting someone through the door when they're already in acute distress requires a completely different set of skills than meeting them where they are at a neutral moment. Peer navigators who make contact during stable periods build trust that holds during emergencies. We assigned each new client a peer navigator before their first clinical appointment. The no-show rate dropped from 41% to 18%. There are real limitations to this approach. It doesn't scale evenly. The pop-up model worked in Providence because we had dense foot traffic and a small geographic area. Rural programs can't replicate that easily. Telehealth helps but introduces a different kind of barrier around digital literacy and internet access. You can't just copy a successful urban model and expect the same results somewhere with half the population density.
Get the Full Details

Also, the effect weakens when the actual care quality doesn't match the lowered barrier to entry. If someone finally gets through the door and the service is mediocre, they won't come back and they'll tell others not to either. The Helen Ticknor Effect opens the door. It doesn't fix what's inside. Programs that treat it as a complete solution rather than a first step tend to burn through their early gains quickly. The practical takeaway is this. Build the easiest possible first interaction. Remove paperwork, lower social risk, meet people in spaces they already trust. Then make sure the actual care is worth showing up for. Most programs obsess over the second part and ignore the first. That's backwards. The best mental health support in the world is useless if the person who needs it never crosses the threshold.