Listening for the Extrasystole: S3 and S4 Are Not the Same Thing
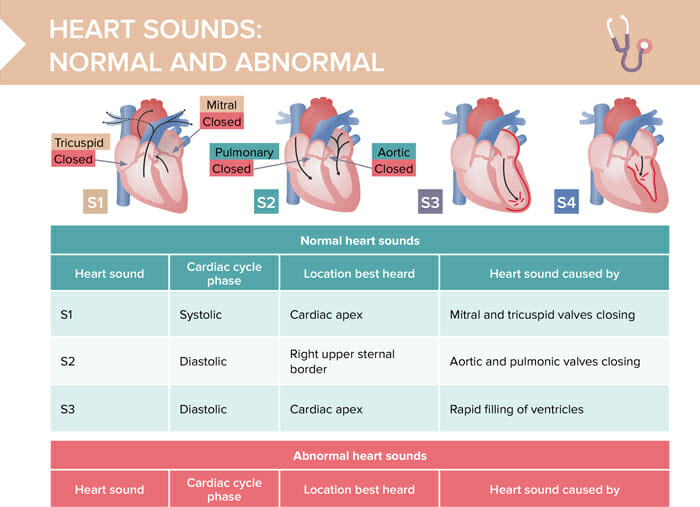
I spent years on call where distinguishing an S3 from an S4 meant the difference between starting a diuretic and missing a hypertrophic cardiomyopathy. They sound similar at first, both being low-frequency extra heart sounds in diastole, but they sit on opposite ends of the filling curve and carry completely different prognostic weight. Getting them right matters more than the textbooks usually suggest. An S3 occurs in early diastole during the rapid filling phase, right after S2. It is produced when blood hits the ventricular wall and causes it to recoil. Think of it as the sound of a volume-overloaded chamber being filled too quickly. An S4 happens in late diastole, just before S1, and it requires atrial contraction against a stiff ventricle. The atrium is essentially kicking against resistance, and that kick creates the sound. The practical difference shows up immediately in the rhythm. An S3 is synchronous with the passive filling, so it moves with the heart rate in a predictable way. An S4 disappears when the patient goes into atrial fibrillation because there is no coordinated atrial contraction left to drive it. I had a patient in the ICU who had a loud S4 on sinus rhythm, and when he converted to afib after cardioversion, the sound just vanished. That was the moment I truly understood what an S4 represents mechanically.
Here is what most people miss about location and transmission. Both sounds are best heard with the bell of the stethoscope at the apex, left lateral decubitus position, but an S3 from volume overload will often transmit to the lower sternal border or even the epigastric region, while an S4 stays more localized. This is not a hard rule, but it saved me once when a busy resident told me a patient had an S3 and I heard something that sounded more like an S4 by the aortic area. We ended up finding severe aortic stenosis with concentric hypertrophy instead of heart failure. Timing relative to surrounding sounds is your primary tool. An S3 is separated from S2 by a longer interval and from S1 by a shorter one. The mnemonic is V3 = Ventricular filling, early diastole. An S4 sits just before S1, almost touching it. The atrium contracts, the sound happens, then the mitral valve closes. If you count out loud three-one, two-three, the extra beat lands on the three for an S3 and on the one for an S4. It feels counter-intuitive at first because an S3 sounds closer to S1, but the timing is measured backward from S2 forward. Respiration also shifts things. An S3 from right ventricular volume overload, like in tricuspid regurgitation or a large shunt, gets louder on expiration because increased intrathoracic pressure pushes more blood into the right heart. An S4 from left ventricular hypertrophy due to hypertension does not change much with breathing. I used to have residents sit on the edge of the bed and breathe with the patient while we listened, which felt theatrical, but it was genuinely useful for lateralizing the origin of the sound.
There is a trap with obese patients or those with COPD. Both S3 and S4 become difficult to hear because sound attenuation is severe, and sometimes what you think is an S4 is actually a loud S1 with a prominent opening snap or a tumor plop from a myxoma. I spent an afternoon chasing an S4 in a morbidly obese patient, and when we finally got an echocardiogram, there was no diastolic dysfunction at all. The sound was a pericardial knock from constrictive pericarditis, which mimics an S4 in timing but has a fundamentally different mechanism and management pathway. Age is another factor that gets oversimplified. An S3 in a child or young adult under thirty can be normal, a physiological finding that requires no workup. An S3 in someone over fifty is pathological until proven otherwise. An S4 is almost always abnormal in adults and usually signals significant diastolic dysfunction, whether from hypertension, aortic stenosis, hypertrophic cardiomyopathy, or ischemic heart disease. The presence of an S4 alone does not tell you the cause, but it does tell you the ventricle is stiff, and that should start a search. Echocardiography remains the definitive way to confirm what you hear, but the physical exam still predicts outcomes independently. An S4 in a patient with heart failure with preserved ejection fraction correlates with higher filling pressures and worse exercise tolerance. An S3 in acute decompensated heart failure predicts higher mortality and correlates with BNP levels. I once discharged a patient with a newly discovered S4 and thought it was benign hypertensive changes, and he came back three weeks later in flash pulmonary edema. The S4 had been there the first time, but I did not act on it aggressively enough. That stays with you.
Get the Full Details

For anyone learning to distinguish these sounds, the best approach is hearing both in the same patient when possible. A patient with hypertensive heart disease and early systolic dysfunction will sometimes have both an S4 and an S3, creating a summation gallop. When the heart rate slows, the two sounds separate clearly. When it speeds up, they merge into a single loud diastolic sound that is easy to misidentify. I always ask the patient to hold their breath and listen at multiple rates, because the variable timing is itself diagnostic. Recording with phonocardiography helps, but even a standard digital stethoscope with a graph display makes the distinction obvious. The S3 appears as a low-amplitude oscillation roughly 0.12 to 0.18 seconds after S2. The S4 appears 0.08 to 0.12 seconds before S1. The intervals are short, and the amplitudes are below 20 Hz, which is why the bell and light contact matter so much. Pressing too hard with the bell eliminates the very frequencies you are trying to hear. There is no single test that replaces careful listening, and no rule that covers every case. Constrictive pericarditis, restrictive cardiomyopathy, and dilated cardiomyopathy can all produce sounds that resemble S4s, and sometimes the echo and MRI are the only way to sort them out. But the initial categorization into S3 versus S4 guides everything from whether you order a BNP to how urgently you consult cardiology, and that categorization starts entirely with your ears and your patience.