Myocardial Infarction Coding in ICD-10-CM
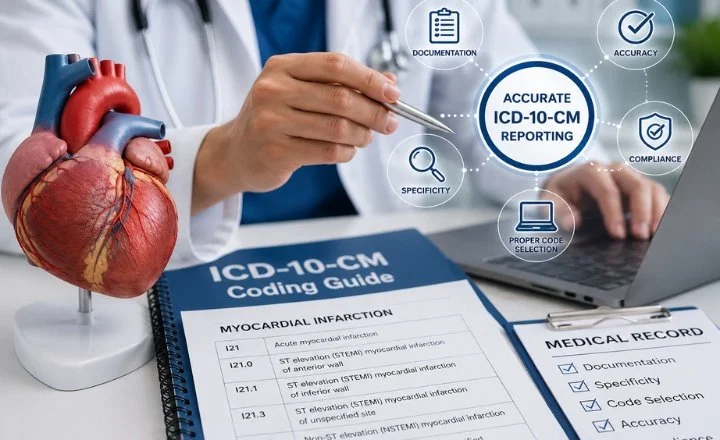
Coding MI sounds straightforward until you open the tabular and realize there are at least twenty codes that could technically apply to the same patient. I have been doing this long enough to know that the first three seconds of your search almost never land you on the right answer. You have to read the entire code block. The difference between a correct assignment and a denial is usually a single character in the code or a detail that was buried three pages into the encounter note. Start with I21 for acute myocardial infarction. That is the anchor. Everything else branches from there. The critical first decision is whether the documentation supports ST elevation or not. If it does, you are looking at I21.0 through I21.3. If it does not, you are in I21.4 territory. The documentation has to explicitly mention STEMI or NSTEMI, or the clinical indicators like ST elevation on ECG have to be recorded in the medical record. Without that specificity, coders fall back to I21.9, which is an unfinalized, non-specific MI diagnosis. Insurance companies reject I21.9 more often than almost any other acute MI code because payers expect the clinician to have distinguished the type. I encountered a case last November where a physician documented acute inferior wall myocardial infarction with ST elevation but the inpatient claim was submitted with I21.1. The coder assumed inferior wall mapped directly to I21.1, but the actual record showed ST elevation changes in leads II, III, and aVF with reciprocal depression. That combination actually points to I21.0, which covers acute transmural infarction of anterior wall, or in this case, the documentation needed to be clarified because the inferior STEMI was being miscoded under a different subcategory. I flagged the discrepancy, sent a query to the physician, and we got the documentation corrected to support I21.0 with the appropriate laterality extension. The revised code went through without a denial. That query process added four days to the turnaround, but it prevented an automatic rejection that would have required a full resubmission cycle taking another two to three weeks.
Subsequent MI codes under I22 exist only for patients who were treated for one type of MI and then present again with a different type within the eight-week window. I22.0 is for subsequent ST elevation MI following a prior non-ST elevation MI, and I22.1 covers the reverse scenario. Most coders skip this entire section because they assume it never applies. It applies frequently. The rule is simple: if a patient is readmitted within eight weeks for a new acute MI event that is a different type than the original, you code the new event with I22. You do not recode the original MI. The eight-week window starts from the date of the initial MI admission, not the discharge date. Counting from discharge is a common error that inflates the window and creates double billing for the same episode of care. Old MI is I25.2. This is often confused with chronic coronary artery disease or post-infarction angina. I25.2 is strictly for evidence of old transmural infarction documented by pathological Q waves on ECG or imaging. If the physician writes chronic MI, old MI, or healed MI with no mention of Q waves, I25.2 may still be appropriate depending on the clinical context, but you need to confirm the Q wave documentation exists in the record. Without it, you should default to I25.9 or I25.10 depending on the presence of atherosclerotic heart disease. A lot of coders auto-assign I25.2 whenever they see the word old because they think it is a safe fallback. It is not. It is a specific diagnosis that requires specific documentation. Sequencing matters enormously in inpatient settings. The acute MI is always listed as the primary diagnosis unless there is a complicating condition like cardiogenic shock or acute heart failure that was the main reason for the stay. Cardiogenic shock gets coded as I26.9 with the MI as secondary. If the shock resolves during the stay, you still code it as a complication. I have seen coders drop the shock code once the patient stabilizes. That is incorrect. Complications are coded regardless of resolution status. They affect the DRG and the severity of illness score.
Another thing nobody warns you about: the external cause codes. For MI, you generally do not assign an external cause code because the event is not injury-related in the trauma sense. But if the MI was caused by a drug adverse effect, such as a chemotherapy agent or a prescribed medication reaction, you code the adverse effect first and the MI as secondary. This is rare but it happens, and missing it creates incomplete data that will show up as a query from a payer who is auditing medication-related hospitalizations. The most time-consuming part of MI coding is actually the documentation review. Physicians frequently write "MI, rule out NSTEMI" and then the final diagnosis is NSTEMI, but the coder grabs the rule-out. That is not acceptable. Final diagnosis only. Conversely, physicians sometimes document MI and leave the type blank. In that case, you query for specification. If you cannot get a response within a reasonable timeframe, you code to the highest specificity available based on what is in the record. You do not guess. You do not expand beyond the documented evidence. You code what exists and you flag the gap. A final practical note: I21 and I22 codes require a seven-character extension for certain circumstances, but most MI codes in the I21 and I22 blocks are six characters and do not need further extension. Do not add a seventh character where one does not belong. It will generate an immediate edit failure in most clearinghouses. Check your code set before submitting. A six-character code submitted with a fabricated seventh character is one of the easiest denials to catch, and it reflects poorly on the coder regardless of the actual medical accuracy of the assignment.
Get the Full Details