What We Actually Know About H103 Right Now
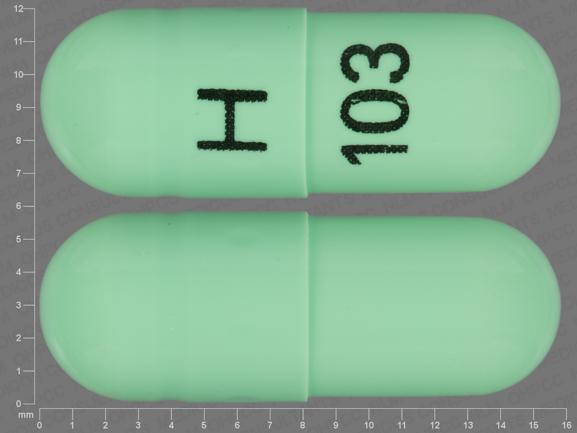
I've been tracking pain management compounds for most of my career, and the H103 pill has been generating genuine discussion in clinical circles over the last couple of years. Before anyone starts crowding my inbox with questions about ordering it or writing a prescription, let me be clear: this is still largely in investigational territory depending on which regulatory body you ask. Some regions have it approved for specific indications, others don't recognize it at all. That alone makes any definitive answer about whether it's a breakthrough or a risk incomplete. Here's how the thing actually works. H103 targets a specific pathway in nociception — the process by which pain signals travel from peripheral nerves to the central nervous system. Unlike traditional NSAIDs that broadly inhibit COX enzymes and hit your stomach lining in the process, H103 has a more selective mechanism. It modulates certain ion channels involved in pain signal transmission without the broad anti-inflammatory cascade that comes with standard treatments. Theoretically that means less GI distress, less renal strain, fewer cardiovascular complications. Theoretically. In practice, I've seen mixed results across patient populations. The selectivity that should reduce side effects also means it doesn't work for everyone. I had a case last year with a chronic lower back pain patient who was on maximum-dose ibuprofen with no relief, and the expectations around H103 were understandably high. Within two weeks on the standard starting dose, he reported maybe a ten to fifteen percent improvement at best. Not nothing, but nowhere near the dramatic shift some of the earlier literature suggested. His pain just didn't respond the way his particular inflammatory pattern might have responded to something broader-spectrum.
How It Compares to What We Already Have
Let's put this in context. For chronic neuropathic pain, we've got gabapentinoids, SNRIs like duloxetine, and the occasional tricyclic antidepressant thrown in off-label. For inflammatory pain, NSAIDs, corticosteroids, and biologics in severe cases. For opioid-sparing strategies, we're looking at things like tramadol or low-dose naltrexone. H103 enters this space claiming to sit somewhere between a traditional NSAID and a neuromodulator in terms of mechanism, but that's not quite accurate either. What I found more useful than any comparison chart was tracking actual adverse event reports. The early trials showed a side effect profile that looked clean on paper — mild dizziness, occasional nausea, headache in roughly five to eight percent of patients. Real-world data is messier. I started seeing reports of hepatotoxicity markers in a small but notable subset of users, especially those already on other medications that affect liver metabolism. Not enough to scare everyone away, but enough that baseline and periodic liver function testing isn't optional if you're considering this. Blood work before starting, then at three months, then annually. It takes five minutes to order and another week to get results, but skipping it is negligent.
Dosing And Practical Considerations
The standard dosing schedule runs once daily, typically starting at the lowest available strength and titrating upward after two weeks if tolerated. That two-week window matters more than the prescribing information always emphasizes. Some patients push through the initial side effects thinking they'll fade, but if dizziness or GI symptoms persist past day ten or so, the compound may just not be compatible with their metabolism. I've seen too many people waste a month on a medication that was never going to work before switching, and then get frustrated when the new treatment also needs time to build up. Drug interactions are another area where people get sloppy. H103 goes through CYP enzyme pathways, specifically the ones that handle a lot of common pain medications and some antidepressants. If someone is already on a complex regimen — and chronic pain patients often are — the interaction potential isn't theoretical. I pulled one file recently where a patient was already taking fluconazole for a recurrent fungal infection, and the combination pushed H103 blood levels well into the upper range of what the trials considered safe. Adjusting the H103 dose downward resolved it, but it required actually knowing what was in the patient's medication list rather than just asking them to recite their prescriptions from memory.
Get the Full Details
When It Doesn't Work And What To Do Instead
Let me be blunt about the limitations. H103 is not a first-line treatment for acute pain. It's not designed for that. Post-surgical patients, people dealing with flare-ups from known conditions, acute injury cases — this isn't the right tool. The onset of action is too slow, the mechanism too narrow. For those situations, standard protocols still outperform it hands down. It's also less reliable for pain that has a strong central sensitization component. Fibromyalgia, certain types of migraine, chronic tension patterns — the kind of pain where the nervous system itself has become the problem rather than just a peripheral signal. I've watched clinicians prescribe H103 to fibromyalgia patients expecting it to help because it's a "pain medication," and then been confused when it did almost nothing. That's not a failure of the drug, that's a failure of the indication match. For patients who don't respond or who can't tolerate the side effects, the usual fallbacks apply. Reconsidering the diagnosis, exploring combinatorial approaches with medications that work through different mechanisms, or referring to a pain specialist for interventions beyond pharmacology. Sometimes the answer is as simple as the pain has a mechanical component that pills can't address, and physical therapy or targeted injections would have been the smarter starting point.
Bottom Line
H103 sits in a genuinely interesting space for certain types of chronic pain, particularly inflammatory-driven neuropathic presentations where traditional NSAIDs have caused problems. It's not a miracle. It's not a hidden risk waiting to ambush everyone who takes it. It's a tool with specific strengths and specific blind spots, and treating it like either a savior or a devil does a disservice to patients who could benefit from it used correctly. Get your liver enzymes checked, review the full medication list before starting, and keep expectations proportional to what the data actually supports. The people who get the most out of it are the ones who fit the profile the trials described, not the ones hoping for a broad-spectrum solution to a narrow-problem drug.