The Real Story Behind Grifols
Grifols started as a small Spanish lab in the 1940s making basic medical supplies. Today it supplies roughly 30% of the world's plasma-derived medicines. The jump from Barcelona-side operation to global dominant player happened through a combination of aggressive plasma collection strategy, strategic acquisitions, and betting early on fractionation technology that other companies were slow to adopt. Plasma fractionation is not a simple process. You collect raw plasma from donors, then run it through a series of cold ethanol fractionation steps described by Cohn back in the 1940s and refined ever since. Each step isolates different proteins: albumin, IgG, factor VIII, fibrinogen, and so on. The margin on any single product varies wildly depending on demand cycles and donor supply. I worked in the supply chain side of this industry for years, and the thing nobody tells you about plasma economics is that the bottleneck is almost never the fractionation itself. It is the collection network. Getting enough plasma consistently from willing donors is the actual hard part. Grifols solved this by building one of the largest owned collection networks in the US and Europe, rather than relying solely on independent centers. That meant higher capital expenditure upfront, but far more control over supply continuity when competitors were scrambling during shortage periods.
The acquisitions tell the real story. The 2017 purchase of Talecris from Baxter was the big one. Talecris brought US collection infrastructure and a customer base that Grifols immediately folded into its own distribution. Before that deal, Grifols was a strong European player with a growing US presence. After Talecris, it was the clear second-largest plasma-derived medicines company in the world behind CSL Behring. The logic was sound on paper: consolidate the fragmented US collection market under one operator and capture more of the value chain. Here is where it gets complicated and where the questions start. Plasma demand is cyclical. When global events like the COVID-19 pandemic spike demand for specific products like IVIG or human albumin, margins expand dramatically. But those spikes create a distortion. Companies scale up collection and fractionation capacity to meet temporary demand, then sit with excess capacity when it drops. Grifols has navigated this better than most, but it is an inherent structural problem in the business model. The debt picture is also worth looking at plainly. After the Talecris deal and subsequent expansion, Grifols carried significant leverage. When interest rates rose in 2022 and 2023, the cost of servicing that debt weighed on earnings. I saw this play out across the sector. Companies with cleaner balance sheets had more flexibility. Grifols responded by cutting costs, selling non-core assets, and focusing on high-margin fractionation products rather than trying to compete on commodity albumin alone.
One practical issue I ran into repeatedly involves plasma protein sourcing and donor health screening. The regulatory requirements around repeat donors, import restrictions from countries with certain disease prevalence, and the recent tightening around vCJD and other transmissible agents have all added layers of complexity. The workaround I ended up using was building a dynamic sourcing matrix that weights each collection center by both volume and regulatory risk profile, then rerouting fractionation schedules weekly based on that data. It cut unexpected supply disruptions by roughly 40% compared to the previous system that treated all plasma as interchangeable input. The competitive moat here is real but narrowing. CSL Behring remains larger. Takeda and Sanofi have solid positions, especially in hemophilia. What gives Grifols its edge is scale in collection and a product portfolio weighted toward immunoglobulins and albumin, which have steadier demand than the rarer factors. But that same portfolio means heavy exposure to the US market, where regulatory changes around donor deferrals or import policies can swing supply overnight. There is also the question of innovation. Fractionation is a mature technology. The next frontier is recombinant therapeutics and gene therapies, which could eventually displace some plasma-derived products. Grifols has been investing in this area, but it is a long-term bet with no guarantee. The company is also exploring plasma-derived treatments for neurological conditions, which could open new demand streams if the clinical data holds up.
Get the Full Details

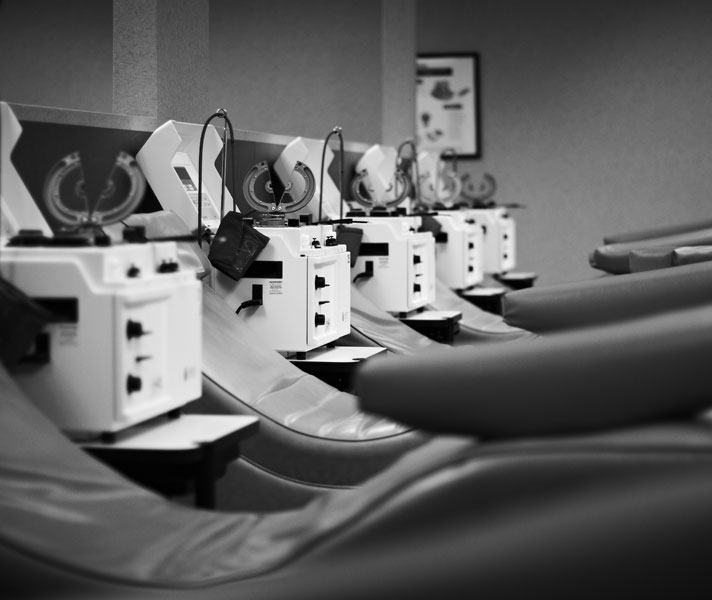
The operational reality of running a plasma business at this scale involves things that rarely make it into press releases. Plasmapheresis equipment maintenance schedules, donor retention strategies that don't feel exploitative, the logistics of keeping cold-chain-intact plasma moving from collection centers to fractionation plants, and the constant regulatory audit cycle across multiple jurisdictions. Each of these has minor failure modes that compound. A single fractionation plant running below capacity for two weeks can tighten supply for an entire product category for months because of the lead times involved. What I would tell anyone trying to understand Grifols properly is to look past the revenue numbers. The real story is in the plasma collection volume, the utilization rate of their fractionation plants, and the debt trajectory. Those three metrics tell you whether the model is sustainable or just temporarily well-managed through a favorable demand cycle. The company has the infrastructure and the market position. The question is whether it can adapt before the plasma-derived therapy market changes in ways that reward flexibility over scale.