Understanding the Greater Sciatic Foramen
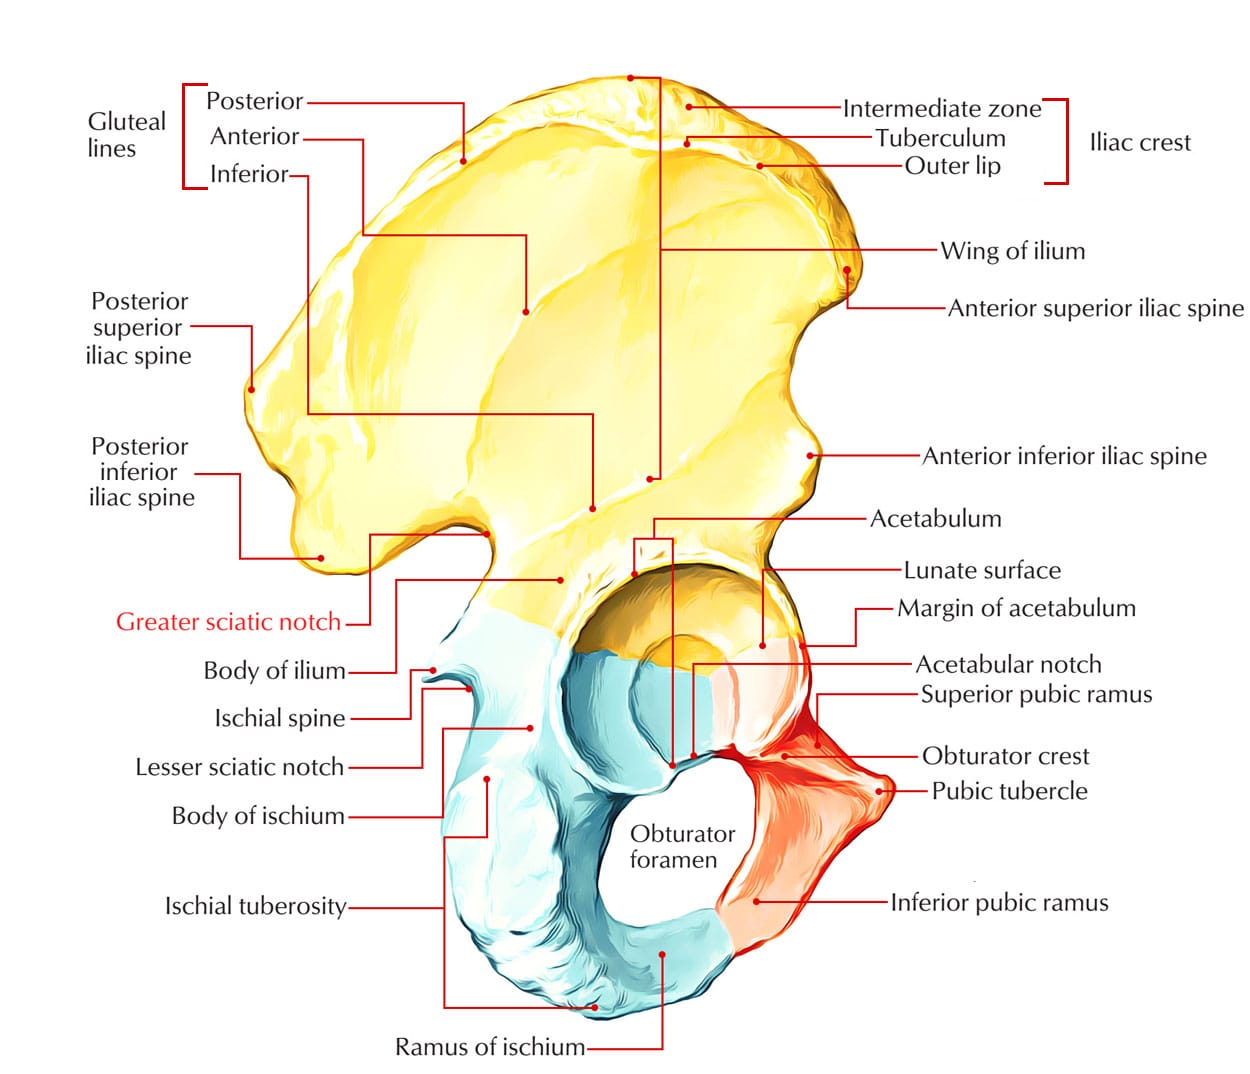
The greater sciatic foramen is an opening at the back of the pelvis. It sits between the greater sciatic notch of the ilium and the sacrotuberous and sacrospinous ligaments. When those two ligaments are in place, they effectively close off the notch and form a true foramen. Several important structures pass through it on their way from the pelvis into the gluteal region and down the lower limb. I have spent a lot of time working through cadaveric dissections of the pelvic region, and repeatedly going back to this foramen because it is where things go wrong in surgical approaches. If you are doing a posterior approach to the hip or working around the piriformis, this is the landmark you keep returning to. Miss it, and you end up chasing nerves that should be visible. The key structures are the piriformis muscle, which passes through and effectively splits the foramen into upper and lower compartments. Above the piriformis you find the superior gluteal nerve and vessels. Below it you find the sciatic nerve, the inferior gluteal nerve and vessels, the posterior femoral cutaneous nerve, and the nerve to piriformis. The pudendal nerve and internal pudendal vessels also pass through the lower part, but they immediately loop around the sacrospinous ligament and re-enter the pelvis through the lesser sciatic foramen.
Common pitfall: people memorize the list but do not internalize the spatial relationships. The sciatic nerve is the most consistent landmark. In the majority of people it exits below the piriformis, lateral to the lesser sciatic foramen. In roughly 15 percent of cases the nerve pierces the piriformis or splits around it. I had a case where a resident was preparing a posterior surgical exposure and kept getting distracted by a variant nerve course that made the usual dissection plane disappear. The workaround was straightforward: identify the sciatic nerve first by tracing it proximally from its typical position, then trace it back to the foramen rather than hunting for the piriformis first. That changed the entire sequence. One detail that is easy to miss in textbooks is how the sacrotuberous ligament interacts with the foramen. The ligament actually forms the inferior boundary. When you palpate the ischial spine clinically, you are close to where the sciatic nerve passes. That is why deep gluteal pain sometimes gets misdiagnosed as sciatica. The nerve can be compressed between the piriformis and the ischial spine, or against the ligament itself. I saw a patient who kept being treated for lumbar radiculopathy when the real issue was entrapment at this level. The workaround involved a targeted injection around the piriformis and sciatic nerve rather than another MRI of the lumbar spine. There is another anatomical subtlety. The relationship of the pudendal nerve to the sacrospinous ligament matters if you are placing sutures near the ischial spine. A suture placed too aggressively here can injure the pudendal nerve. I learned this the hard way during a pelvic floor procedure where a needle went slightly deeper than intended and caused immediate perineal numbness. The patient recovered over several weeks, but it was a clear example of why the bony landmarks alone are not enough. You have to think in three dimensions.
What passes through the foramen and why it matters
The superior gluteal nerve exits above the piriformis. It innervates the gluteus medius, gluteus minimus, and tensor fasciae latae. Damage to this nerve results in a Trendelenburg gait. The inferior gluteal nerve exits below the piriformis and innervates the gluteus maximus. Loss of this nerve makes stair climbing and rising from a seated position difficult. The sciatic nerve is the largest nerve in the body. It usually exits below the piriformis and then divides into the tibial and common fibular components. The common fibular division is more vulnerable because it has fewer connective tissue protections. I have seen injuries to this division after hip surgery, often from retractors placed too far posteriorly. The posterior femoral cutaneous nerve provides sensation to the posterior thigh and perineum. It runs with the sciatic nerve but is smaller and easier to miss. In dissection, it can look like a small branch until you trace it to its cutaneous territory. The nerve to the obturator internus and the nerve to the quadratus femoris also pass through the lower compartment. These are small but important for proprioception and muscle function.
Get the Full Details

Clinical relevance and boundaries
The boundaries of the greater sciatic foramen are the greater sciatic notch of the ilium anteriorly and superiorly, the sacrotuberous ligament inferiorly, the sacrospinous ligament medially, and the piriformis muscle dividing the space. The obturator internus and levator ani muscles line the medial wall. The ischial spine sits at the junction where the sacrospinous and sacrotuberous ligaments meet. Fractures of the acetabulum or pelvis can disrupt this region. I worked on a trauma case involving a posterior acetabular fracture where the sciatic nerve was entrapped by bone fragments at the foramen. The patient had immediate foot drop after the injury. Surgical decompression was necessary within hours to avoid permanent damage. This is one scenario where anatomical knowledge directly affects outcomes. Piriformis syndrome is another clinical scenario. It is controversial because diagnosis is clinical and there is no single definitive test. Imaging can help rule out other causes, but the actual compression often requires dynamic assessment. I have found that ultrasound-guided evaluation during movement is more useful than static MRI for this particular condition. The nerve moves with the piriformis, and static images can miss the compression.
Practical anatomy tips
If you are studying this region, do not rely only on atlases. Cadaveric dissection gives you the actual variation in real tissue. The ligaments are tough and can obscure the nerve exits until you reflect the surrounding structures. The piriformis is often the first structure you identify because it is large and consistently placed, but it is not always the most reliable landmark for the nerve courses. Palpation of the ischial spine is a useful clinical skill. You can reach it transgluteally or transrectally. This helps you locate the general area where the sciatic nerve and pudendal structures exit. In obese patients the spine is harder to palpate, and the relationship between bony landmarks and soft tissue structures becomes less reliable. Ultrasound or MRI becomes necessary in those cases. I recommend drawing the foramen yourself after each dissection or imaging review. Map the piriformis, then the nerves above and below it, then the vessels. Repeat this until the layout is automatic. The variation rate is high enough that rote memorization will fail you in practice. The 15 percent nerve variation I mentioned earlier means you cannot trust a single diagram.
When the anatomy fails you
This region does not always cooperate. Inflammation from prior surgery, scarring from trauma, or congenital variants can distort the normal relationships. I encountered a patient with extensive pelvic surgery who had such severe fibrosis that the sciatic nerve was adherent to the piriformis and could not be identified by standard dissection. The workaround was a more proximal approach, tracing the nerve from its origin at the sacral plexus before it reached the foramen. This added time but avoided blind dissection in a scarred field. Sometimes the boundaries themselves shift. The sacrotuberous ligament can calcify with age, narrowing the foramen. I have seen imaging studies where the calcified ligament appeared to compress the posterior femoral cutaneous nerve, producing symptoms that mimicked lumbar pathology. Treatment required ligament release rather than anything lumbar. The greater sciatic foramen is not a simple hole. It is a complex gateway with multiple nerves and vessels arranged in a spatial relationship that varies enough to require real understanding, not just memorization. The practical takeaway is to identify the large, consistent structures first, trace the smaller ones from them, and always account for variation when planning procedures or interpreting clinical findings.


