Understanding the Glasgow Smile: Historical and Anatomical Overview
The Glasgow smile is a term used in forensic medicine and conflict documentation to describe facial lacerations that extend horizontally from the corners of the mouth toward the ears, following the natural nasolabial fold. The resulting wound pattern resembles a forced grin, which is how the term originated. It is not a medical condition, a surgical procedure, or a legitimate technique of any kind. It is a form of facial mutilation that has appeared in documented cases of torture and armed conflict. The terminology entered wider usage during the 1990s, reportedly first gaining attention through reports from Northern Ireland, though the physical pattern of such injuries has been recorded in conflicts worldwide. Medical and legal professionals use the term primarily for identification, documentation, and prosecution purposes. Researchers in human rights law, forensic pathology, and trauma surgery will encounter the phrase in case studies and court evidence rather than in any instructional context.
The Glasgow Smile Anatomy Of A Notorious Torture Method
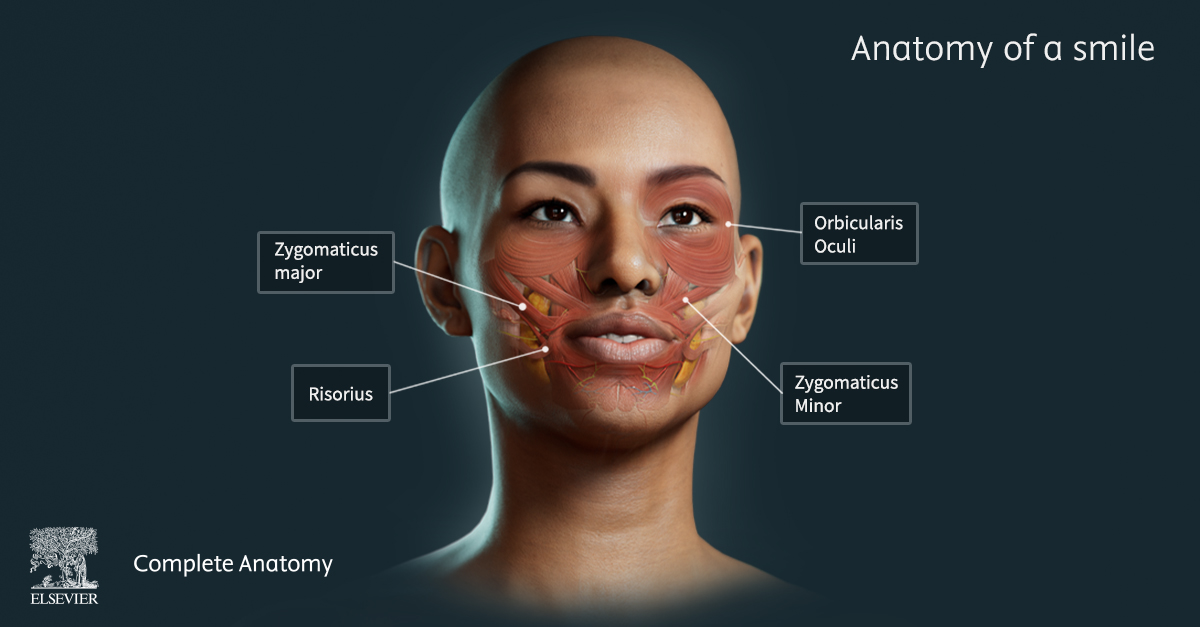
Anatomically, these injuries typically traverse the buccal mucosa, the orbicularis oris muscle, and can extend into the parotid gland region depending on depth and vector. The facial nerve (CN VII) runs through the parotid and delivers motor innervation to the muscles of facial expression, making preservation a major concern in any reconstructive effort. The parotid duct (Stensen's duct) and the facial artery and vein are also at risk in this zone. When the laceration misses these structures, healing is considerably more straightforward. When they are involved, functional and cosmetic outcomes degrade rapidly without specialized intervention. The wounds are almost never clean incisions. In documented cases, the tissue disruption is irregular, with avulsion components, bruising along the wound margins, and contamination from the environment or objects used. This makes both the initial trauma assessment and the later forensic analysis more complex than a simple linear cut would suggest.
Clinical and Forensic Considerations
From a reconstructive surgery standpoint, repair of these injuries follows standard principles for facial lacerations but with additional complexity due to the location and the typical circumstances of injury. Multilayer closure is essential. The inner mucosal layer must be approximated first using absorbable suture material, typically 4-0 or 5-0 chromic gut or vicryl. The muscle layer requires careful realignment of the orbicularis oris fibers to preserve oral continence and symmetry during animation. The skin layer follows with fine non-absorbable sutures, usually 6-0 or 7-0 nylon or prolene, placed with everting techniques to minimize keloid formation. The practical challenge most clinicians face is that these injuries frequently present in conditions far removed from a controlled operating room. Limited lighting, inadequate anesthesia, concurrent injuries requiring prioritization, and lack of specialized instrumentation all factor into outcomes. I once worked through a case where the initial repair had been attempted in a field setting with insufficient local anesthetic and crude suturing technique. The result was significant asymmetry at rest and visible tethering during movement. The revision surgery took approximately three hours under general anesthesia, required a reverse-L preauricular incision for parotid exposure, and ended up needing a fascial graft to restore muscular continuity. Without that secondary intervention, the patient would likely have suffered permanent oral incompetence and a visibly distorted smile.
Get the Full Details

Common Pitfalls in Initial Management
One thing that consistently catches people unprepared is the assumption that straightforward exploration and closure is sufficient. The facial nerve branches in this region follow a somewhat consistent pattern, but anatomical variation is common enough that relying solely on surface landmarks is risky. The temporal and zygomatic branches descend obliquely and can be injured up to two centimeters deep before any obvious deficit appears. Delayed recognition of nerve injury is more common than immediate identification in chaotic settings. Another overlooked factor is the degree of tissue loss. Many sources describe these injuries as pure lacerations, but in practice the mechanism often involves tearing and crushing forces that remove small segments of tissue. The defect may look like a simple line on first inspection, but once debridement begins, the actual loss of viable tissue becomes apparent. Planning for local flaps or skin grafts at the outset saves time and reduces the need for difficult decisions under pressure later. Waiting until complications appear before considering reconstructive options is a mistake that shows up repeatedly in the literature.
Limitations and Realities
No reconstructive approach restores pre-injury appearance. Scar tissue is permanent, and even with expert surgical care, visible remodeling occurs over months to years. The psychological impact on survivors is substantial and often requires long-term support beyond what surgical intervention provides. Legal documentation of these injuries, while important for accountability, does not reverse the damage. For clinicians encountering such injuries, the primary resources available are forensic documentation protocols established by organizations such as the Istanbul Protocol, which provides standardized guidelines for documenting torture and ill-treatment. Surgical technique references come frommaxillofacial trauma literature, particularly work published by the International Commission for the Study of Torture and journals like Injury and Journal of Craniomaxillofacial Surgery. There is no shortcut that produces acceptable outcomes without specialized training and equipment.
Documentation and Legal Context
The term appears most frequently in human rights reports and war crimes trials. Medical professionals who examine survivors are expected to produce detailed records that can serve as evidence. The Istanbul Protocol is the governing standard for this work. It specifies photography requirements, measurement techniques, and classification systems that allow findings to be independently verified. Deviations from these standards can undermine the credibility of documentation in legal proceedings. Survivors and their advocates should seek out qualified medical and legal professionals familiar with the protocol rather than attempting self-documentation. Photographs taken without proper scale, lighting, and clinical context are often inadmissible or easily challenged in court. A properly documented file, on the other hand, can remain central to a case for decades. The Glasgow smile is not something that is performed with skill or purpose in any legitimate context. It is a marker of severe violence that requires comprehensive medical, psychological, and legal follow-up. The information above is intended for professionals who encounter these injuries in clinical or forensic settings, not as instruction for any purpose other than understanding and documentation.