Understanding Growth Hormone and What It Actually Does to Your Body
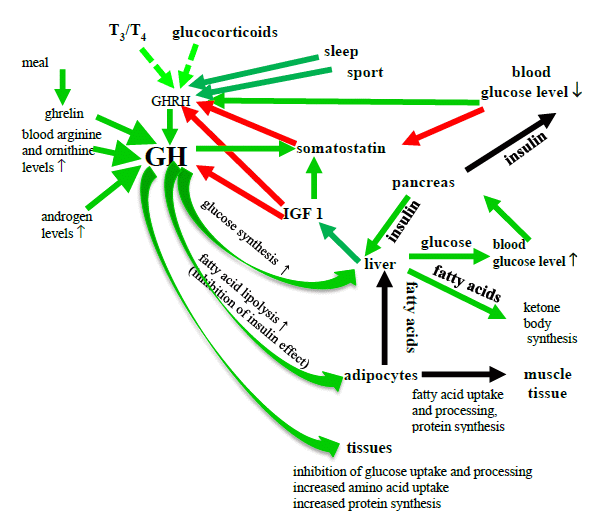
Most people who ask about GH have no idea what they're actually looking at. They see muscle growth charts or fat loss claims and assume there's some dramatic transformation happening. There isn't. Growth hormone is a peptide hormone produced by the anterior pituitary gland, and its primary mechanism involves stimulating the liver and other tissues to produce insulin-like growth factor 1, commonly called IGF-1. That's the real driver of most of the downstream effects people chase. Without IGF-1 being elevated, GH on its own does very little.The physiology is straightforward once you strip away the bro-science. GH binds to receptors on target cells, triggering a JAK2-STAT5 signaling cascade that upregulates protein synthesis and lipolysis. It also reduces glucose uptake in peripheral tissues, which means it has anti-insulin effects at high levels. This is why prolonged GH exposure can contribute to insulin resistance, a point that gets glossed over far too often in casual discussions. When people talk about the GH effect in training and body composition circles, they're usually referring to a combination of increased lean mass, altered fat metabolism, and improved connective tissue repair. The timeline matters here. Acute effects like increased free fatty acid oxidation happen within hours of administration or endogenous release spikes. Structural changes like collagen synthesis and tendon remodeling take weeks to months of sustained elevated IGF-1 levels. Anyone promising you noticeable body composition shifts in two weeks doesn't understand the half-life and cumulative biology involved. Here's something most guides skip: the relationship between GH dose and IGF-1 response is not linear. At lower physiological replacement doses, you see proportionate IGF-1 increases. As you push into supraphysiological ranges, the liver becomes less responsive and more GH just gets cleared without proportional IGF-1 gains. This is called receptor desensitization, and it's why some protocols hit a ceiling where more compound doesn't mean more effect. I ran into this myself when someone tried stacking a higher dose of somatropin assuming linear returns. Bloodwork showed IGF-1 flatlining while fasting glucose crept up. We dropped the dose back to the baseline and added intermittent fasting windows to improve insulin sensitivity, which got the numbers moving again. That workaround of managing the metabolic side effects rather than just throwing more peptide at the problem is what separates people who actually get results from people who just get expensive bloodwork.
Key mechanisms at play: Protein synthesis upregulation through mTOR pathway stimulation, though this is significantly weaker than what you get from resistance training alone or from anabolic steroids. GH is permissive rather than primary in this regard. Lipolysis acceleration via hormone-sensitive lipase activation in adipose tissue. This is one area where GH has genuine measurable impact, particularly on visceral fat. The effect is dose-dependent and becomes more noticeable after several weeks of consistent elevation.
Glycogen sparing and the shift toward fatty acid oxidation during fasting or caloric deficit states. This is useful but easily overstated. It doesn't replace adequate protein intake or a proper training program. There's also the recovery angle that deserves attention. GH increases collagen synthesis in tendons and ligaments. Athletes using it for injury recovery often report faster healing, and the data supports this somewhat. However, the effect is modest compared to something like physical therapy or proper load management. It's an adjunct, not a fix. The measurement question is critical and almost always ignored. Serum GH fluctuates dramatically throughout the day with pulsatile release. A single random blood draw tells you almost nothing about overall GH secretion or treatment efficacy. IGF-1 is the standard marker because it has a longer half-life and reflects integrated production over days. But even IGF-1 varies by age, sex, liver function, and nutritional status. A "normal" IGF-1 range covers roughly 100 to 300 ng/mL depending on the lab, and someone at 120 ng/mL might be perfectly healthy while someone at 280 ng/mL could be running exogenous GH. Context is everything.
Get the Full Details

One counter-intuitive point: higher GH levels don't automatically mean better outcomes. Chronically elevated GH from exogenous sources suppresses your natural production through negative feedback on the hypothalamus and pituitary. After cessation, recovery of endogenous secretion is variable. Some people bounce back within weeks. Others take months or never fully restore baseline pulsatility. The literature on post-cycle recovery is thin, largely because ethical constraints limit long-term follow-up studies. Common pitfalls people make when working with GH protocols include ignoring baseline metabolic markers, skipping regular IGF-1 monitoring, and assuming more frequency equals better results. Once-daily dosing is standard for most recombinant somatropin formulations. Splitting doses between morning and evening might theoretically keep levels steadier, but the evidence for superior outcomes is weak. The half-life of methionyl GH is roughly 2 to 4 hours, and the biological half-life of IGF-1 is around 10 to 15 hours, so the dosing window isn't as tight as some protocols suggest. The edge case that catches people out is concurrent use with other compounds that affect insulin sensitivity. DHEA, high-dose omega-3s, and certain sleep interventions can improve the metabolic environment enough that lower GH doses produce the same IGF-1 response. I've seen people increase their GH by 50 percent when the real issue was poor sleep quality and chronic stress elevating cortisol, which blunts the GH-IGF-1 axis. Fixing the sleep first, then reassessing, resolves more problems than increasing the dose ever will.
On the limitations side, GH is not a magic bullet for fat loss or muscle growth. The average fat loss benefit in clinical studies is in the range of 1 to 2 kilograms of fat mass over 12 to 24 weeks when combined with exercise and diet. Muscle mass gains are similarly modest without concurrent resistance training and adequate protein. The side effect profile includes carpal tunnel syndrome, joint pain, edema, and the insulin resistance issues I mentioned. For healthy young people considering GH for performance enhancement, the risk-reward ratio is poor. The data simply doesn't support dramatic transformations. If you're looking at GH for a legitimate medical indication like confirmed deficiency or certain wasting conditions, the calculus changes entirely. In those cases, replacement therapy is well-supported and benefits are clear. The problem is the gray area where people self-prescribe or use sources that bypass medical supervision. That's where things get messy, and where the most avoidable complications happen. The practical takeaway is that GH works, but narrowly and predictably. It improves body composition slightly, aids recovery modestly, and carries real metabolic costs. Understanding the IGF-1 dependence, monitoring the right markers, and managing the side effects proactively makes the difference between a protocol that produces results and one that just produces expensive urine and rising fasting glucose.