Getting Started With Microbial Disease Analysis
Most people think germ theory is settled science from 1880, but working with it day to day reveals it's far messier than the textbooks suggest. I've spent years running cultures, sequencing pathogens, and troubleshooting why a case that looks textbook on paper doesn't actually behave that way in practice. This guide covers the practical side of how germ theory applies to real diagnostic and research work, including where it breaks down and what you do instead.The Germ Theory Of Disease Unveiling The Hidden Enemies Within
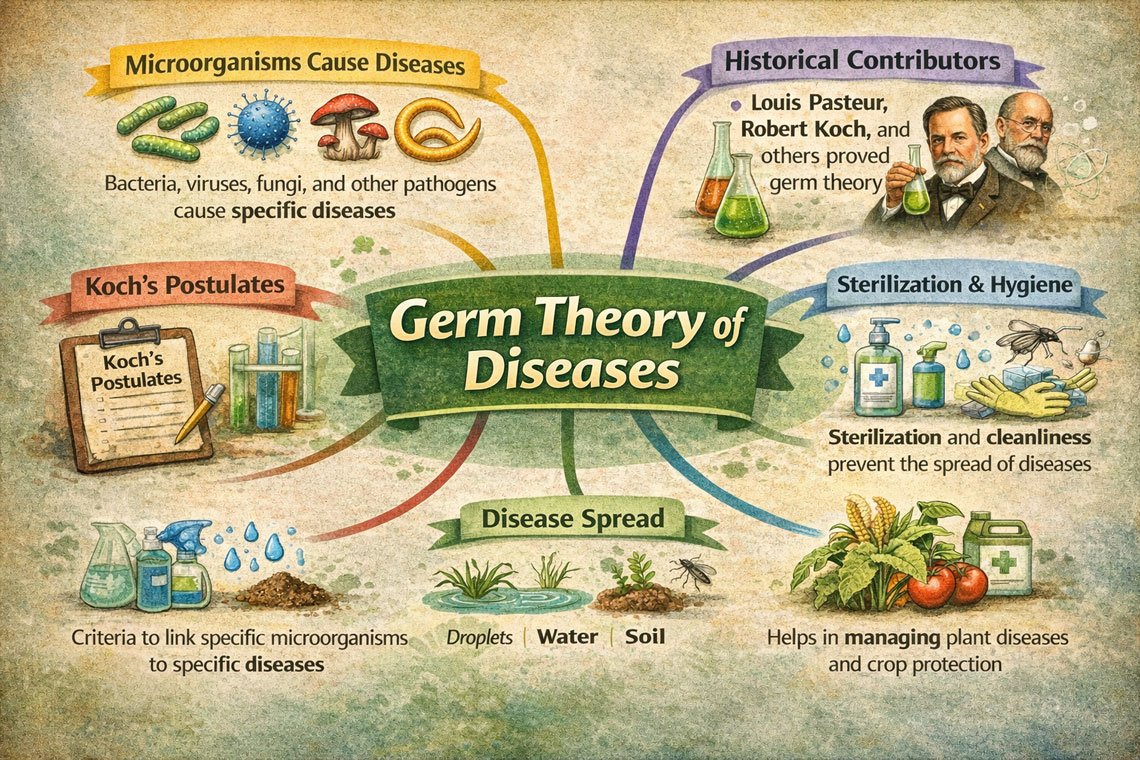
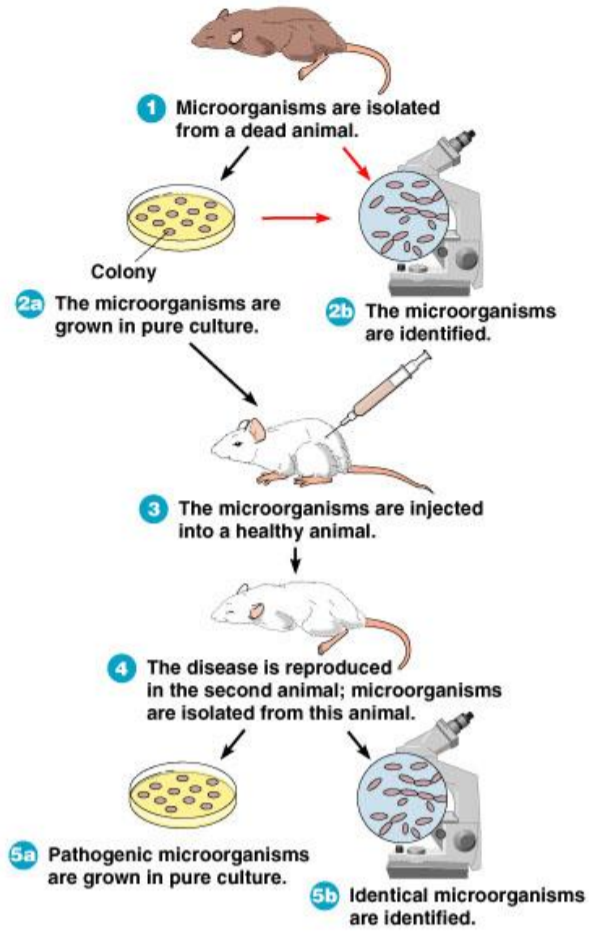
The core principle is straightforward: specific microorganisms cause specific diseases. Koch's postulates from the late 19th century laid the foundation — you isolate the organism from a sick host, grow it in pure culture, introduce it to a healthy host, and confirm the same disease appears. That framework still underpins modern clinical microbiology, but it was never the complete picture, and treating it like one will get you in trouble fast. Here's what the postulates don't tell you: many clinically important pathogens can't be cultured using standard laboratory methods. Helicobacter pylori took decades to isolate properly because it needs microaerophilic conditions and specific growth media that most undergraduate labs don't stock. Mycoplasma pneumoniae lacks a cell wall, so Gram staining gives you nothing, and it grows painfully slowly on specialized media. Then there are viruses, prions, and obligate intracellular bacteria like Rickettsia and Chlamydia, which simply won't grow on artificial media at all. Koch's fourth postulate — re-isolating the organism from the experimentally infected host — becomes irrelevant when you're working with agents you can't culture in the first place. The practical workaround I use involves shifting from culture-dependent to culture-independent detection. PCR and multiplex PCR panels have largely replaced traditional culture for many respiratory and gastrointestinal pathogens. I run a respiratory panel on any patient presenting with unexplained pneumonia where sputum cultures come back negative, and it catches things like Bordetella pertussis or Legionella pneumophila that standard bacterial cultures miss entirely. For Legionella specifically, urinary antigen testing is faster than culture but only detects L. pneumophila serogroup 1, so you'll miss other serogroups and species if you rely on it alone. I always pair it with PCR when the clinical picture suggests Legionnaires' disease.
Another counter-intuitive point that beginners miss: the presence of a microorganism doesn't automatically mean it's the causative agent. Colonization is extremely common and easily confused with infection. I had a case last year where a wound culture grew MRSA repeatedly, and the treating team was convinced it was a surgical site infection. The wound looked clean, the patient had no systemic signs, and the MRSA was growing from superficial swabs rather than deep tissue. I recommended a deep tissue biopsy instead of continuing antibiotics, and the biopsy showed no organisms at all. The MRSA was just colonizing the skin around the wound. Switching to that approach saved the patient from unnecessary IV antibiotics and a prolonged hospital stay. Opportunistic pathogens add another layer of complexity. Pseudomonas aeruginosa and Staphylococcus aureus are common nosocomial isolates, but their significance depends entirely on the clinical context. A catheter-related bloodstream infection with Pseudomonas in an immunocompromised patient is treated very differently from the same organism growing from a tracheal aspirate in a mechanically ventilated patient who has no fever or elevated white blood cell count. The microbiology lab report doesn't include clinical correlation. It's your job to overlay that context onto every positive result. When you're building a diagnostic workflow around germ theory, start with specimen quality. I've seen too many wasted resources on poor samples. A sputum sample that's mostly saliva — you can tell by seeing more than ten squamous epithelial cells per low-power field on Gram stain — is worthless for lower respiratory tract diagnosis. Reject it and ask for a proper sample. Same principle applies to urine cultures: a clean-catch midstream specimen is essential, and even then, contamination from periurethral flora is inevitable if the patient hasn't followed proper collection technique. Colony counts below 10^3 CFU/mL in a properly collected specimen usually represent contamination rather than true bacteriuria.
Antimicrobial susceptibility testing is where germ theory meets practical treatment decisions. Broth microdilution remains the gold standard for determining minimum inhibitory concentrations, but it takes 16 to 24 hours for most organisms. If you need faster results, MALDI-TOF mass spectrometry can identify organisms in minutes and detect certain resistance mechanisms like ESBL production through direct-on-plate testing in under two hours. I use it extensively for overnight calls when we get positive blood culture gram stains and need to guide empiric therapy before full ID and sensitivities are available. The limitations of germ theory as a standalone framework are worth stating plainly. It doesn't account for the human microbiome's role in health and disease. Gut dysbiosis is linked to conditions ranging from Clostridioides difficile infection to inflammatory bowel disease, but germ theory in its classical form doesn't have a good answer for why disrupting a microbial community causes disease when no single pathogen is identified. The hygiene hypothesis similarly falls outside the classic model — reduced early-life microbial exposure correlates with increased autoimmune and allergic conditions, but there's no single germ to point at as the culprit. If you're working in a resource-limited setting without access to molecular diagnostics, you'll need to rely more heavily on culture and phenotypic identification. The workaround here is investing in good quality control and maintaining a well-stocked reference library of common local pathogens. I keep strain collections of our most frequent isolates and run them through our identification systems regularly to catch drift in reagent performance or instrument calibration. A misplaced decimal in an MIC value can flip a susceptible result to resistant, and that changes everything about treatment.
Get the Full Details

For anyone just starting out in clinical or research microbiology, the single most important habit is learning to read a Gram stain properly before you ever touch a culture plate. It takes time — I spent months doing nothing but Gram stains in my fellowship — but it pays off immediately. You'll know whether your culture is likely contaminated, whether your specimen is appropriate, and what organism you're probably dealing with before the incubator even finishes its first cycle. Everything after that is refinement.