Understanding Self-Preservation in Psychoanalytic Theory
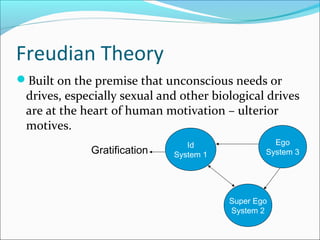
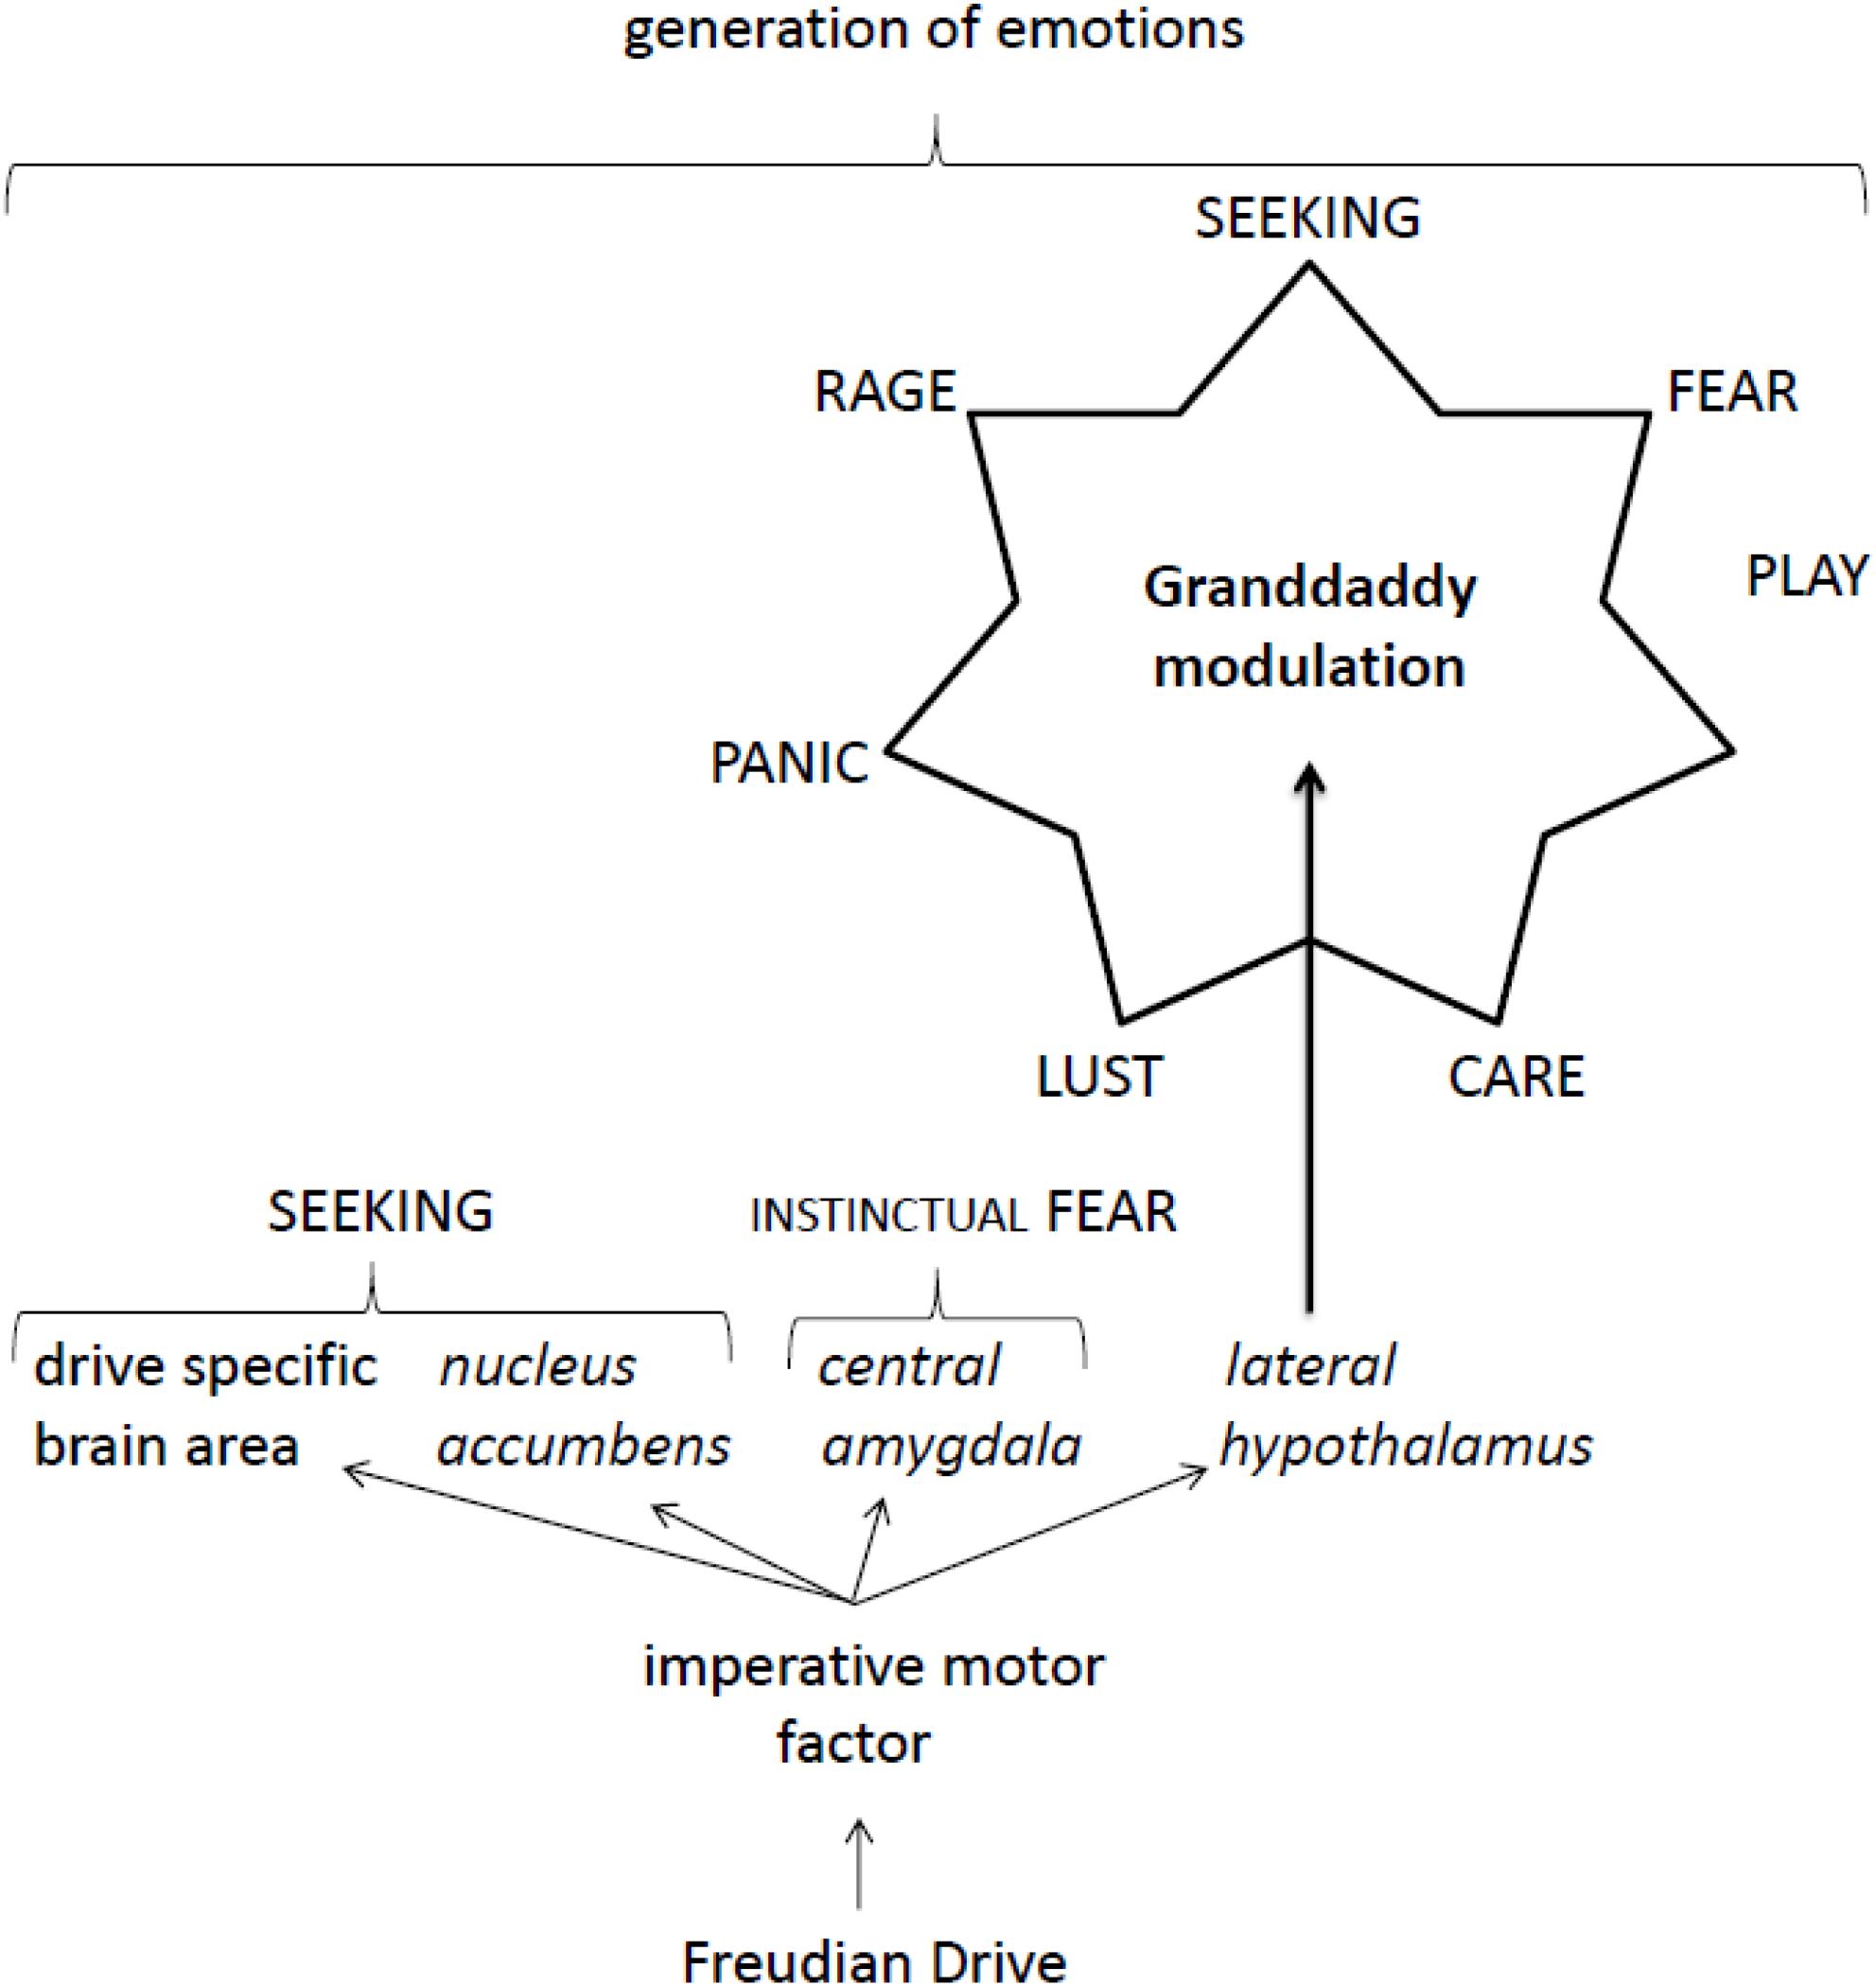
The idea that Freud had a single unified concept explaining everything is mostly a later simplification. What actually exists is a cluster of related ideas — Eros, the instinct for self-preservation, the death drive, and the compulsion to repeat — that together form something close to what people now search for under The Freudian Drive To Survive The Concept That Explains Everything. It's not one tidy theory. It's more like a toolbox Freud kept adding to over decades, and he never quite resolved the tensions between the pieces. Freud's earliest model of human motivation was built around what he called the ego-instincts — basically the biological and psychological mechanisms that keep an organism alive. He grouped these under the umbrella of sexual instinct early on, which sounds strange until you remember he was using "sexuality" in a much broader sense than we do today. For Freud, libido wasn't just about reproduction or pleasure. It was a general life energy, a driving force behind growth, attachment, creativity, and yes, survival itself. The pivot came in 1920 with Beyond the Pleasure Principle. Freud had been treating patients with shell shock from World War I, people who kept reliving their trauma in nightmares. The pleasure principle — the idea that the psyche seeks pleasure and avoids pain — didn't explain why someone would consciously or unconsciously repeat something awful over and over. That's when he introduced the death drive, or Thanatos, alongside the life drives (Eros). The death drive is the urge toward dissolution, returning to an inanimate state. Eros is the urge to bind, connect, build, and survive. Together they form a kind of psychic push-pull that Freud increasingly treated as the fundamental engine of all behavior.
So when someone talks about The Freudian Drive To Survive The Concept That Explains Everything, what they're usually pointing at is this tension. Survival isn't just a biological function. It's a psychic battleground between the force that wants to hold life together and the force that wants to tear it apart. Everything — love, war, addiction, art, neurosis — gets filtered through that contradiction. I've spent years unpacking how this framework applies to clinical work, and the first thing you learn is that it doesn't work the way textbooks make it sound. The death drive isn't just a metaphor for suicidal thoughts. It shows up in places you wouldn't expect. A patient who keeps sabotaging a successful therapy relationship. A person who unconsciously recreates the exact dynamics of their childhood abuse in every romantic relationship they enter. That's not a desire for death in the literal sense. That's the compulsion to repeat, which Freud himself admitted was the trickiest part of his model to operationalize. Here's a specific problem I ran into that the literature barely addresses. I was working with a client who had developed a severe psychosomatic condition — chronic migraines with no identifiable medical cause. The standard reading would be that her Eros drive was being thwarted somehow, her life energy blocked. But after months of analysis, it became clear that the migraines were serving a different function entirely. They were her unconscious way of forcing herself to stop. Not to die. To pause. To survive a life that had become psychologically impossible to sustain without some kind of biological circuit-breaker.
The workaround was to stop treating the symptom as purely defensive and start treating it as communicative. We worked with the idea that the body was doing what the psyche couldn't — creating an enforced cessation. It took about four months of therapy to reframe how she understood her own condition, and the migraine frequency dropped from daily to maybe twice a month. That's not a cure. But it's evidence that the drive to survive often takes indirect routes, and the route matters more than the destination.
Get the Full Details
How The Mechanism Actually Works in Practice
Let me walk through how this plays out when you're actually applying the model rather than just reading about it. The first thing to understand is that Freud never gave us a clean diagnostic manual. He gave us a way of listening. When a patient says something contradictory, repeats a pattern, or resists a line of questioning, you ask yourself which drive is more active in that moment. Is the person reaching toward connection and meaning, or are they dismantling, repeating, or pushing away? The complication is that both drives are always operating simultaneously. You can't isolate one from the other. A person clinging to a toxic relationship isn't just expressing Eros — they're also expressing a death drive, because staying in that situation is slowly killing them. Conversely, someone who appears self-destructive might actually be engaged in a desperate act of self-preservation, trying to control a narrative that otherwise controls them. The survival drive doesn't always look like survival. Sometimes it looks like recklessness. Sometimes it looks like numbness. Sometimes it looks like rage. In my experience, the most useful application of this framework is in understanding resistance. Beginners in psychoanalytic thinking tend to treat resistance as something to break through. The deeper you get, the more you realize that resistance is the psyche's immune response. When a patient refuses to remember something, or changes the subject, or arrives late to sessions repeatedly, they're not being difficult. They're protecting something. The question is always: what is being protected, and from what?
I found that keeping a two-column note system during sessions helped. On one side, I'd track what seemed like life-affirming movement — moments of connection, insight, genuine emotional expression. On the other side, I'd track repetition, sabotage, withdrawal, somatic complaints. After about six weeks, patterns emerged that were invisible in the moment. Usually one drive was dominating, and the therapy work was simply helping the patient become aware of which one was running the show without their knowledge.
The Counter-Intuitive Part Nobody Mentions
Most people assume that strengthening the survival drive means promoting health, growth, and positive thinking. In practice, that's often counterproductive. Pushing someone toward "positive" behavior without addressing the underlying death drive creates what I'd call superficial adaptation. The person functions well on the outside but accumulates unconscious tension that eventually erupts as symptom — depression, addiction, panic, self-sabotage. I've seen this in organizational consulting too. Companies that try to build culture through mandatory positivity and team-building exercises while ignoring systemic sources of existential dread almost always see the behavior reset within eighteen months. The more effective approach, which Freud himself drifted toward in his later work, is to help the death drive become conscious rather than trying to suppress it. When a person can articulate their owndestructive impulses — not act on them, but name them — those impulses lose a significant amount of their automatic power. This is why techniques like free association and dream analysis persisted in psychoanalysis even as other approaches moved toward more structured methods. You can't bypass the death drive through logic. You have to let it speak. Another pitfall I've noticed repeatedly is the assumption that Eros is inherently "good" and the death drive is inherently "bad." That's a moral reading, not a clinical one. Eros can bind people to suffering just as effectively as Thanatos can destroy them. A mother who cannot stop sacrificing herself for her adult child isn't expressing pure love. She's expressing a life drive that has fused with a need for control. The death drive, conversely, is also the source of curiosity, of the therapeutic instinct, of the ability to confront uncomfortable truths. Without it, there's no pressure to change anything at all.

Limitations and Where This Framework Fails
I need to be straightforward about where this model breaks down. It's not falsifiable in any meaningful scientific sense. You can interpret almost any behavior through the lens of Eros and Thanatos, which makes it resistant to disconfirmation. A patient improves — that's Eros winning. A patient deteriorates — that's Thanatos taking over. A patient stays the same — that's both drives in equilibrium. The framework explains everything and therefore predicts nothing specific. This is why I don't use it as a standalone diagnostic tool. It works best as a supplementary lens, layered onto more structured approaches like cognitive-behavioral frameworks, attachment theory, or trauma-informed care. Alone, it's too fluid. The language is rich but imprecise. Two analysts using the same framework can reach opposite conclusions about the same case, and there's no objective way to determine which is correct. There's also the issue of cultural specificity. The death drive concept emerged from a very particular intellectual and historical context — early twentieth-century Vienna, shaped by the horrors of World War I and the intellectual traditions of Schopenhauer and Nietzsche. Applying it directly to patients from different cultural backgrounds without adaptation can lead to misinterpretation. What looks like a death drive in one cultural context might be a spiritual practice, a communal coping mechanism, or a rational response to systemic oppression in another.
If you're looking for a more empirically grounded alternative, attachment theory offers testable predictions about how early relational patterns shape survival strategies. Trauma neuroscience provides measurable correlates for what Freud described metaphorically. I use the Freudian framework when I need to understand the deeper symbolic layer of a person's suffering, but I rely on attachment and trauma research when I need to plan treatment and measure progress.
Practical Steps for Working With This Concept
Start by reading Freud's Beyond the Pleasure Principle directly. The 1920 text is dense but short, and it's the primary source for everything that follows. Don't rely on textbook summaries. Then move to The Ego and the Id for the structural model that contextualizes the drive theory. After that, Anna Freud's The Ego and the Mechanisms of Defense is where the abstract becomes operational. When applying this to your own work or personal understanding, I'd recommend keeping a weekly reflection log. Write down three moments where you noticed a pattern of repetition or self-sabotage, and three moments where you noticed genuine forward movement or connection. Look for the underlying question each time: what is being preserved, and at what cost? The goal isn't to eliminate the death drive from your life. The goal is to stop letting it operate in the background while you pretend it isn't there. For clinical practitioners, the key skill is learning to tolerate ambiguity. This framework doesn't give you quick answers. It gives you a more honest vocabulary for the things that are already happening in the room. If you're looking for a five-step method to fix a problem, this isn't it. If you're looking for a way to think more clearly about the contradictions in human motivation, it's one of the best tools available, even if it's an imperfect one.