Understanding Extreme Obesity: What It Actually Looks Like
I spent about three years consulting for healthcare facilities that specialized in bariatric care, which means I saw firsthand how extreme obesity presents itself in clinical settings. The public tends to think of it as a matter of scale numbers, but anyone who has worked in this space knows the reality is far more complex than counting pounds or reading BMI charts. When a patient reaches critical mass levels, every single aspect of daily life becomes a negotiation with physics. The medical literature typically defines morbid obesity as a BMI exceeding 40, though in practice, patients we classified as critically obese often carried well over 500 pounds. Their bodies were not merely larger versions of average human frames; they were structurally different systems with fundamentally different mechanics. Joint loads, cardiovascular demands, respiratory patterns—all of these operated on entirely different parameters than someone carrying a moderate amount of excess weight.
How Medical Teams Approach the Heaviest Patients
The first practical hurdle any facility encounters is equipment. Standard hospital beds max out around 350 to 500 pounds depending on the model, and most examination tables are rated even lower. We had to order specialized bariatric beds that could handle up to 1,000 pounds, and those came at roughly three times the cost of regular hospital beds. Getting them into the building sometimes required reinforcing door frames and hallway floors because standard construction just would not support the mass being moved through narrow corridors. Here is something most people do not consider: diagnostic imaging becomes genuinely difficult at extreme weights. Standard CT scanners have weight limits around 450 pounds, and MRI tables are similarly constrained. When a patient exceeded those limits, we had to arrange for portable X-ray units or transfer them to specialized facilities equipped for super-obese individuals. Those transfers alone required teams of at least six to eight trained staff members and pneumatic lift systems to move the patient safely.
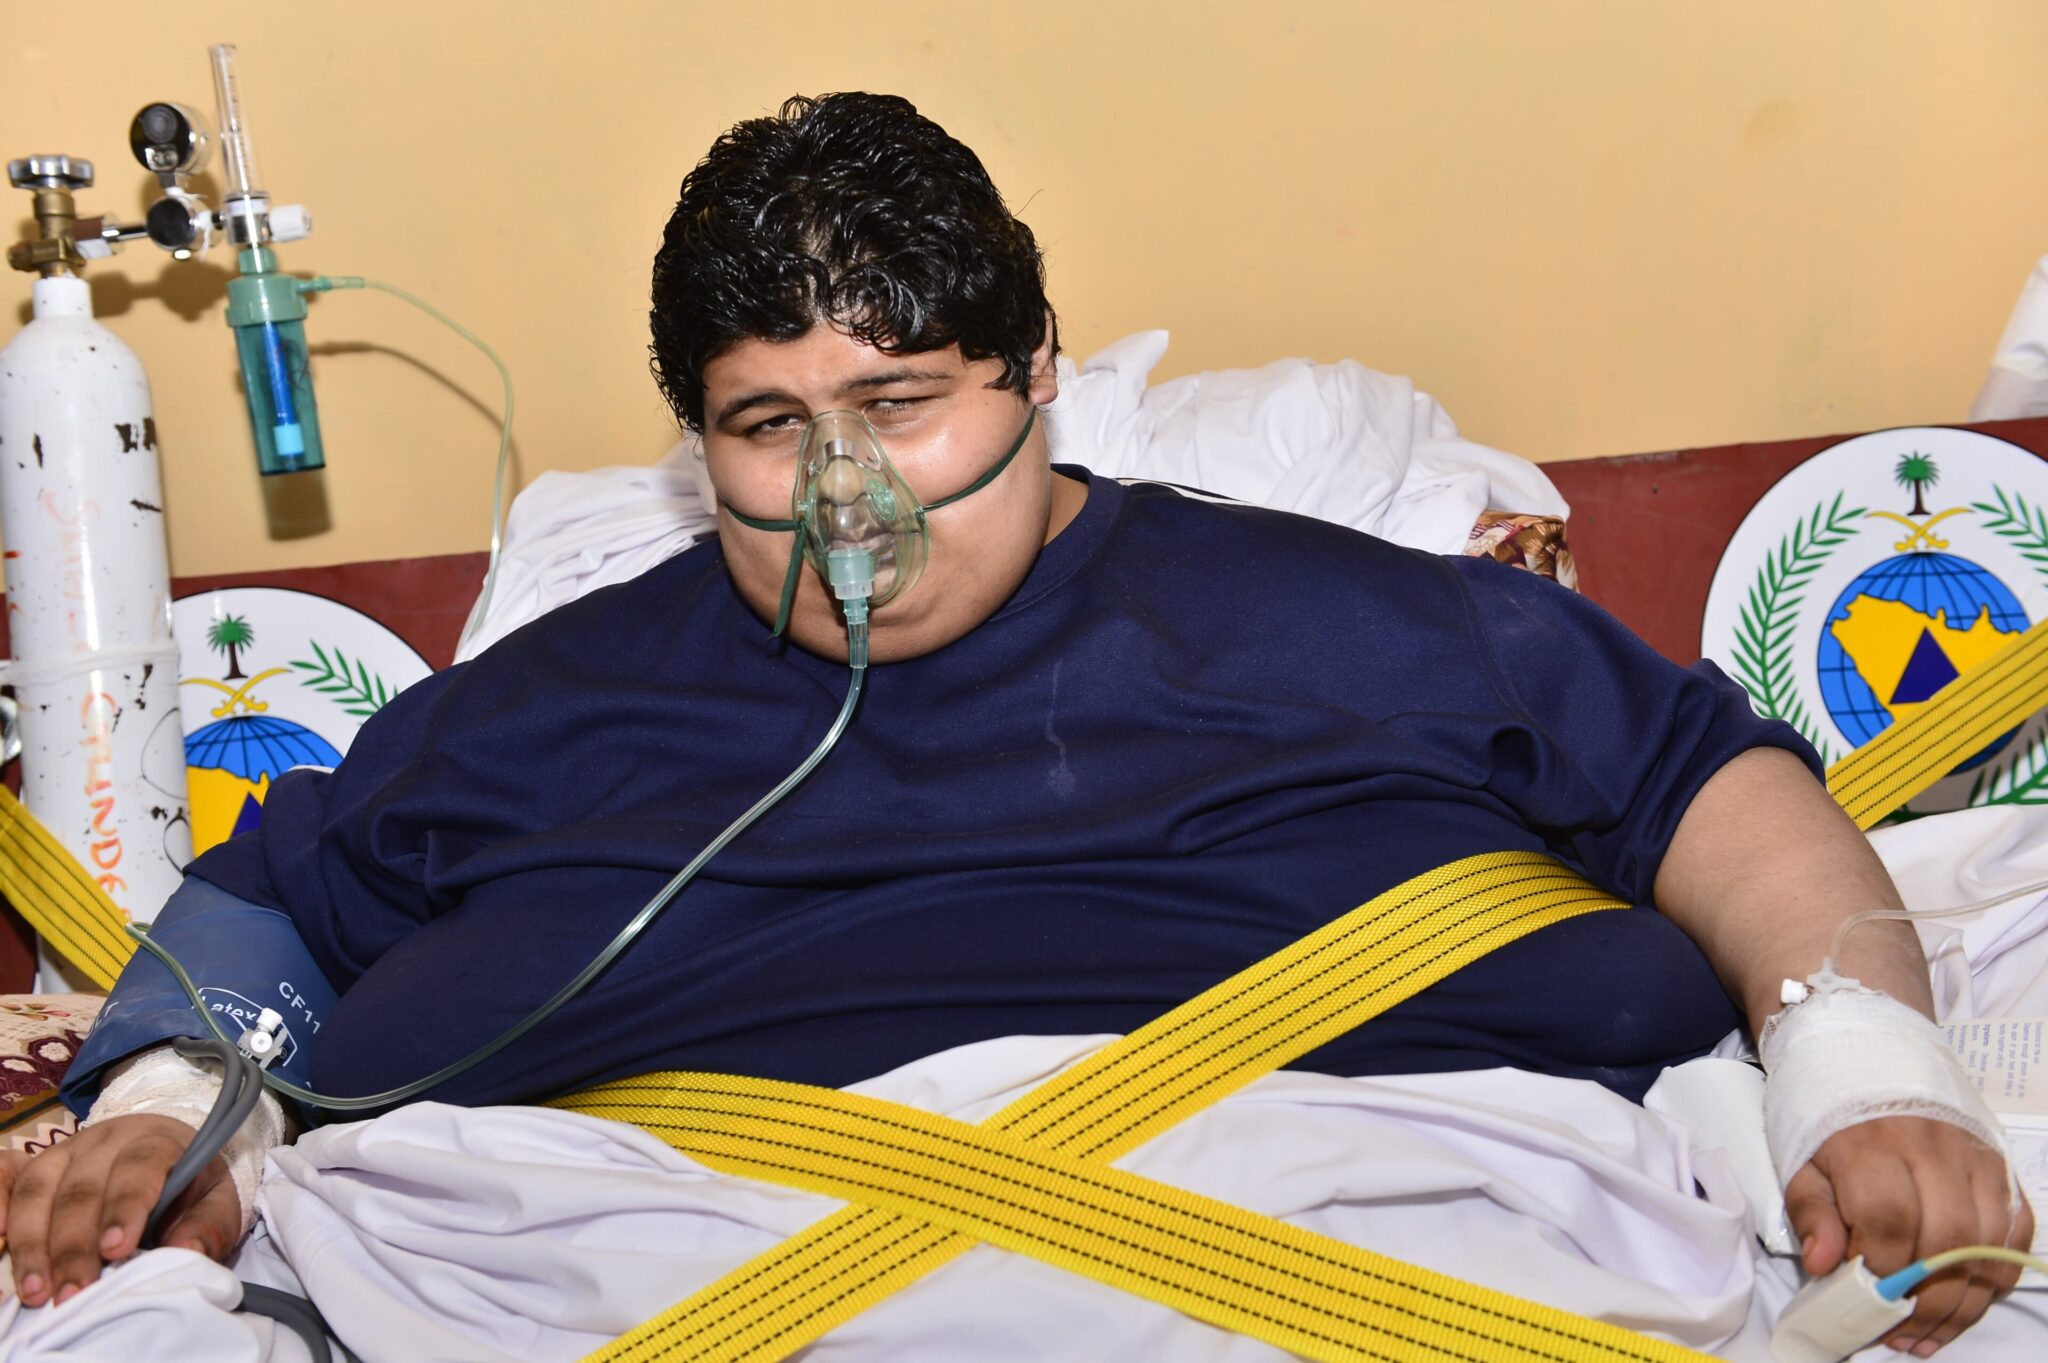
The Fattest Person In The World A Striking Portrait Of Extreme Obesity
When discussing the heaviest individuals ever documented, the medical record consistently points to Jon Brower Minnoch from Seattle, who peaked at approximately 1,400 pounds in the early 1970s before passing away in 1983. His case remains the most extensively studied example of extreme obesity in medical literature, and understanding his situation reveals why this condition is so devastating beyond the obvious physical burden. Minnoch was hospitalized repeatedly throughout his life, spending a combined total of roughly two decades in hospitals across multiple states. At his peak weight, he could barely breathe while lying flat, needed multiple people to help him change position, and his heart was working so hard just circulating blood through his massive body that he developed chronic heart failure. The sheer metabolic cost of maintaining that much tissue meant his caloric needs were astronomical, yet his mobility was so restricted that he could not burn anywhere near enough calories to prevent further weight gain. Another frequently cited case is Emmanuel Luis Como from Brazil, who weighed around 1,366 pounds before undergoing bariatric surgery in the mid-2000s. Unlike Minnoch, Como was able to lose significant weight through surgical intervention and lived longer after treatment, though his story demonstrates the enormous medical resources required even to begin addressing extreme obesity. His surgery alone took nearly twelve hours and involved a team of twenty medical professionals.
Get the Full Details

Why Extreme Obesity Develops and Persists
The common assumption is that extreme obesity stems purely from poor dietary choices and sedentary behavior, and while those factors contribute significantly, the actual biological mechanisms are far more tangled. Leptin resistance plays a massive role here. Leptin is the hormone that signals fullness to the brain, and in most super-obese patients, their bodies produce enormous amounts of it simply because they have so much adipose tissue. The problem is that their brains stop responding to the hormone entirely, so they never receive the satiety signal regardless of how much they have eaten. Gut microbiome composition also differs substantially in extreme obesity cases. Research conducted at Johns Hopkins and several other institutions found that super-obese patients harbored distinctly different bacterial populations in their digestive tracts compared to moderately obese individuals. These microbial communities appear to extract more calories from the same foods and may influence hunger signaling through metabolic byproducts. That finding completely changed how our facility approached nutritional counseling, because it meant telling patients to simply eat less was biologically naive.
Practical Barriers That Make Treatment Nearly Impossible
I want to share a specific scenario that illustrates why extreme obesity cases rarely resolve through conventional methods. One of our patients, a woman we will call Patricia, weighed approximately 680 pounds when she first arrived at our bariatric program. She met every criteria for surgical intervention: her BMI was over 45, she had hypertension and type two diabetes, and she had attempted multiple supervised diet programs without lasting success. The obstacle was not medical eligibility, it was logistics. Our surgical suite had a maximum patient weight of 600 pounds. Patricia needed to lose at least 80 pounds before she could even be considered for surgery, but losing that weight while weighing 680 pounds required calorie intake so severely restricted that she would have been clinically malnourished within weeks. We arranged for her to use a specialized bariatric pharmacy that compounded low-calorie, high-protein shakes designed specifically for pre-surgical weight loss in super-obese patients, which helped her drop 60 pounds over four months. Even then, her first postoperative complication was a skin infection under the massive apron of abdominal tissue that had formed from years of extreme weight. Standard wound care protocols did not account for the depth and moisture retention in those skin folds, so infections would develop in places that light simply could not reach. We ended up using specialized UV-absorbing powders and positioning her on beds to allow drainage, which was not part of any standard postoperative guideline. That workaround, developed through trial and error with our wound care specialists, became part of our facility protocol for all subsequent patients above 500 pounds.
The Psychological Dimension Most People Ignore
Extreme obesity almost always coincides with severe psychological comorbidity, though the relationship is circular rather than linear. Patients did not become obese because of depression, and they did not become depressed solely because of obesity, but the two conditions reinforced each other continuously. Stigma from healthcare providers themselves was a factor I observed directly. Several physicians on our team, albeit unintentionally, treated super-obese patients with less thoroughness, which led to missed diagnoses and delayed interventions. One of our nurses, Maria, kept a private log of patient interactions that revealed something disturbing: surgeons spent an average of four minutes per consultation with super-obese patients compared to twelve minutes for patients under 300 pounds. The time difference was statistically significant and correlated with lower rates of appropriate diagnostic testing for the heaviest group. After we presented those findings to the hospital administration, mandatory extended consultation protocols were implemented for all patients above 400 pounds, which improved detection rates for conditions like sleep apnea and venous thromboembolism.

What Recovery Actually Looks Like Long Term
Successful weight reduction in super-obese patients creates an entirely new set of problems that no one prepares families for. When someone loses three hundred or four hundred pounds, the skin does not contract like it would after moderate weight loss. Patients end up hanging in massive folds that trap moisture, harbor fungal infections, and cause chronic pain from the constant pulling on the spine and joints. Secondary surgeries to remove excess skin, called body contouring procedures, are routinely recommended but rarely covered by insurance for bariatric patients because insurers classify them as cosmetic despite being medically necessary. Our most successful long-term outcomes involved patients who committed to a minimum of eighteen months of multidisciplinary follow-up care that included nutritional counseling, psychological support, physical therapy adapted for limited mobility, and regular monitoring for electrolyte imbalances that develop during rapid weight loss. Patients who dropped out of follow-up care within the first six months, which happened in roughly forty percent of cases, tended to regain weight because they had not developed the behavioral patterns and support structures needed to maintain their new lifestyle.
Why the Statistics Keep Changing
World records for human weight fluctuate because measurement standards changed over time and because documentation quality varies across countries. During the 1970s and 1980s, Guinness World Records verified the heaviest individuals through documented hospital measurements, but as bariatric surgery became more common and effective, fewer people reached the extreme weights that characterized earlier decades. Current estimates suggest that the global prevalence of class three obesity, which is BMI over 40, has roughly doubled since the year 2000, meaning the heaviest recorded weights today may actually exceed historical figures even though surgical interventions prevent some individuals from reaching those extremes. The World Health Organization reported in 2022 that extreme obesity was increasing at twice the rate of moderate obesity, which creates a growing population that healthcare systems around the world are completely unequipped to handle. Most hospitals still do not have adequate bariatric equipment, and there is a severe shortage of physicians trained in treating patients above 500 pounds. This gap between clinical need and available resources is where many of the worst outcomes occur, because patients either avoid seeking care altogether or receive substandard treatment when they do present at facilities unprepared for their needs.