Understanding Irregular Bones in Practice
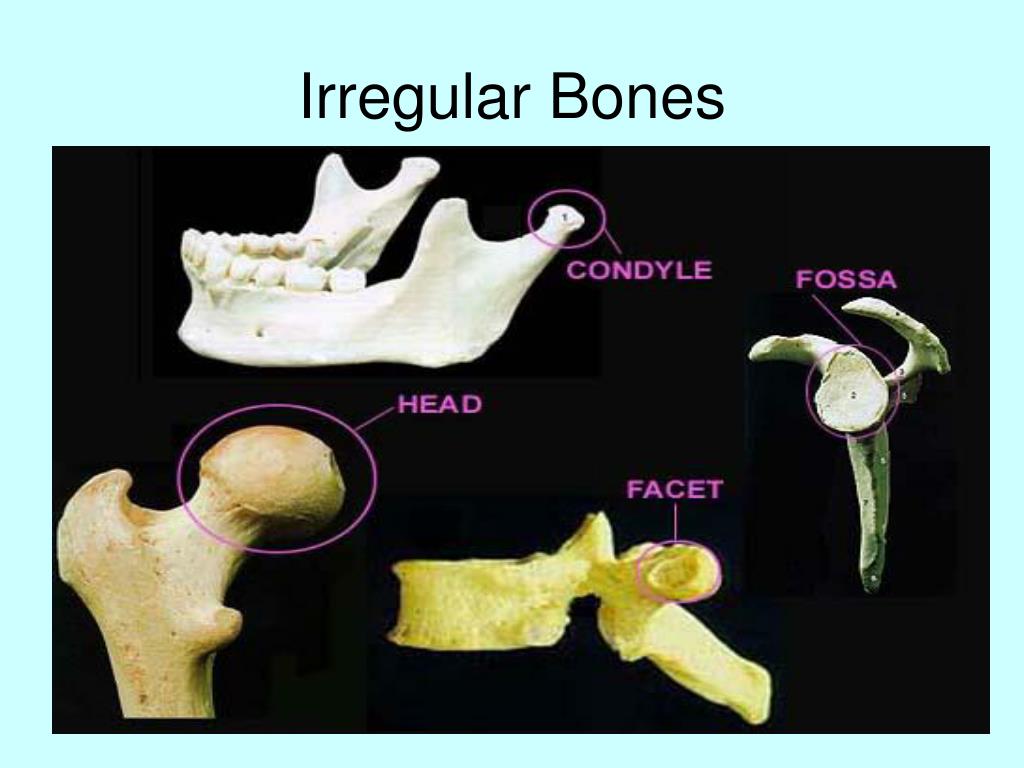
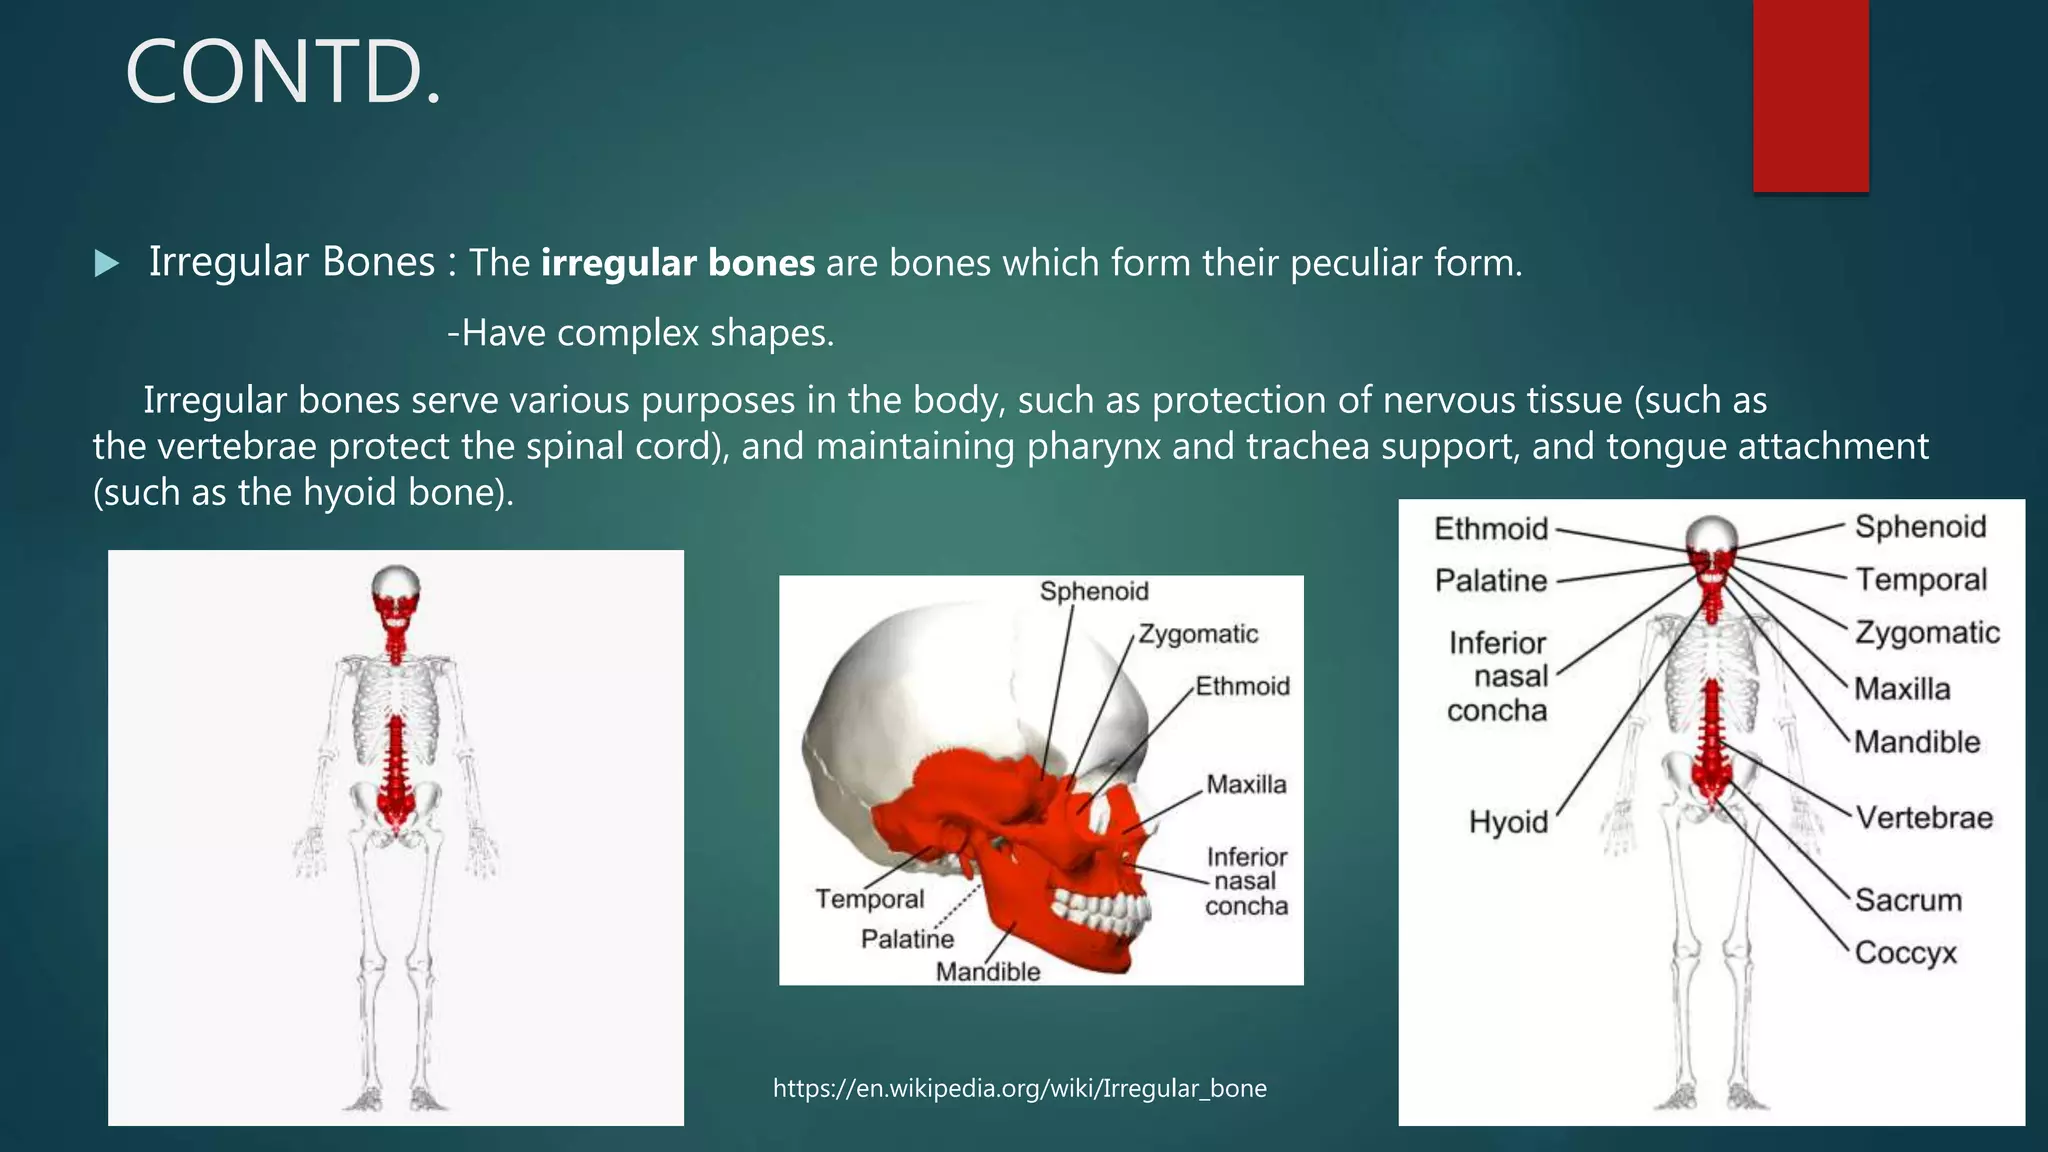
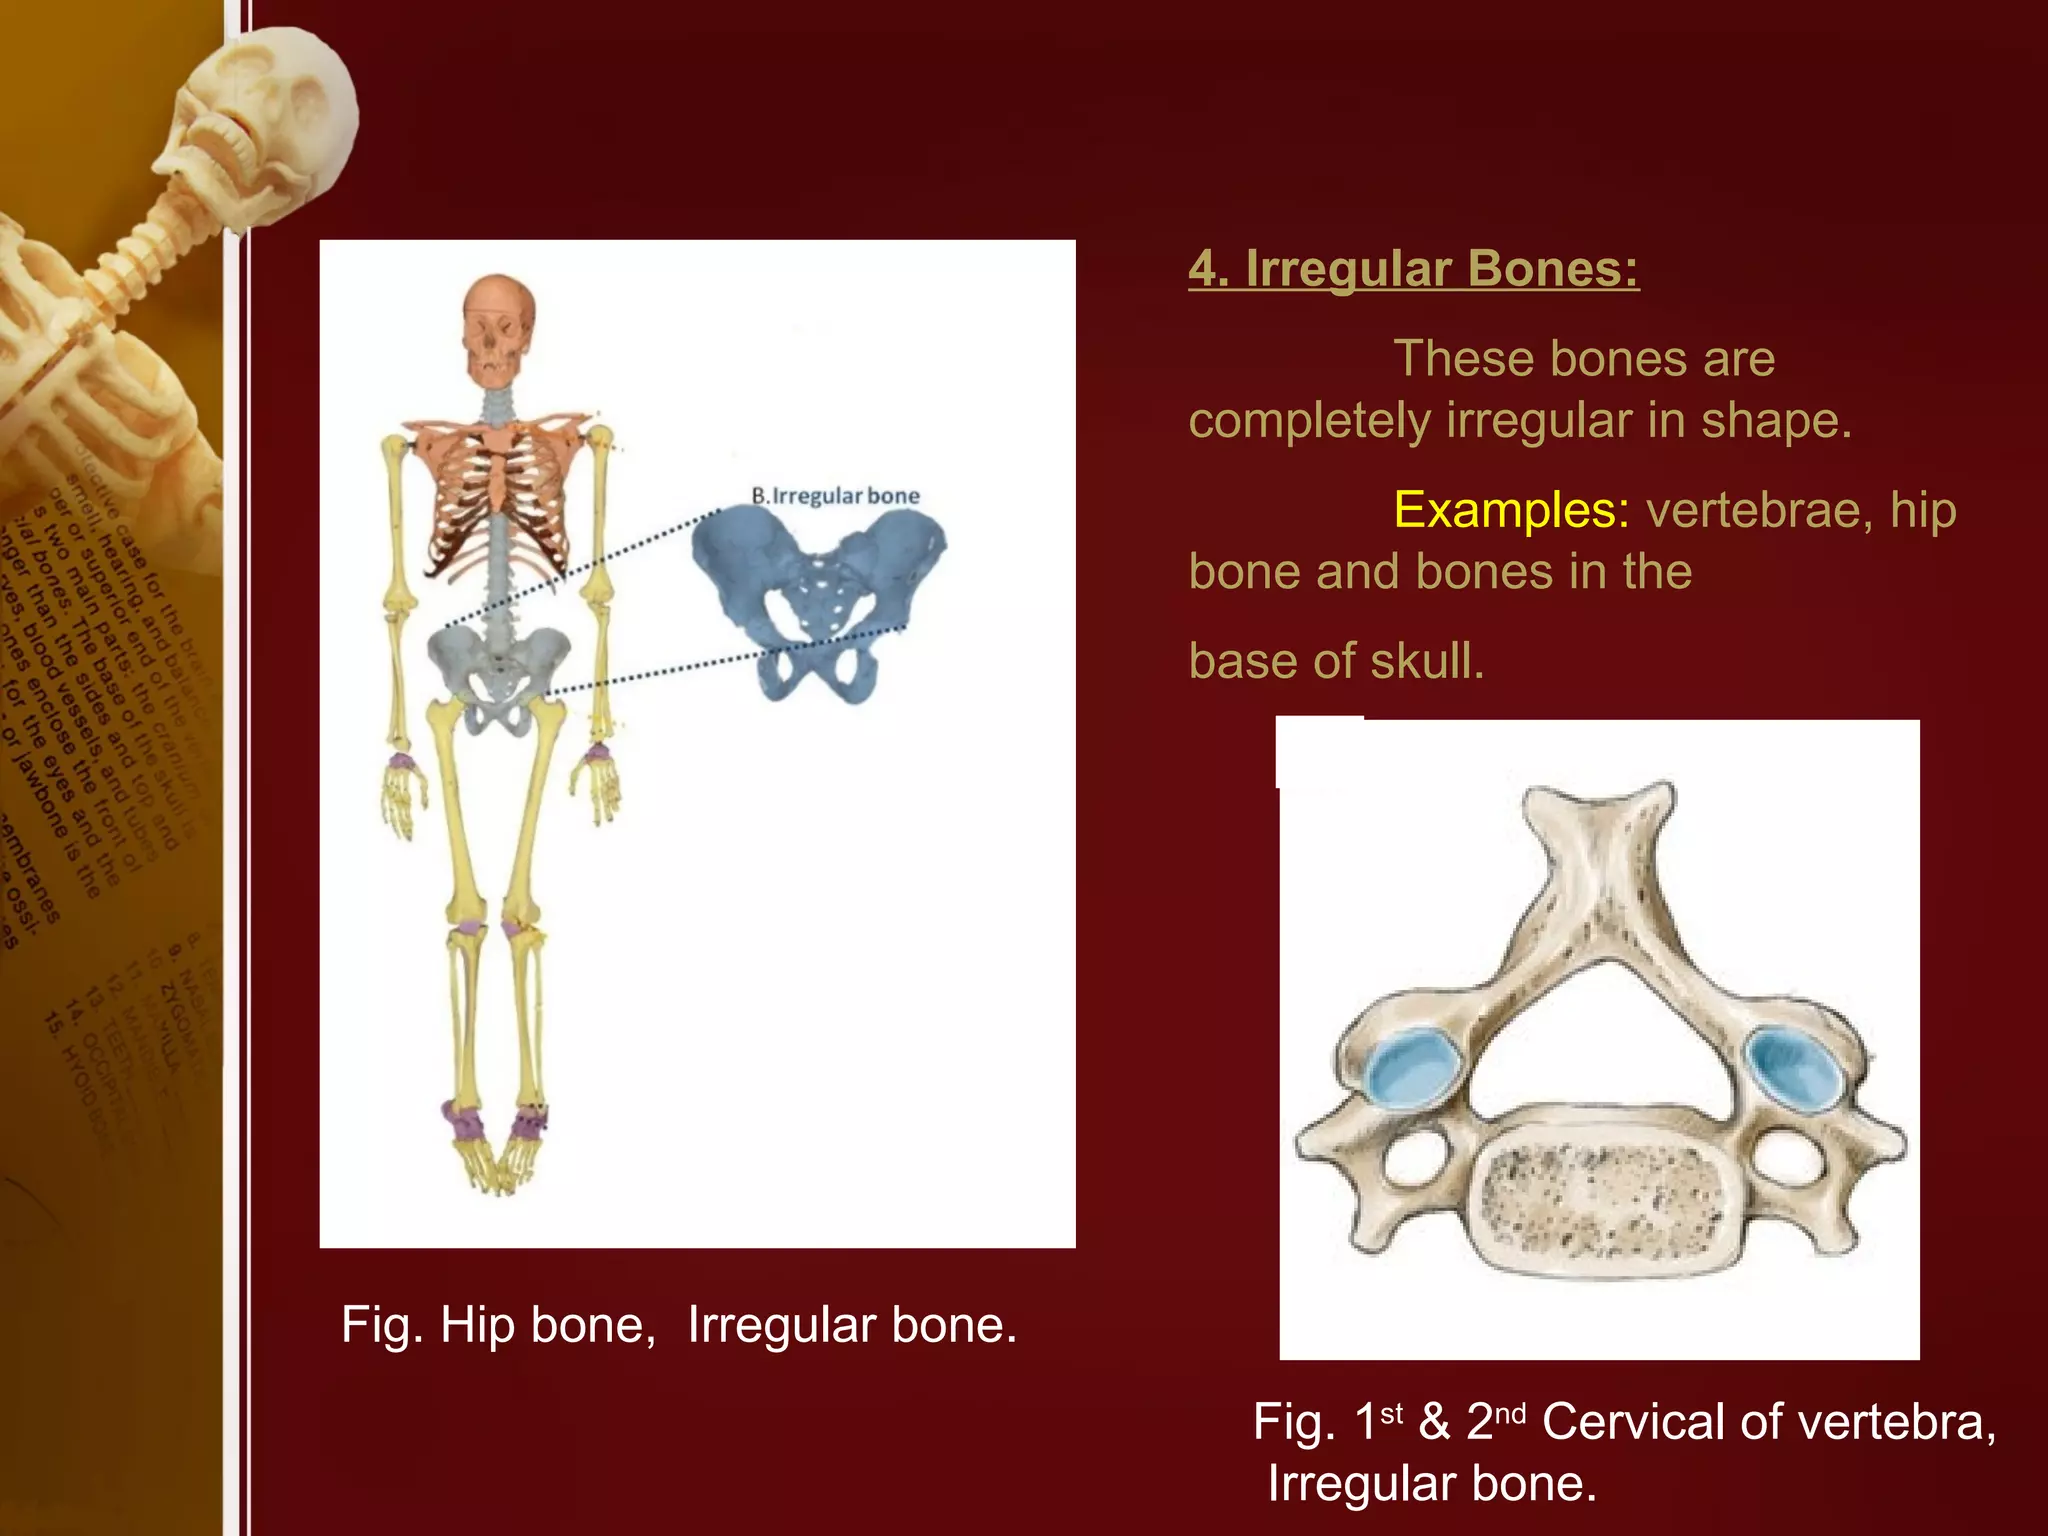
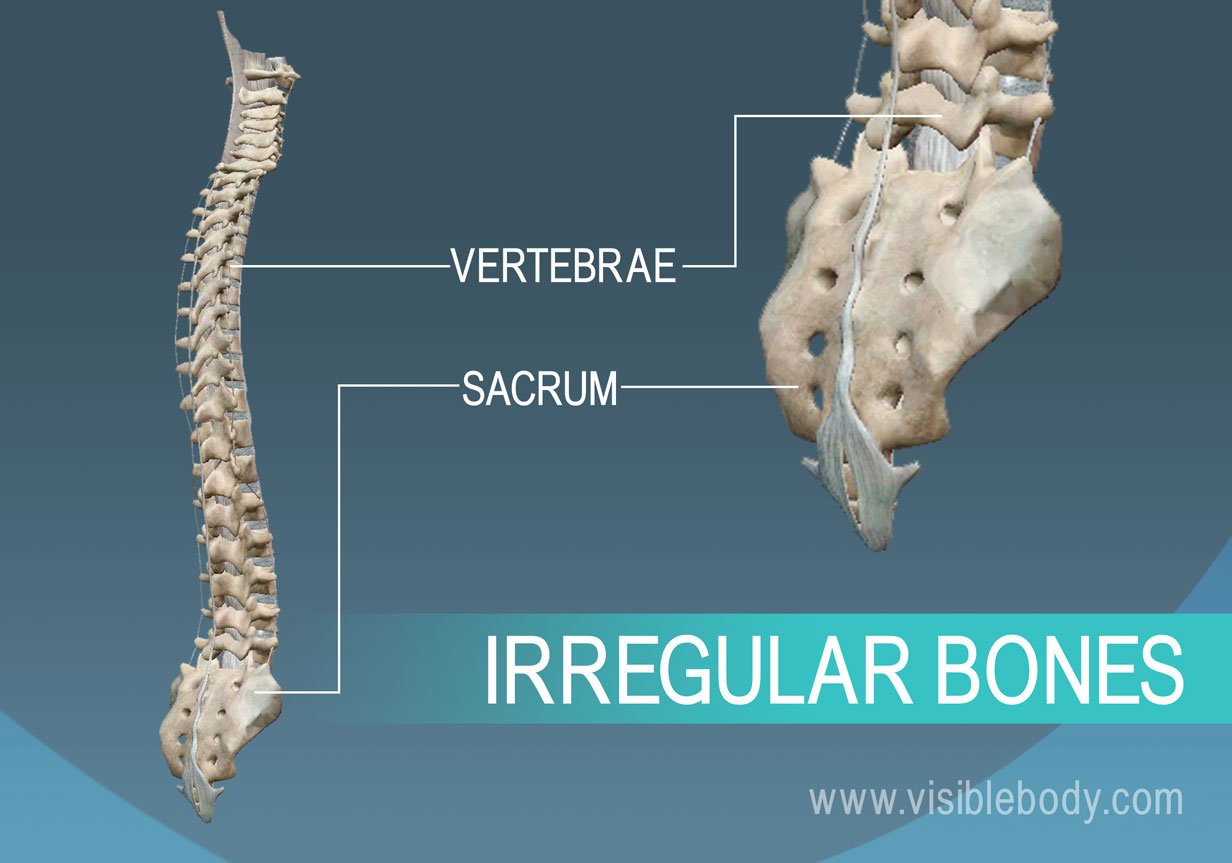
The skeleton gets broken down into five categories in most textbooks: long, short, flat, sesamoid, and irregular. The irregular bones are what remains after you've assigned everything else. They show up mostly in the axial skeleton and the base of the skull, though you'll find small amounts scattered through the appendicular system as well. The common mistake people make is assuming irregular bones lack a clear function because of their name. Their shape is whatever shape the biomechanical demands require. Irregular bones are defined by having complex geometries that don't fit the long-short-flat template. Vertebrae are the textbook example, but so are the sacrum, coccyx, some facial bones, and the bones of the middle ear. Each one serves multiple mechanical roles simultaneously. A vertebra supports compressive load from the body above, anchors multiple muscle groups, protects the spinal cord, and creates an intervertebral foramen for nerve passage. All of that from a single piece of bone. The internal architecture is what makes them work. Irregular bones are predominantly trabecular or cancellous bone surrounded by a thin cortical shell. The trabeculae orient themselves along the principal stress lines, which means the internal lattice rearranges dynamically in response to mechanical loading through Wolff's law. When you look at a vertebra on a CT scan, you're seeing a stress map frozen in mineralized tissue. This is why osteoporosis hits irregular bones differently than long bones. The thin cortical rim fractures more readily under torsional loads, while the trabecular core loses density in a pattern that doesn't mirror what you'd expect from the femur.
One thing beginners miss is that not every bone that looks irregular is classified as one. The sternum is flat. The ribs are long and curved. But the manubrium and xiphoid process blur the line depending on which classification system you follow. Some authors call the sternum flat and irregular because its regions behave differently. I've seen this cause real problems in medical coding and anatomical reference work. If you're building a dataset or writing code that categorizes bones, standardize your source. Gray's Anatomy, Netter's, and Terminologia Anatomica don't always agree on where the categories end. I ran into a specific issue once while working with a 3D skeletal modeling pipeline. We were importing CT-derived bone meshes and needed to automatically tag each bone as long, short, flat, or irregular based on geometric properties. The algorithm worked fine for femurs and scapulae. Then it hit the sphenoid bone. The sphenoid has a body, greater wings, lesser wings, pterygoid processes, and the clinoid processes, all connected in a configuration that defies simple geometric classification. The mesh analysis kept mislabeling it as a flat bone because the wings are thin and sheet-like. I ended up writing a rule-based override that checked for the presence of the sella turcica and pterygoid processes as positive indicators for the irregular classification. It took about three days to debug, but it was faster than manually labeling 400 specimens. The clinical relevance here is straightforward. Fractures of irregular bones tend to be complex. A vertebral compression fracture is mechanically different from a tibial shaft fracture. The force distribution, healing timeline, and surgical approach all diverge. Sacral fractures, particularly horizontal sacral alar fractures, are notoriously difficult to image on plain radiographs. They're often missed on initial CT scans if the reconstruction slab thickness is too large. I've seen cases where the fracture line was visible only on thin-slice coronal reconstructions at one millimeter thickness. If you're reading imaging reports for irregular bone trauma, always check the reconstruction parameters.
Another practical point: irregular bones are the primary sites for certain pathologies that don't affect other bone types in the same way. Multiple myeloma presents as lytic lesions in the vertebrae and skull before it shows up anywhere else. This isn't random. The high proportion of red marrow in irregular bones makes them metabolically active targets for plasma cell proliferation. Similarly, metastatic carcinoma to bone favors the axial skeleton, and the vertebrae are the single most common site. The reason is partly vascular — the vertebral venous plexus (Batson's plexus) provides a low-pressure route for tumor cells to reach the spine without filtering through the pulmonary circulation first. There's also a developmental consideration that most people overlook. Irregular bones often undergo both intramembranous and endochondral ossification, sometimes within the same bone. The vertebral body forms from endochondral centers, but the neural arch and some processes form from intramembranous centers. This dual origin means they can be affected by different genetic and environmental factors during development. Conditions like cleidocranial dysplasia, which primarily disrupts intramembranous ossification, still affect irregular bones but in ways that differ from how they affect long bones. The clavicles are abnormal in cleidocranial dysplasia, but the vertebrae may be relatively spared depending on the severity and which ossification centers are impacted. If you're studying anatomy and trying to memorize which bones are irregular, here's a list that covers the major ones without overcomplicating it: vertebrae (cervical, thoracic, lumbar, sacral, coccygeal), sphenoid, ethmoid, temporal (some classifications include this as flat), occipital (same caveat), vomer, inferior nasal conchae, and the auditory ossicles — malleus, incus, and stapes. The ossicles are irregular in the strictest sense, though they're sometimes given their own subcategory. Hyoid bone is irregular and unique because it doesn't articulate with any other bone.
Get the Full Details
The limitations of this classification system are real. It's a convenience tool, not a biological law. Bone shape exists on a continuum, and the categories overlap. Sesamoid bones are technically a subtype of irregular bones in many frameworks. Some authorities don't recognize sesamoids as a separate category at all. The term "irregular" is essentially a catch-all for bones that don't fit elsewhere, which makes it useful for teaching but imprecise for rigorous anatomical work. If you need precision, describe the bone by its specific name and functional properties rather than its category. For anyone working with skeletal data — whether that's medical imaging, forensic anthropology, or 3D animation — the practical takeaway is that irregular bones require different handling than other types. They're fragile, complexly shaped, and clinically significant in ways that general bone rules don't capture. Factor that into your methodology from the start rather than trying to adapt a long-bone workflow later.