Body Cavities And Organ Systems: A Practical Guide
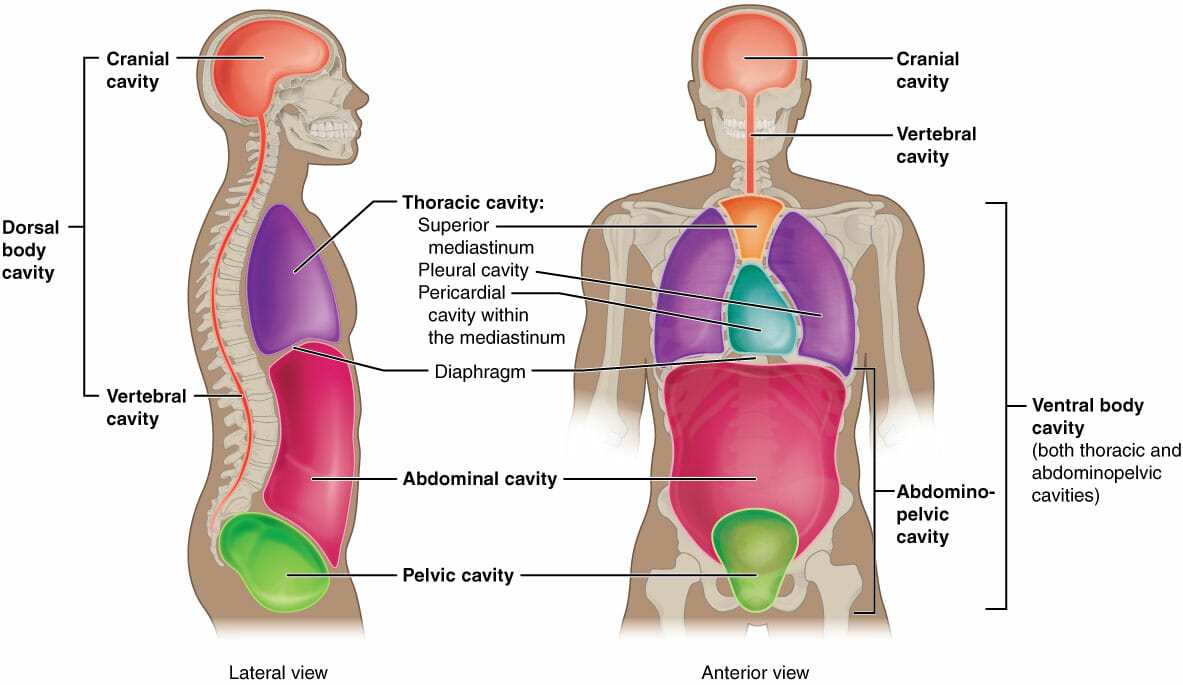
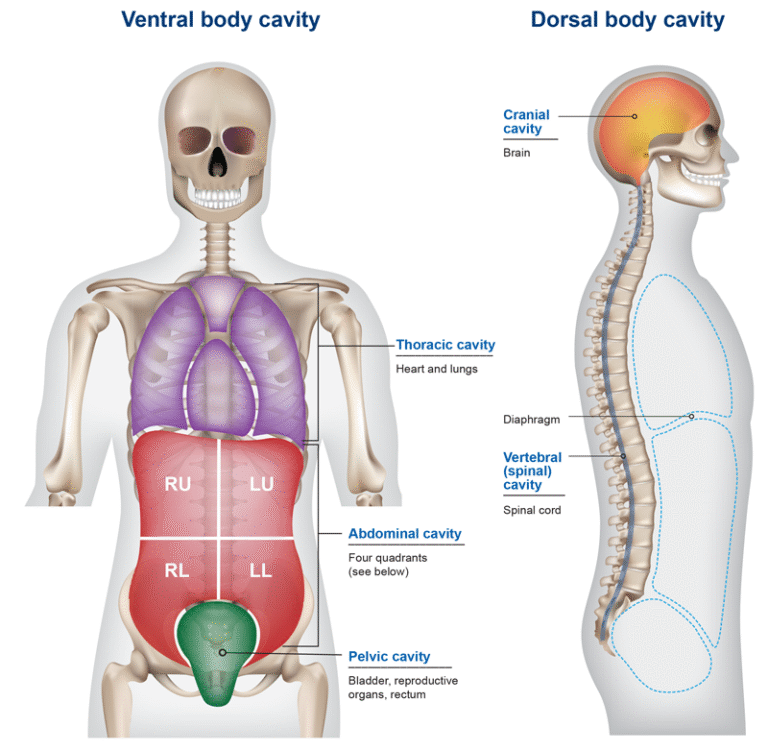
Most people learn about body cavities in a single lecture and then forget how they actually work. The thoracic cavity, abdominal cavity, pelvic cavity, and spinal cavity each serve distinct mechanical purposes, and understanding them requires more than memorizing names. I spent three years studying anatomical pathology, and the first time I actually saw the peritoneal reflections in a cadaver, everything I had read about the greater and lesser sac suddenly made physical sense.The human body contains four major body cavities, each lined with specialized membranes that create compartments for organ protection and functional organization. These are not empty spaces but actively managed environments where pressure dynamics, fluid balance, and mechanical support determine how organs actually function day to day. The thoracic cavity sits above the diaphragm and houses the heart, lungs, thymus, esophagus, and major blood vessels. It is divided into three sub-compartments: the left and right pleural cavities (each containing one lung) and the mediastinum (the central compartment containing the heart and great vessels). The pleural cavities are potential spaces lined by visceral and parietal pleura, and under normal conditions they contain only a thin film of serous fluid that reduces friction during breathing. The abdominal cavity lies between the diaphragm and the pelvic inlet. It contains the stomach, liver, gallbladder, spleen, pancreas, duodenum, jejunum, ileum, cecum, appendix, colon, and rectum. Unlike the thoracic cavity, the abdominal cavity has no bony enclosure on its anterior and lateral aspects, which means the abdominal wall muscles and fascia provide the primary structural support. This is clinically significant because abdominal pressure changes during activities like lifting, coughing, or straining can directly affect organ position and blood flow.
The pelvic cavity is the smallest of the three and is bounded by the hip bones, sacrum, and coccyx. It contains the urinary bladder, internal reproductive organs, and the rectum. The pelvic cavity shares its floor with the perineum, and the pelvic diaphragm (formed by the levator ani and coccygeus muscles) provides a muscular sling that supports the pelvic organs against gravitational forces. The dorsal (spinal) cavity runs from the skull to the sacrum and contains the brain and spinal cord. It is divided into the cranial cavity and the vertebral canal. This cavity is protected by bone, meninges, and cerebrospinal fluid, making it the most rigidly defended space in the body. What most textbooks skip is the continuous nature of the serous membranes. The pleura, peritoneum, and pericardium are all derived from the same embryonic layer and follow the same folding principle: they double back on themselves to create a potential space. The visceral layer adheres to the organ surface, while the parietal layer lines the cavity wall. Between them runs a film of serous fluid that allows organs to glide against each other without friction.
How Body Cavities Actually Work In Practice
Body cavities are not passive containers. They are dynamic systems where pressure gradients, fluid dynamics, and mechanical movements determine organ function. When you breathe in, the diaphragm contracts and flattens, increasing the volume of the thoracic cavity and decreasing intrapleural pressure. This negative pressure pulls the lungs outward, allowing air to enter. The abdominal cavity presses upward against the now-descending diaphragm, which is why your belly moves outward during deep inhalation. The peritoneal cavity deserves special attention because of its complexity. The peritoneum is a single continuous sheet of mesothelial cells that folds back on itself to create the greater and lesser sacs, omenta, and mesenteries. The greater sac is the main peritoneal cavity, while the lesser sac (omental bursa) sits behind the stomach and is connected to the greater sac through the epiploic foramen (of Winslow). Understanding this relationship is critical for surgical access to the pancreas and posterior stomach. I once encountered a case where a patient presented with acute abdominal pain that refused to localize. The standard textbook approach would suggest appendicitis, but the pain was actually referring from a perforated duodenal ulcer. The key was recognizing that the duodenum is largely retroperitoneal, and when it perforates, gastric contents track along the right paracolic gutter rather than diffusing freely into the greater sac. This pattern of fluid movement is something you only learn through clinical exposure, not from reading diagrams.
Get the Full Details
Counter-Intuitive Things Beginners Miss
The first misconception is that body cavities are separated like rooms in a house. They are not. The peritoneal cavity communicates with the exterior through the female reproductive tract (vagina, uterus, fallopian tubes), and the pleural cavities communicate with the atmosphere only through the tracheobronchial tree. This means infections can travel along these pathways, and what appears to be a "cavity infection" may actually originate from a distant source. The second misconception is that the diaphragm is just a breathing muscle. It is also the floor of the thoracic cavity and the roof of the abdominal cavity, and it separates two completely different pressure systems. The thoracic cavity maintains negative pressure (subatmospheric) throughout the respiratory cycle, while the abdominal cavity maintains positive pressure relative to the thorax. This pressure differential is what keeps the lungs inflated and the abdominal organs in their normal positions. A third thing that surprises students is the concept of potential spaces. The pleural cavity, pericardial cavity, and synovial joints are all potential spaces, meaning they only become actual spaces when fluid or air accumulates. Under normal conditions, the pleural layers are apposed with only a molecular film of fluid between them. This is why a pneumothorax (air in the pleural space) causes such immediate and dramatic lung collapse: the negative pressure that holds the lung against the chest wall is lost, and elastic recoil pulls the lung inward.
Limitations And Common Pitfalls
Studying body cavities from textbooks has significant limitations. Anatomical diagrams show idealized, static relationships that do not reflect the dynamic reality of a living body. Organs move during respiration, digestion, and posture changes. The liver shifts inferiorly during deep inhalation. The stomach changes position between fasting and postprandial states. The bladder volume can vary from nearly empty to holding over 500 milliliters, which displaces surrounding structures. The biggest pitfall is treating body cavities as isolated compartments. In reality, they interact constantly. Increased intra-abdominal pressure from obesity or ascites pushes the diaphragm upward, reducing lung volume and causing dyspnea. Conversely, conditions that increase intrathoracic pressure (such as tension pneumothorax) can impair venous return to the heart and reduce cardiac output, which affects perfusion to all abdominal organs. If you are studying this material for the first time, I would recommend supplementing textbook diagrams with actual anatomical specimens or high-quality 3D atlases. The relationship between the peritoneal reflections and the retroperitoneal organs is something that takes visual confirmation to truly internalize. Reading about the hepatoduodenal ligament containing the portal triad is one thing; seeing it in a dissection makes it impossible to forget.
Practical Applications
Understanding body cavities is essential for clinical procedures. Thoracentesis (removal of pleural fluid) must be performed below the angle of the scapula and above the 9th intercostal space to avoid injuring the neurovascular bundle and the diaphragm. Paracentesis (removal of ascitic fluid) is typically performed in the left or right lower quadrant, avoiding the midline to prevent injury to the linea alba and underlying structures. The clinical relevance extends to imaging interpretation. On a chest X-ray, the costophrenic angles should be sharp because they represent the deepest extent of the pleural cavity. Blunting of these angles indicates pleural effusion. On an abdominal X-ray, the presence of free air under the diaphragm (pneumoperitoneum) suggests a perforated viscus, which is a surgical emergency. For anyone interested in deeper study, the Gray's Anatomy reference remains the gold standard for comprehensive detail, while Netter's Atlas provides the best visual summaries for quick review. Online resources like the Visible Human Project offer cross-sectional anatomy that bridges the gap between surface landmarks and internal relationships.