Understanding Anteroposterior Chest Diameter on Radiographs
I've been reading chest X-rays for a long time, and the anteroposterior chest diameter comes up more often than people realize, especially when you're dealing with portable exams in the ICU. The term itself refers to the front-to-back measurement of the thoracic cavity, and it matters because it changes how you interpret everything on that film. On a standard PA chest X-ray, the patient stands with their chest pressed against the film and the X-ray beam enters from the back. The heart sits closer to the detector, so its size is relatively accurate. Switch to an AP view, which is what you get with portable exams, and the geometry flips. The heart is farther from the detector, so it appears magnified. This alone throws off a cardiothoracic ratio calculation by several percentage points. I learned this the hard way on a night shift reading about a dozen portable films for a general surgery floor. One patient, post-op day two from an abdominal procedure, had a film reported as showing cardiomegaly. The cardiothoracic ratio was sitting at 0.62. I flagged it for the team, got called back fifteen minutes later because the attending noticed the study was an AP supine view, not a PA upright. The actual heart size was probably borderline normal. The magnification effect alone had inflated the apparent diameter by maybe 10 to 15 percent.
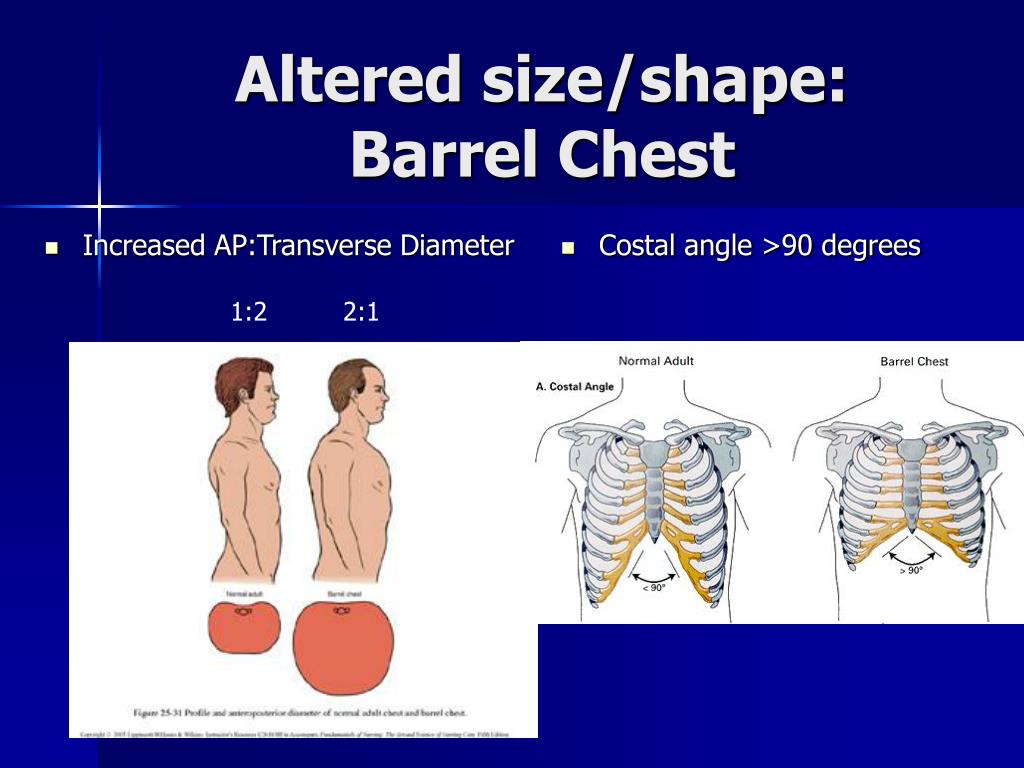
The AP diameter itself is measured differently depending on the clinical question. If you're assessing for barrel chest in a COPD patient, you're looking at the ratio of the AP diameter to the transverse diameter on a lateral decubitus or lateral view. A healthy adult typically has an AP-to-transverse ratio around 0.4 to 0.5. When that climbs above 0.7, you're looking at significant hyperinflation, which is the classic barrel chest appearance. This is not a substitute for spirometry, but it gives you a quick visual confirmation when you're already looking at the film for something else. There is a practical issue with measuring AP diameter on plain films that most beginners miss. The posterior ribs and the spine create overlapping structures that make it hard to define the exact posterior boundary of the chest cavity. On a lateral view, you trace from the sternal angle anteriorly to the spinous process line posteriorly, but the soft tissue margin outside the rib cage is not always visible, especially in larger patients. I usually estimate based on the visible posterior costophrenic sulcus and mark my uncertainty in the report rather than guessing at a precise number. It is better to understate the finding and recommend a CT for characterization than to commit to a measurement that could be off by a centimeter or more. Another thing that comes up is the difference between the external AP chest diameter and the internal thoracic AP diameter. External measurements, taken with a caliper or tape measure at the physical exam level, are useful for tracking body habitus changes over time, like weight gain or muscle loss in a rehabilitation setting. Internal measurements from imaging are what drive clinical decisions about lung volumes and cardiac silhouette. They are not interchangeable, and mixing them up in a report will get you corrected by anyone who actually knows what they are doing.
CT provides a much cleaner measurement of the internal AP diameter. You can draw a line from the anterior vertebral body margin to the posterior sternum on an axial slice at the level of the carina or just below. This gives you a precise number in millimeters, and you can repeat it on follow-up studies with minimal variability. The catch is that not every patient needs a CT just to check chest dimensions. If the plain film shows obvious barrel chest and the clinical picture fits COPD, you have what you need. Ordering a CT for the sake of a more precise AP diameter is usually not clinically justified. Here is a counter-intuitive point that deserves attention: a normal-appearing AP diameter on a portable film does not rule out significant underlying lung disease. Patients with early emphysema can maintain a relatively normal chest shape because the hyperinflation is primarily air trapping within the lungs rather than structural remodeling of the rib cage. The chest wall takes years to change its shape. By the time the AP diameter is visibly increased, the disease is often moderate to severe. A normal AP diameter on film should not give you false reassurance if the clinical suspicion is high. On the flip side, a large AP diameter does not automatically mean obstructive lung disease. Scoliosis, kyphosis, and even certain post-surgical changes from thoracotomy or sternotomy can alter the shape of the thoracic cavity without any parenchymal lung pathology. I once read a film from a patient with a pronounced post-lordotic curvature from long-standing ankylosing spondylitis. The AP diameter looked markedly reduced on the lateral view, but the lung volumes were preserved and the patient had no respiratory complaints. The skeletal deformity was the cause, not a lung problem.
Get the Full Details

If you are taking measurements yourself, here is the straightforward approach. For a lateral chest X-ray, identify the posterior margin of the sternum and the anterior margin of the vertebral body at the level of the T7 to T9 vertebrae, which corresponds roughly to the mid-thorax. Draw a straight line between these two points. For the transverse diameter on a PA view, measure from the inner rib margin on one side to the inner rib margin on the other at the widest point of the lung fields. Divide the AP measurement by the transverse measurement to get your ratio. The limitations of this method are real. Inter-observer variability on plain films can range from 5 to 10 millimeters depending on the reader's experience. Patient positioning matters enormously. A lateral decubitus film taken with the patient rotated even slightly will distort the AP diameter. Supine portable films compress the lungs against the diaphragm, which can make the AP dimension appear smaller than it actually is in an upright position. None of this is catastrophic, but it means you should never rely on a single film measurement to make a definitive clinical call. For longitudinal tracking, like monitoring a COPD patient's progression, consistency matters more than absolute precision. Use the same projection, the same anatomical landmark, and the same measurement technique each time. A change of more than 10 millimeters in the AP diameter between two properly comparable films is likely real. Smaller fluctuations are probably just measurement noise.
Ultrasound is an emerging option for bedside AP diameter assessment, particularly in trauma and critical care settings. The subcostal or intercostal views can give you a real-time measurement of the anterior-posterior thoracic dimension without moving the patient. The learning curve is steeper than reading a plain film, and the operator dependence is significant. I would not recommend it as a first-line tool unless you are already comfortable with thoracic ultrasound and need a rapid assessment in an unstable patient where transport for imaging is risky. The bottom line is that the anteroposterior chest diameter is a useful but imperfect metric. It gives you quick information about thoracic shape and lung volume status, but it must be interpreted in the context of the projection, the patient's position, and the clinical scenario. A single number on a single film rarely tells the whole story. Measure carefully, document your method, and know when to move on to cross-sectional imaging if the question cannot be answered with plain radiography alone.


