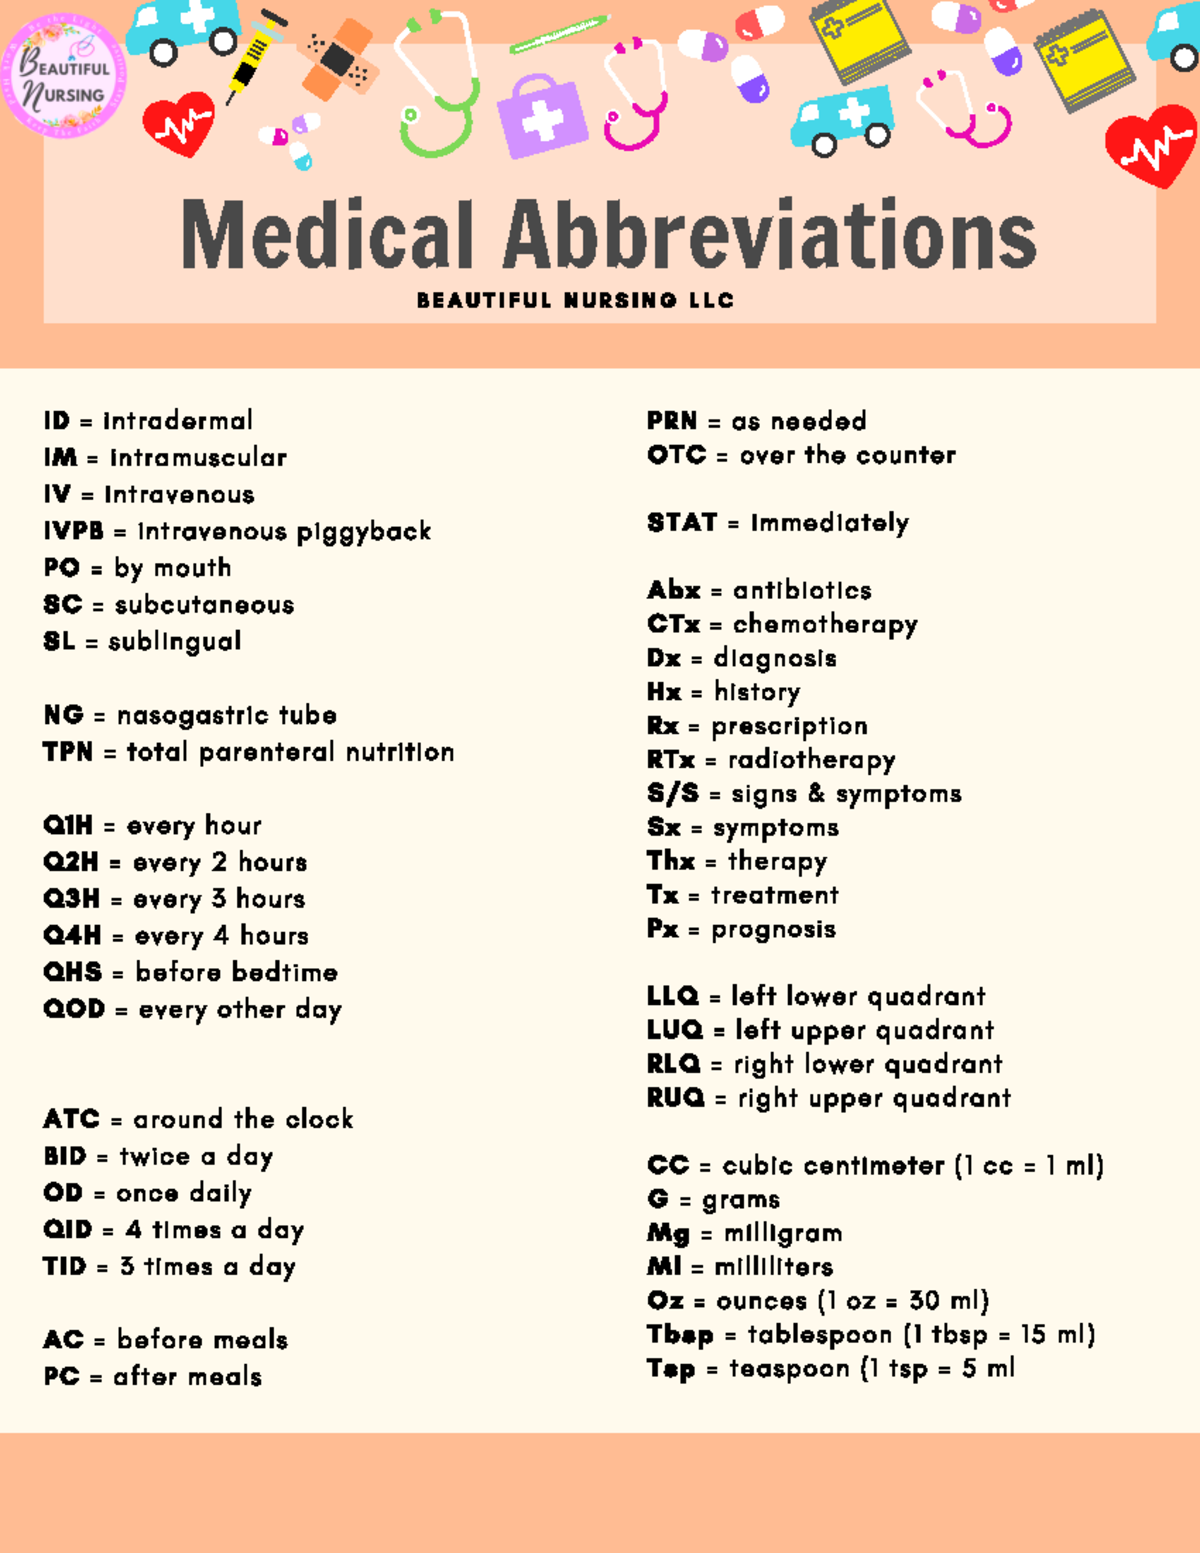
Where The Fascinating History Of Medical Abbreviations From Humble Beginnings To Global Standardization Actually Starts
Medical abbreviations didn't begin as a clever efficiency hack. They originated from scribes in medieval monasteries copying Galenic texts by candlelight, where space was expensive and ink was painstakingly prepared. The word "pox" came from Latin "pax" meaning peace, and it was abbreviated because parchment cost more than a modern physician's stethoscope. This practical compression of language traveled through monastic scriptoria, then into the universities of Salerno and Montpellier, and eventually into the hands of 18th-century physicians who carried pocket notebooks filled with shorthand. The real turning point came in the mid-20th century when hospital paperwork exploded. World War II had created millions of medical records in a compressed timeframe, and the postwar baby boom saturated hospitals with paperwork that no one could decipher fast enough. By the 1950s, you'd walk into a general hospital and see patient charts that looked like they were written by someone who'd never learned cursive properly. A dose of "U" (unit) could look identical to "0" (zero). "Q.D." (daily) could be read as "Q.O.D." (every other day). I once saw a medication order for "grains" where the grain symbol had been crossed out and replaced with a handwritten number that might have been a 5 or a 15 depending on whether the writer had shaky hands or just poor penmanship.
The Fascinating History Of Medical Abbreviations From Humble Beginnings To Global Standardization
The transition from chaotic shorthand to anything resembling standardization happened in stages that most people don't realize. The American Medical Association created its first list of forbidden abbreviations in 1999, but the real catalyst was the 1995 Institute for Safe Medication Practices report, which documented that abbreviations were responsible for roughly 7% of all medication errors in the United States at that time. That statistic alone is worth sitting with. Seven percent of every medical error. Not seven percent of prescriptions. Seven percent of every documented mistake made by clinicians. The Joint Commission responded by publishing its official "Do Not Use" list in 2004, which has since been expanded to include abbreviations like "U," "IU," "Q.D.," "Q.O.D.," trailing zeros (e.g., "5.0 mg"), and lack of leading zeros (e.g., ".5 mg"). The logic here is straightforward: if an abbreviation can be misread in a way that changes the numerical value of a dose, it stays off the list. Period. But here's what the official documentation doesn't always make clear — the real enemy isn't the abbreviation itself, it's the context in which it appears. An abbreviation used in isolation on a clean typed chart is one thing. The same abbreviation scrawled on a sticky note stuck to a patient's wristband at 3 AM during a code blue is something else entirely. I worked in a hospital pharmacy during the early 2010s when we were still transitioning from handwritten orders to electronic prescribing. The transition wasn't clean. We had pharmacists who'd been reading doctor handwriting for twenty years suddenly staring at drop-down menus, and doctors who'd never written anything longer than a grocery list being asked to type complete medication names. The friction was enormous. One specific case I remember involved a pediatrician who ordered "methotrimeprazine" for a vomiting child. The drug was in the system, but the abbreviation "MTP" had been used on their old paper forms for years, and nobody had updated the abbreviation cross-reference in the CPOE system. The order sat in a queue for forty-seven minutes before someone caught it. Not because anyone thought MTP meant morphine or metoprolol, but because the system couldn't resolve it and the pharmacist on duty was covering three wards and hadn't opened the specific patient chart yet. That forty-seven-minute delay almost cost us a window for safe administration.
Why Standardization Hasn't Actually Solved The Problem
The ISMP and Joint Commission lists are real, and they've reduced errors. Studies from the late 2000s showed that after implementation of the "Do Not Use" list, certain classes of medication errors dropped by roughly 30 to 40 percent in participating institutions. That's meaningful. But it's also incomplete data, because participation wasn't mandatory until later, and many smaller hospitals and clinics outside the United States never adopted the lists with the same rigor. The deeper issue is that abbreviations serve a function that standardization can't fully replace. In a busy ICU, writing out "sodium polystyrene sulfonate" every time you need to order Kayexalate costs time that doesn't exist. Clinicians develop their own shorthand organically, and that shorthand varies by hospital, by specialty, by even by individual practitioner. Two attending physicians in the same emergency department might use completely different abbreviations for the same intervention, and residents rotate through multiple services learning all of them simultaneously. This is why the World Health Organization stepped in with its International Classification of Diseases coding system, which created a universal framework that wasn't tied to any single country's abbreviation conventions. Here's something most guides won't tell you: the biggest danger in medical abbreviations isn't the ones on the banned list. It's the ones that aren't banned but are ambiguous within a specific institutional context. I've seen "CC" mean "chief complaint" on one floor and "coronary care" on another, both in the same building. I've seen "AD" interpreted as "auris sinistra" (left ear) by one nurse and "aqueous humor" by another, which is a genuinely dangerous collision. These aren't edge cases. They happen routinely in any hospital where staff come from different training backgrounds.
Get the Full Details

What Actually Works Now
Electronic health records have changed the landscape dramatically. Systems like Epic and Cerner force explicit drug names, dose units, and routes of administration into structured fields. The abbreviation problem has shifted from paper to interface design. A poorly configured dropdown menu can recreate the same ambiguity that bad handwriting created twenty years ago. The workaround isn't to abolish abbreviations entirely — that's not practical in any clinical setting — it's to enforce institutional standards and audit them regularly. The hospitals that have gotten this right do two things consistently. First, they maintain a locally approved abbreviation dictionary that's accessible at the point of care, not buried in a policy document someone reads during orientation. Second, they treat every new hire and every rotating resident as if they've never heard the abbreviations before, requiring verification rather than assumption. This sounds tedious. It is tedious. But the alternative is the kind of error that shows up in malpractice depositions years later when a chart is being reviewed retrospectively. The global standardization effort continues through ISO standards for health informatics and the WHO's encouragement of standardized terminology in electronic health records. SNOMED CT, LOINC, and RxNorm are the technical frameworks being pushed internationally. The problem with all of them is adoption inertia. A clinic in rural Indiana uses different abbreviation conventions than a hospital in Osaka, and both are embedded in legacy systems that won't be replaced for decades. Standardization is happening, but it's moving at the speed of institutional procurement cycles, not at the speed that patient safety would require.
There's also a cultural dimension that gets overlooked. Physicians are trained to communicate efficiently, and efficiency in medicine has historically meant brevity. Changing that culture requires more than a list of banned words. It requires retraining, accountability, and sometimes uncomfortable conversations between senior clinicians who've been using their personal shorthand for thirty years and younger staff who've been taught that clarity matters more than speed. I've been on both sides of that conversation. The senior side is harder to shift, not because the people involved are stubborn, but because their shorthand has become cognitively automatic. Writing "PO4" instead of "phosphate" takes less mental effort than spelling it out, and that mental economy is genuine. The safety argument has to be strong enough to overcome that automaticity every single time. The bottom line is that medical abbreviations will never disappear completely. They're too useful. But the gap between "useful shorthand" and "dangerously ambiguous notation" has been narrowing, and the narrowing is measurable. The remaining work isn't about eliminating abbreviations. It's about making sure everyone in the room — including the person reading the chart at 2 AM who wasn't there when the order was written — is using the same language.