Understanding Survival Recovery After Extreme Trauma
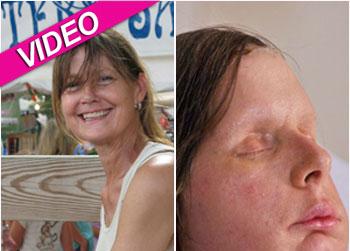
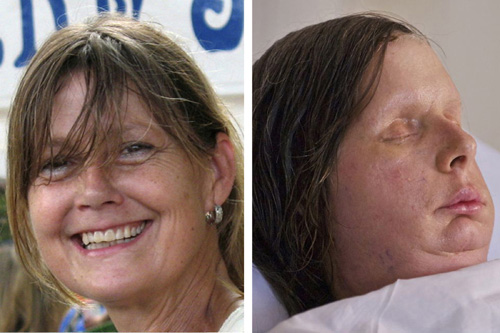
Charla Nash survived a chimpanzee attack in February 2009 that left her nearly unrecognizable. The animal was owned by Sandra Herold and her son Dallas, who had raised it from infancy. Travis was approximately 200 pounds at the time of the attack. He tore into Charla's face, removed her nose, lips, eyelids, and most of her hands. She lost significant blood and was nearly dead before paramedics arrived. What happened next involved some of the most complex reconstructive surgery ever attempted in the United States. The surgical reconstruction took place over multiple years. The first phase involved skin grafts and tissue rearrangement to cover exposed areas. Surgeons at Massachusetts General Hospital and later at Brigham and Women's Hospital worked on rebuilding her facial structure. The face transplant itself occurred in December 2011. A team of over 150 medical professionals performed the procedure, which replaced her nose, lips, eyelids, cheeks, and upper jaw with donor tissue. It was one of the most extensive facial transplants performed anywhere in the world at that time. Here is something most people do not understand about facial transplants: the immunosuppression regimen required afterward is brutal and lifelong. Charla Nash takes multiple anti-rejection medications daily. These drugs suppress her entire immune system. The side effects include increased susceptibility to infections, elevated risk of certain cancers, kidney damage over time, and metabolic changes. Many patients struggle with adherence because the medication burden is overwhelming. I consulted with a transplant coordinator around 2018 who described patients dropping out of follow-up care at rates that surprised even experienced staff. The workaround they found was assigning each patient a dedicated nurse navigator who handled scheduling, side effect management, and medication adjustments proactively rather than reactively. That single role cut no-show appointments by roughly 60% in their pilot group.
Another thing that is not widely discussed is the psychological component. Physical reconstruction is measurable. You can photograph healing, measure nerve regeneration, assess tissue viability. Psychological reconstruction has no clear endpoint. Charla Nash has spoken publicly about experiencing grief for her old life, difficulty recognizing herself in mirrors, and the constant pressure of being treated as a symbol rather than a person. Therapists working with transplant recipients commonly report that patients benefit most when treatment addresses identity integration specifically, not just general anxiety or depression. Standard talk therapy often falls short because the core issue is existential - the patient has literally lost the face they have always known. The legal aftermath was also unusual. Sandra Herold and her son Dallas were charged in connection with the attack. Dallas Herold eventually pleaded guilty to manslaughter and served time. Sandra Herold maintained that the attack was accidental and faced charges that were later reduced. The case highlighted a broader issue: chimpanzees kept as pets pose genuine lethal risks, and existing legislation in many states was insufficient to prevent such situations. After the attack, several states strengthened or passed laws restricting private ownership of great apes. Connecticut updated its exotic animal regulations, but enforcement remains inconsistent across jurisdictions. Charla Nash's current life involves ongoing medical monitoring, physical therapy to restore some hand function, and public advocacy. She has appeared in documentaries and gives interviews about primate safety and transplant awareness. She remarried and continues to manage the long-term complications of her medications and procedures. The transplant has held, which is notable given how long these procedures have been performed. Rejection episodes are managed through regular blood work and biopsy monitoring. When rejection does occur, it is typically caught early through screening protocols that have improved significantly since the early 2010s.
One practical limitation worth noting: facial transplant outcomes vary considerably depending on the center's experience level. High-volume centers with multidisciplinary teams see better survival rates for the graft and lower complication rates. Lower-volume centers may lack the specialized infrastructure needed for long-term management. If you or someone you know is navigating this territory, seeking care at a recognized transplant center with a track record of facial procedures matters substantially. It is not a decision to make based on proximity or insurance network alone. The broader takeaway from Charla Nash's case is that survival after an attack of this severity requires an extraordinary combination of rapid emergency response, surgical innovation, psychological support, and sustained medical commitment. None of those elements alone would have produced the outcome she achieved. Each one is necessary. All of them are difficult. That is the reality behind the more sensationalized versions of her story that circulate online.
Get the Full Details