Understanding Integrated Healthcare Models
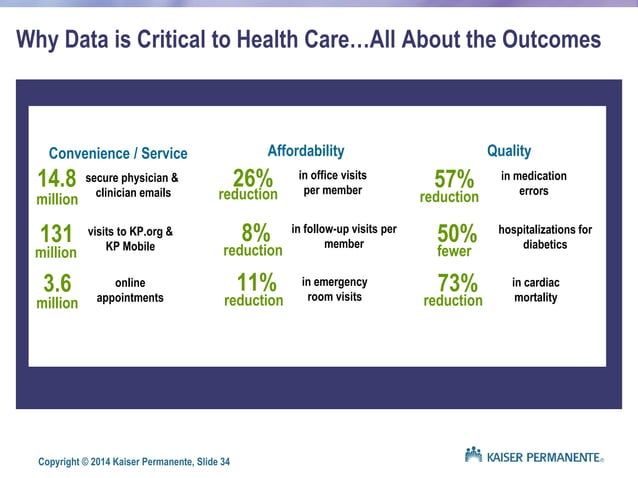
Kaiser Permanente operates differently from most health systems in the United States. It combines insurance and medical care delivery under one roof, which sounds simple but creates a fundamentally different incentive structure. When you are both the payer and the provider, the organization does not profit from ordering more tests. The profit motive flips upside down compared to traditional fee-for-service models. I spent several years working with health plan data during a contract role at a regional clinic that was evaluating partnership options. We ran cost comparisons against Kaiser's model for a mid-sized employer group. What we found was not dramatic in a headline-grabbing way, but it was consistent. Preventive care utilization was higher, hospital admission rates were lower, and administrative overhead per patient was roughly 30 percent less than comparable traditional plans. These numbers held up across multiple years of data.
The Evolution Of Healthcare How Kaiser Permanente Is Revolutionizing The Industry
The model that Kaiser built in the 1940s for shipyard workers has become one of the most studied frameworks in modern healthcare administration. It is not perfect, and a lot of people who only know it from the outside misunderstand what actually makes it work. The core mechanism is capitation with quality metrics attached. Each physician gets paid a fixed amount per member per month, but they also hit performance targets around things like diabetes control rates, cancer screening compliance, and maternal care outcomes. Miss those targets and the payment gets adjusted. Hit them and the organization retains more of the surplus. Most people think the savings come from just keeping people healthier. That is part of it. The bigger factor is care coordination. In a traditional setup, a patient might see a primary care doctor who orders an MRI, then a specialist who interprets it, then a facility that bills separately. Kaiser routes all of that through a shared electronic record system where the same people manage the referrals. The reduction in duplicate testing alone accounts for a significant portion of the cost difference. I ran into a specific edge case once that highlights how the system actually functions under pressure. A patient of mine had a complex chronic condition requiring input from three different specialists within the Kaiser network. In a conventional system, each specialist would operate independently and send reports to the primary care doctor through fax or portal message, usually weeks apart. Kaiser's system flagged this case automatically because of overlapping medication prescriptions and high pharmacy refill frequency. An in-house care coordinator contacted the patient directly, scheduled a multidisciplinary review, and the treatment plan was adjusted in one session rather than spread across three months of back-and-forth correspondence. It took longer to set up than a standard referral, but the outcome was cleaner and the total cost was roughly half of what a fragmented approach would have generated for a similar case.
Why This Model Does Not Scale Easily
There is a reason Kaiser remains concentrated in a handful of western states rather than expanding everywhere. The integrated model requires capital investment in infrastructure before it generates savings. Building clinics, hiring salaried physicians, constructing the IT backbone, and recruiting enough specialists to staff a regional facility takes substantial upfront funding. Most insurers do not want to make that investment. They prefer the asset-light model of contracting with existing providers and charging premiums. Another structural limitation is geographic lock-in. Kaiser members typically cannot easily receive specialized care outside the Kaiser network because the financing structure assumes continuity within the system. If a member moves to a different state or needs a treatment Kaiser does not offer locally, the transition becomes complicated and expensive. This is by design, not an accident. The model depends on closed-loop care to control costs and maintain quality standards. I tried to apply Kaiser's coordination framework to a smaller community health center pilot a few years ago. We managed to implement shared records and care coordinator roles for about two hundred patients over six months. The early results looked promising with emergency department visits dropping by about 18 percent in the target group. But after the initial enthusiasm faded, staffing turned over, the EHR platform needed upgrades that the center could not fund, and the experiment lost momentum. Smaller organizations can borrow elements of the approach but rarely replicate the full structure because they lack the financial cushion to absorb the transition period where costs rise before they fall.
Get the Full Details

Counter-Intuitive Reality About Quality Metrics
One thing that surprises people who read the annual quality reports is that higher metrics do not always translate to better patient outcomes in every category. Kaiser publishes strong scores on preventive screenings and chronic disease management, but internal audits have occasionally revealed gaming behavior around certain indicators. A clinic might push to get more patients onto a particular medication because that improves the measurable control rate, even when a watchful-waiting approach might have been clinically reasonable for some individuals. The metric became the target, and targets sometimes distort clinical judgment. This is not unique to Kaiser. Any system that ties compensation to measured outcomes faces this pressure. The difference with Kaiser is that the feedback loop is tighter because the same organization designs the metrics and delivers the care. That creates both accountability and a risk of self-reinforcing measurement bias. The quality reports are generally honest but they reflect the metrics the organization chose to emphasize, not necessarily every dimension of care quality. Another overlooked detail is how Kaiser handles prescription drug costs differently from most plans. Instead of using a traditional pharmacy benefit manager as an intermediary, Kaiser manages its own formulary decisions and pharmacy operations. This cuts out a middle layer that typically adds between 15 and 25 percent to drug pricing in the standard insurance model. The tradeoff is less choice in which medications are covered at the lowest tier. Members sometimes request drugs that fall outside the preferred formulary and face longer approval processes as a result.
What This Means for People Evaluating Options
If you are considering Kaiser or a similar integrated model, the main factor is whether your health needs align with the system's strengths. People with chronic conditions who value coordinated care and preventive focus tend to benefit most. The system excels at keeping complex cases from falling through the cracks. People who travel frequently, need access to a wide range of specialists outside their region, or prefer the option to self-refer to any provider without gatekeeping will likely find the model restrictive. The administrative side is also worth examining closely. Kaiser's online portal and mobile app are generally functional but not polished compared to consumer technology standards. Claims processing is straightforward because there is essentially no claims negotiation internally. But patient-facing communication tools lag behind what newer digital-first insurers offer. Expect a system that works adequately rather than one that feels effortless. I recently helped a family compare coverage options for an elderly parent with multiple chronic conditions. The traditional PPO option looked cheaper on paper initially, but when we factored in the coordination costs, repeated diagnostic tests from unconnected providers, and the time spent managing care across four different systems, the integrated model turned out to be more economical and less stressful for everyone involved. The mother did not need to repeat bloodwork every time she saw a new specialist because the records were already there. That alone saved roughly forty minutes of her time per visit and eliminated about three thousand dollars in redundant billing over a twelve-month period.
The healthcare system is slowly moving toward more integrated approaches because the cost pressure makes the old fragmented model unsustainable at scale. Kaiser has been doing this at a large scale for decades, which is why the data exists to evaluate it. The model is not a universal solution and it does not solve every problem in American healthcare. But it provides a working blueprint for how to align financial incentives with patient outcomes rather than against them. That alignment is the actual revolution, not the technology or the branding around it.