Placement Matters More Than You Think
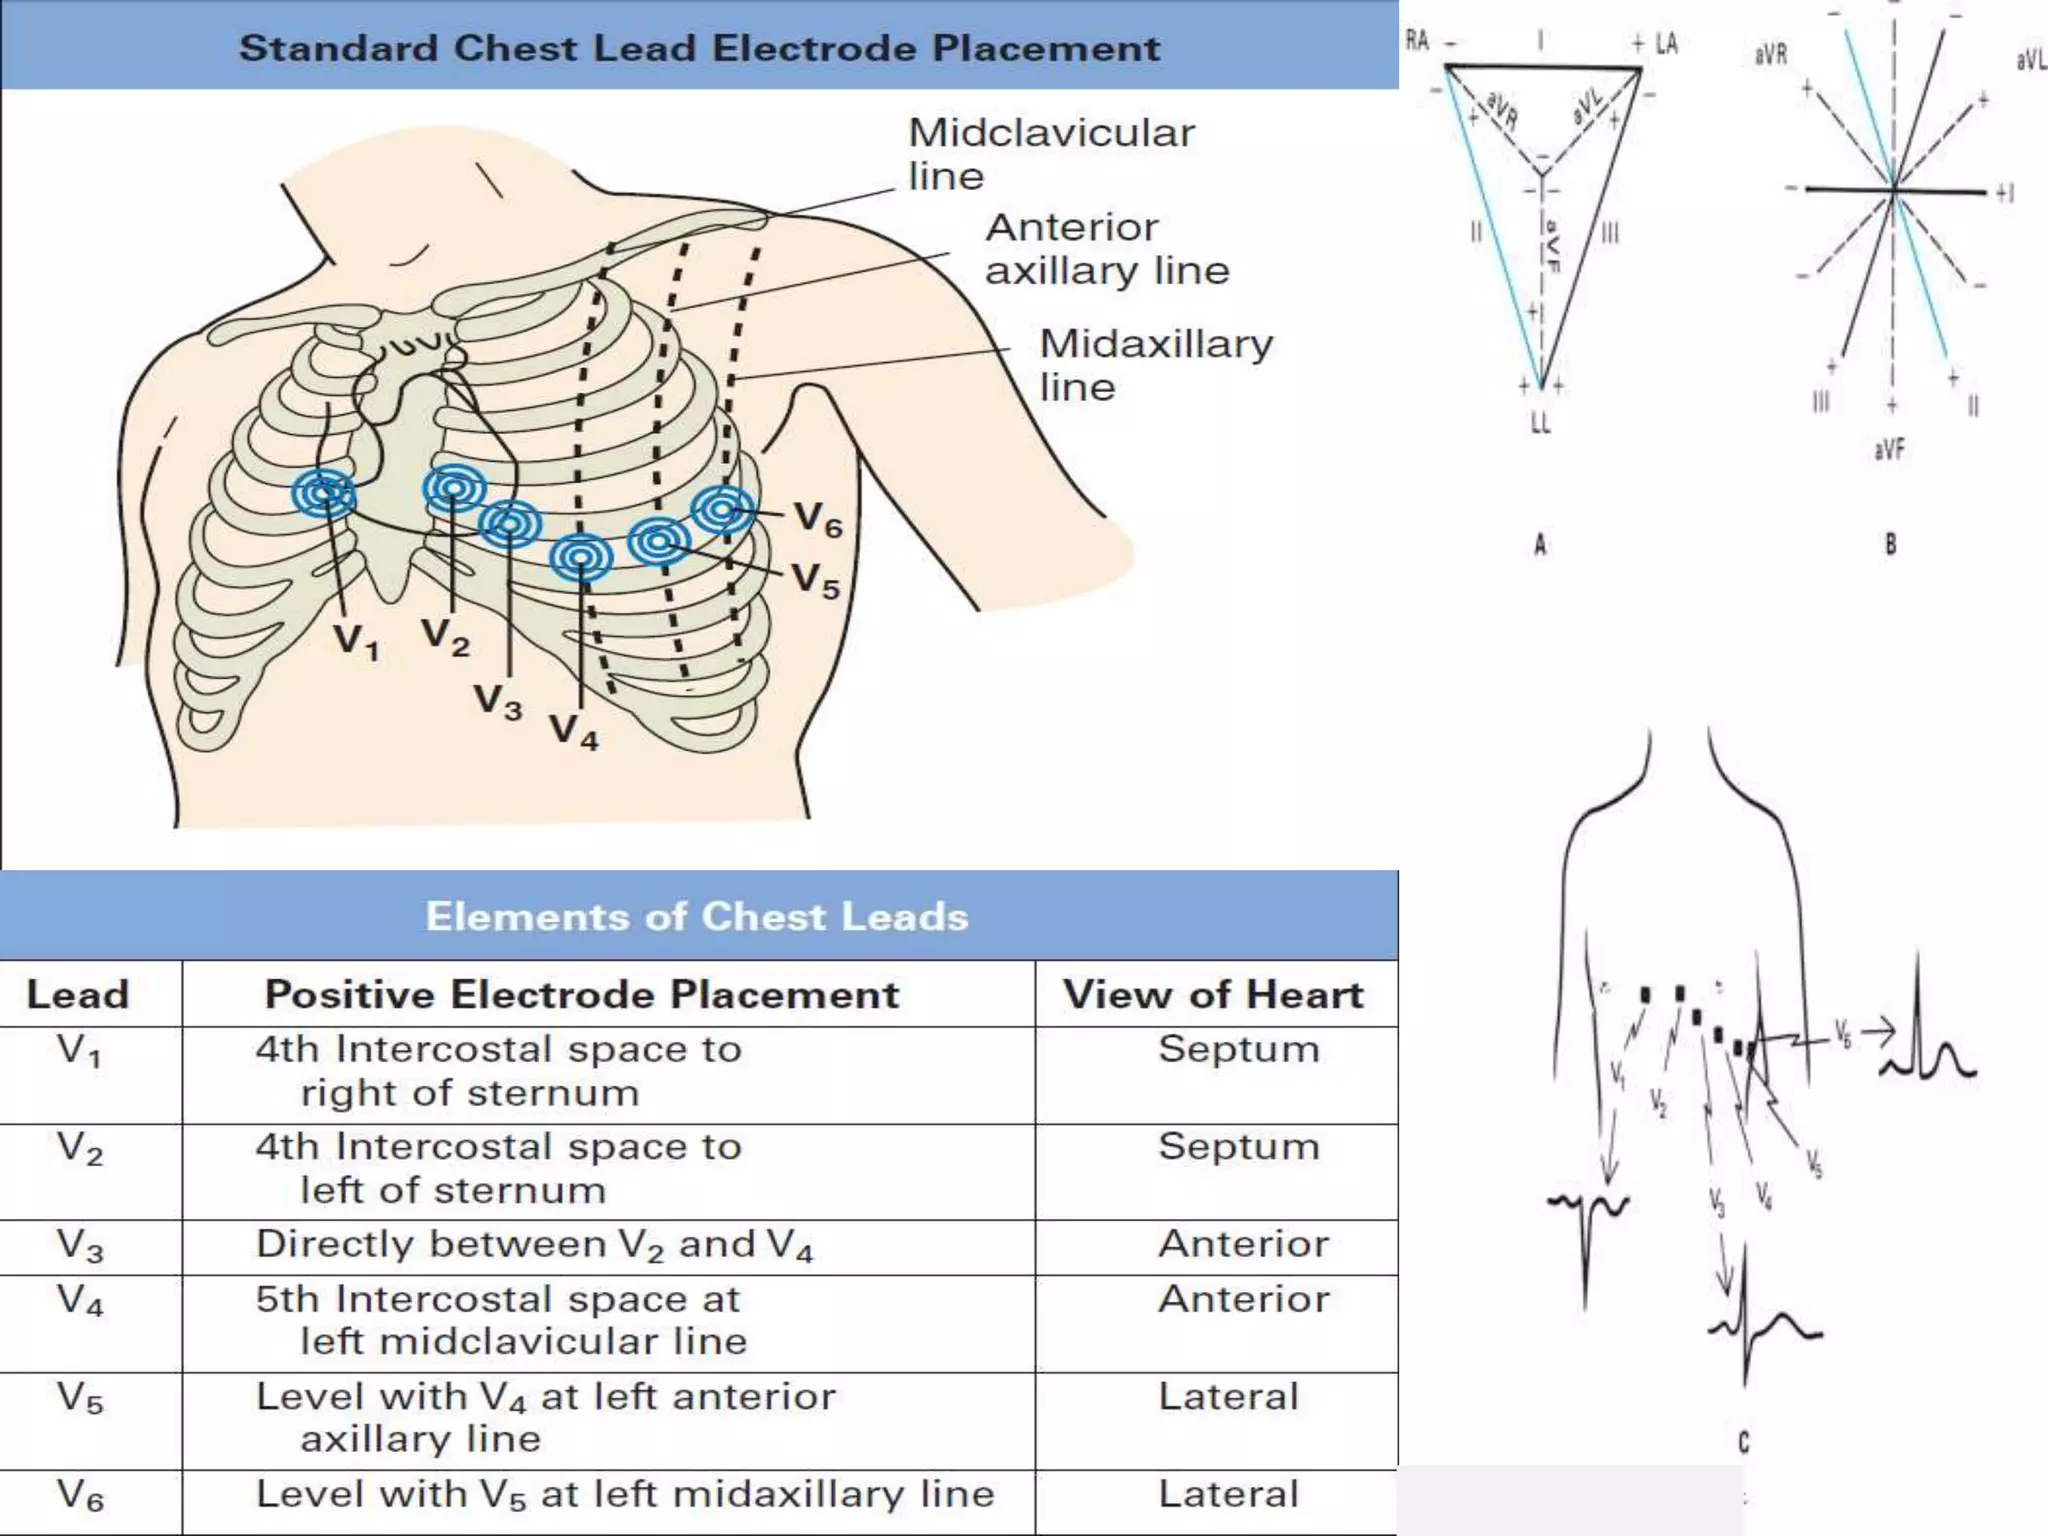
The anterior leads on an ECG—V1 through V6—sound straightforward. They're the precordial leads. Standard placement. But anyone who's run 500-plus ECGs knows the difference between a clean read and a diagnostic headache usually comes down to millimeter-level precision at the skin surface. I've pulled my hair out over ST elevation that turned out to be a lead placed one intercostal space too high. Here's what actually happens when you set up those six electrodes correctly, and where people regularly go wrong. V1 sits in the fourth intercostal space at the right sternal border. V2 goes in the same intercostal space at the left sternal border. That's textbook. The mistake most technicians make isn't finding those spaces—it's counting from the wrong landmark. If the patient has a large breast or a prominent sternum, you can easily miscount. I always palpate the angle of Louis first, which is the sternal notch junction, then slide down to find the second rib. From there, fourth space is two ribs down. Do that every time. It takes four extra seconds and prevents one common error pattern.
V3 lands midway between V2 and V4. V4 is fifth intercostal space at the midclavicular line. V5 sits at the same horizontal level as V4 but on the anterior axillary line. V6 is at the midaxillary line, same level. These spatial relationships matter because the electrical axis of the heart rotates across these leads. A myocardial infarction shows different patterns depending on which anatomical territory is involved. Anterior wall involvement shows in V1 through V4. Lateral involvement extends to V5 and V6. When you move a lead even slightly, you change which territory it's sampling. I encountered a specific problem last year that I still think about. A patient came in with chest pain and what looked like a significant anterior STEMI on the initial ECG. Strong ST elevation in V2 through V4. I called cardiology, they activated the cath lab team, and then I rechecked the lead placement because something felt off. V2 was sitting too high—fourth intercostal instead of fifth. When I moved it down to the proper fifth intercostal space, the ST changes nearly disappeared. The initial reading had been a false positive caused entirely by lead misplacement. This kind of thing happens more than you'd expect, especially on busy floors or when someone is rushing through a rapid assessment. The real challenge with anterior leads isn't just placement. It's interpretation in patients with complicating factors. Left bundle branch block changes everything about how you read those anterior leads. Septal hypertrophy from long-standing hypertension produces tall R waves in V1 and V2 that can mimic anterior injury. Obesity makes landmark identification harder and increases the distance between electrode and heart, which dampens signal amplitude. Chronic obstructive pulmonary disease shifts the heart position and can rotate the electrical axis in ways that make anterior leads look abnormal when nothing is actually wrong.
One counter-intuitive point that beginners consistently miss: deep S waves in V1 and V2 are normal. Everyone focuses on ST depression in those leads and jumps to conclusions about ischemia, but a deep S wave is just the normal sequence of ventricular depolarization moving away from the right precordial region. The S wave should get progressively smaller as you move from V1 to V6. If it doesn't, that's called poor R wave progression and it warrants attention, but the presence of a deep S in V1 alone is not pathological. Another nuance: the transition zone. This is where the R wave and S wave are roughly equal in amplitude. In most adults, this happens around V3 or V4. If the transition is delayed past V5, you might have right ventricular hypertrophy or a posterior MI. If it's early, around V1 or V2, you could be looking at left ventricular hypertrophy. Knowing where the transition should normally sit helps you catch abnormalities that don't present as dramatic ST changes. For actual technique, here's the practical workflow I use. Clean the skin with alcohol or light abrasion—removing dead skin cells and oils makes a measurable difference in signal quality. Shave excessive hair if needed. Press the electrode firmly so the adhesive makes full contact. Check impedance after placement; anything above five kilohms usually indicates a poor connection and needs reapplication. Run a quick rhythm strip and watch the waveform morphology on each lead before declaring the ECG ready. Flat lines, noise, or bizarre QRS shapes in one lead while the others look normal almost always points to a bad electrode rather than a cardiac problem.
Get the Full Details

There are scenarios where anterior leads simply cannot give you reliable information. Severe kyphoscoliosis changes thoracic anatomy enough that standard lead placement no longer maps to the expected cardiac territories. In those cases, you need to adjust based on bony landmarks rather than following the standard grid, or consider alternative imaging. Post-mastectomy patients with chest wall changes present similar problems. Also, portable ECGs on ventilated ICU patients often pick up massive artifact from the ventilator circuit, defibrillator pads, and other monitoring equipment. That artifact shows up prominently in the anterior leads because they have the highest sensitivity to surface noise. When anterior lead interpretation is unclear, the fallback is usually a 12-lead with additional right-sided and posterior leads. Right-sided leads (V3R through V6R) assess right ventricular involvement, which matters especially with inferior MI. Posterior leads (V7 through V9) catch posterior wall infarctions that don't show up in standard anterior positions. I've seen several MIs missed because the team relied only on V1 through V6 and never extended the lead set when the clinical picture didn't match the ECG. The most common error I see is skipping the impedance check and calling an artifact-ridden tracing normal. A noisy ECG that looks acceptable at first glance can hide subtle ST changes that are clinically significant. Take the extra thirty seconds to verify lead contact. It prevents more misreads than anything else in my experience.
What Most Resources Don't Tell You
Anterior lead placement has improved with smart electrodes and automated placement guides, but those tools aren't perfect. They struggle with morbidly obese patients and children. Manual landmark-based placement remains the gold standard when precision matters. The learning curve is real—new technicians need perhaps thirty to fifty supervised placements before their landmark identification becomes reliable enough to work independently without second-guessing every electrode. If you're studying for boards or certification, focus on the anatomical relationships. Know which ribs correspond to which intercostal spaces. Understand that the midclavicular line drops vertically from the midpoint of the clavicle, not from the nipple, because nipple position varies significantly between individuals and doesn't reliably indicate the correct intercostal level. Practice palpating the angle of Louis on yourself or a colleague until you can find it without thinking about it. That single landmark anchors almost everything else. There's no shortcut download or app that replaces actual hands-on practice. The knowledge is procedural, not theoretical. You learn it by doing the placement repeatedly and then correlating the ECG findings with clinical outcomes. I still double-check my V4 placement on every single patient, even after years of experience. Complacency is the real enemy here.