What You Actually Need to Know About Emory's Healthcare Innovation Playbook
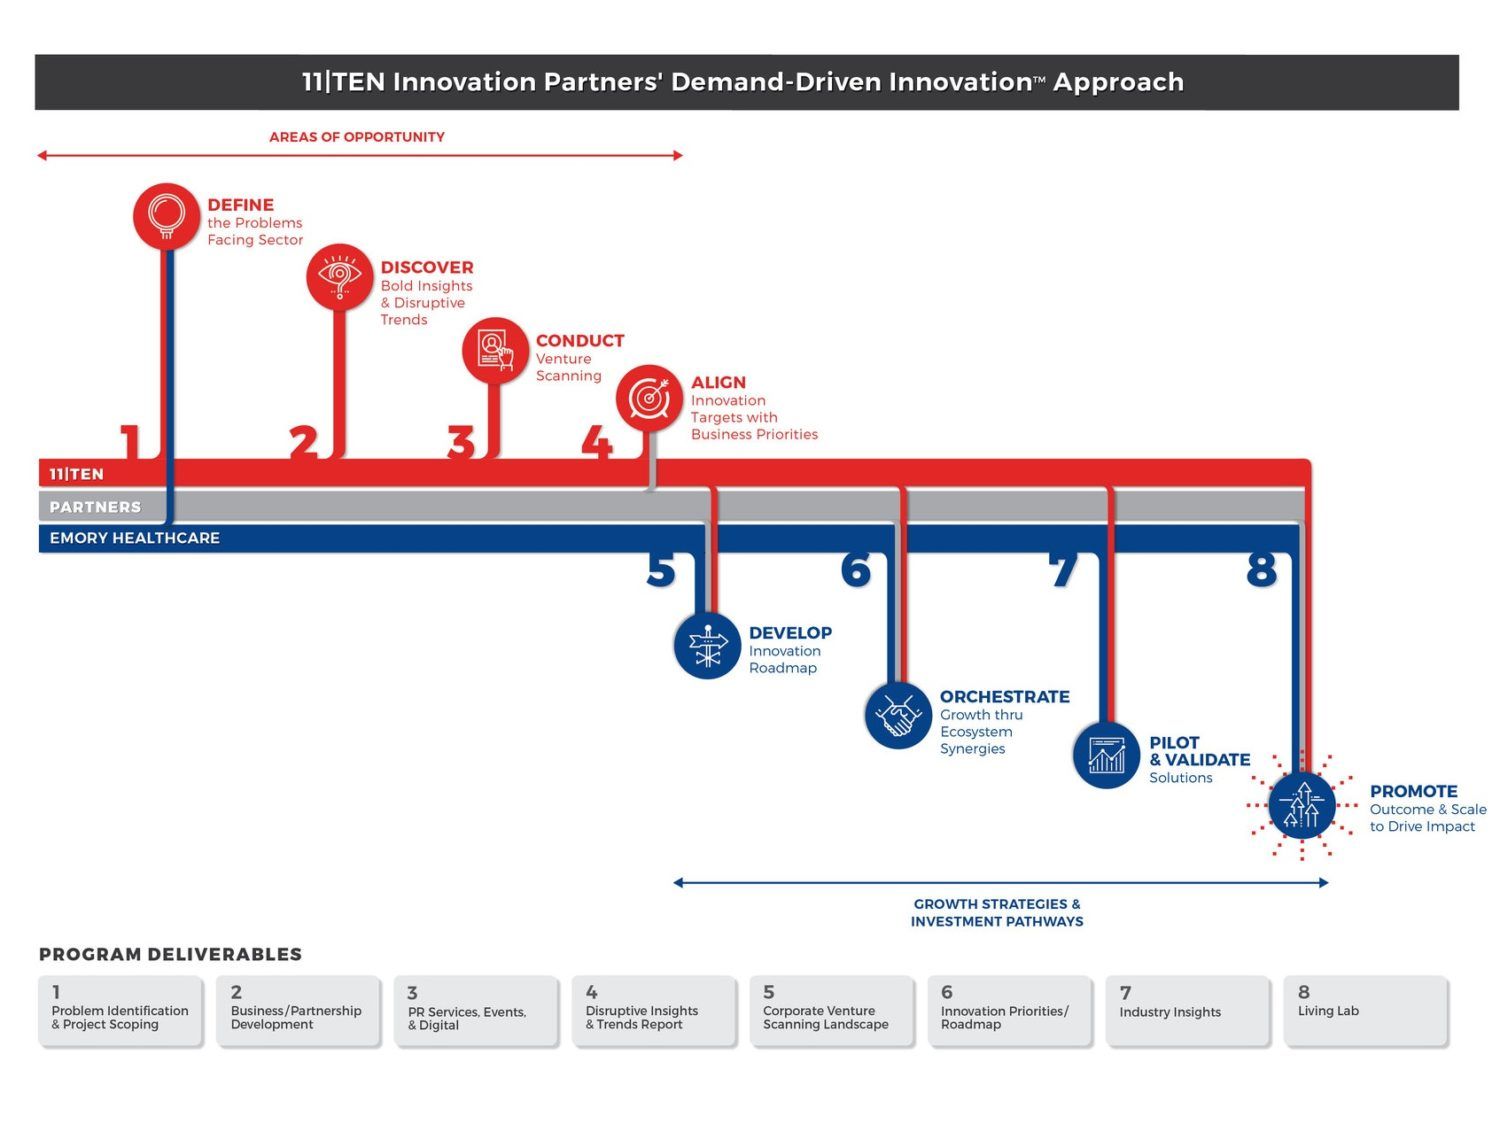
I ran into this framework while advising a group of clinicians at Emory who were trying to launch a quality improvement project that actually stuck. The standard playbook for healthcare innovation usually involves a lot of slide decks and buzzwords. The Emory Advantage blueprint is different because it forces you to tie every single initiative back to measurable patient outcomes before you spend real money. That constraint changes everything about how projects get built. At its core, this is a structured methodology that came out of Emory's clinical research and health systems architecture groups. It's not a product you download. It's a set of operating principles that tell you how to go from an idea to an implemented change in a hospital or clinic environment without the usual chaos. The five pillars are pretty straightforward: clinical problem definition, interdisciplinary team composition, evidence integration, iterative prototyping, and scale-readiness assessment. That last one is where most people fail, but more on that later. Here's the thing nobody tells you about this framework. It was originally designed around Emory's particular institutional setup, which means it assumes a certain level of existing data infrastructure and cross-departmental communication channels. If you're at a smaller community hospital without an EMR that talks to anything else, you're going to need to adapt the blueprint significantly. I learned this the hard way.
Last year I worked with a regional health system that wanted to implement the Emory Advantage model for reducing hospital-acquired infections. They bought into the framework and started building out their interdisciplinary teams. Everything looked good on paper for three months. Then they hit a wall when they tried to integrate their infection tracking data with their nursing workflow system. The two platforms used completely different data standards, and there was no middleware between them. The blueprint assumes you can pull real-time clinical data for your prototyping phase, but this system couldn't even generate a basic report that synced across departments. The workaround was brutal but effective. We stopped trying to force integration and instead built a manual data capture layer. Nurses filled out structured paper forms during each shift, and a dedicated analytics person entered the data daily into a simple SQLite database. It added maybe two hours of work per day for the team, but it let us run the iterative prototyping cycle the blueprint requires. Within six weeks we had enough clean data to prove the intervention worked, and only then did we justify the budget for proper system integration. The blueprint doesn't cover this scenario, but it's honestly the most common one I see in practice. Counter-intuitive insight number one: The framework's emphasis on "evidence integration" doesn't mean you need a full randomized controlled trial before acting. In my experience, a well-designed prospective cohort study with a concurrent control group, tracked over 60 to 90 days, gives you more actionable signal than a published meta-analysis that's three years old. The Emory model people understand this, which is why the evidence tier system allows for local data as legitimate evidence. Most institutions still treat internal data as second-class, and that hesitation costs lives.
Counter-intuitive insight number two: The scale-readiness assessment, which is supposed to be the final step, actually needs to happen at step one. I've watched too many teams build a perfect pilot intervention and then discover during the scaling phase that their hospital's staffing ratios, reimbursement structures, or union agreements make widespread adoption impossible. Running a lightweight version of the scale assessment upfront — even just a one-page matrix of barriers and enablers — takes about an hour and prevents months of wasted effort downstream. The practical workflow looks like this. You start by writing a one-paragraph clinical problem statement that includes a specific patient population, a measurable outcome gap, and a timeline for change. Something like: "Patients aged 65 and above admitted with heart failure exacerbation at Grady Memorial have a 30-day readmission rate of 24 percent, compared to the national benchmark of 19 percent. We aim to reduce readmissions to below 20 percent within 12 months." That's it. No slides. No stakeholder meetings yet. Just the problem statement. From there, you assemble the team. The blueprint specifies that every project must include at least one frontline clinician who directly treats the patient population, one data analyst, one process engineer or operations person, and one patient representative. I've seen projects skip the patient representative to save time. They always regret it later. The patient perspective catches workflow realities that clinicians and administrators miss entirely.
Get the Full Details

The evidence integration phase is where you review existing literature and internal data to understand what's already been tried and what worked. This isn't a literature review for its own sake. It's a targeted scan to identify the highest-leverage intervention points. I typically spend about two weeks on this phase for medium-complexity projects. The key deliverable is a prioritized list of three to five intervention candidates ranked by evidence strength and implementation feasibility. Prototyping follows. This is the iterative design and testing phase. You build a minimum viable version of your intervention and test it on a small scale — usually one unit or one clinic. The Emory framework recommends running at least three prototype cycles before declaring success. Each cycle should be one to two weeks long. The first cycle almost never works cleanly. Cycle two reveals the real issues. Cycle three is where you start seeing genuine improvement. Rushing through prototypes is the single biggest mistake I see teams make. After successful prototyping comes the scale-readiness assessment. This is a structured evaluation of whether the intervention can work at a larger scale given your organization's resources, culture, technology, and regulatory environment. The assessment covers seven dimensions: clinical workflows, technology infrastructure, staff training needs, financial sustainability, regulatory compliance, patient acceptance, and leadership alignment. Each dimension gets scored on a one-to-five scale, and anything below a three flags a risk that needs addressing before scaling.
Now for the part the official documentation doesn't emphasize enough. The blueprint assumes you have executive sponsorship from the start. In reality, you often need to generate enough early proof to earn that sponsorship. I've found that running a micro-pilot — a two-week, one-unit test with minimal resources — is usually enough to get leadership attention. The key is presenting results in the language administrators care about: cost savings, length of stay reduction, patient satisfaction scores, and readmission penalties avoided. A single well-executed micro-pilot can convert skeptics faster than any business case document. There are real limitations to this framework, and I want to be clear about them. First, it works best in large academic medical centers with existing research infrastructure. Smaller community hospitals will need to compress several phases and may not be able to support the dedicated data analyst role that the blueprint recommends. Second, the timeline assumptions are optimistic. The standard model suggests six to nine months from problem statement to scale decision for a moderate-complexity intervention. In practice, even streamlined projects often take ten to fourteen months due to IRB reviews, procurement delays, and staffing changes. Budget for the longer timeline from day one. Third, the framework is heavily weighted toward clinical process improvements. It's less useful for technology development projects like building a new app or device, where the innovation lifecycle follows different patterns. If your project is primarily a product development effort, you'd be better served by combining elements of the Emory Advantage with a lean startup or design thinking approach rather than trying to force it into the clinical innovation mold.
Fourth, and this is important, the blueprint doesn't adequately address the post-implementation sustainment phase. Getting an intervention to scale is one thing. Keeping it running two years later when the original champions have moved on is another. I recommend building a sustainment plan into your scale-readiness assessment from the beginning. That means designating an ongoing ownership role, establishing quarterly performance reviews, and planning for staff turnover with documented Standard Operating Procedures. If you're looking to access the actual framework documents, they're available through Emory's clinical innovation research network. The core playbook is a roughly 40-page document covering the five pillars in detail, plus supplemental templates for problem statements, team charters, and the scale-readiness assessment matrix. There's also a companion workbook with case studies from implemented projects. These resources aren't behind any paywall, but you do need to go through Emory's institutional partnership process to access the full package. Individual practitioners can usually get the core playbook through a formal collaboration request or by attending one of their quarterly innovation workshops. The workshop route is honestly the faster path if you need this for an active project. The workshop format covers the framework in a day, gives you hands-on practice with the templates, and connects you with Emory staff who can answer questions specific to your institutional context. Travel and lodging aren't free, but compared to the cost of implementing a flawed innovation project, it's a reasonable investment. I'd recommend attending before diving into the documents solo, especially if your organization doesn't have prior experience with this type of structured innovation work.

One final note that might save you some trouble. Don't try to implement the entire blueprint at once across your organization. It's designed for project-level use, not organization-wide transformation. The most successful institutions I've seen adopt it selectively, applying the framework to high-priority initiatives where they want the best chance of success. Rolling it out universally tends to create resistance and dilute the rigor that makes the framework effective in the first place. Pick two or three projects, run them through the full cycle, learn from the results, and expand from there. That's how this actually works in the real world.