Reading an ECG Is Not Something You Pick Up in a Weekend
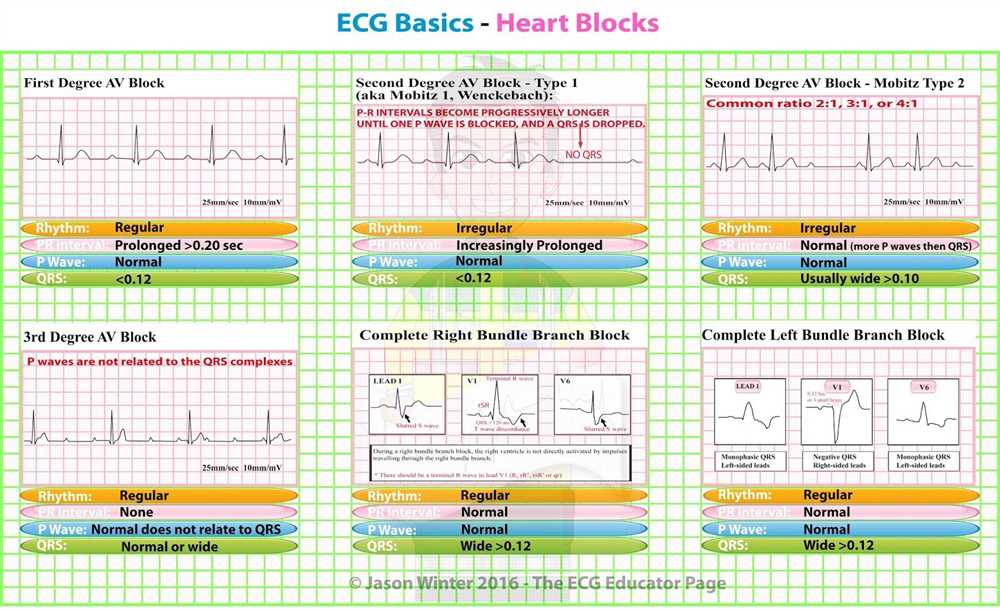
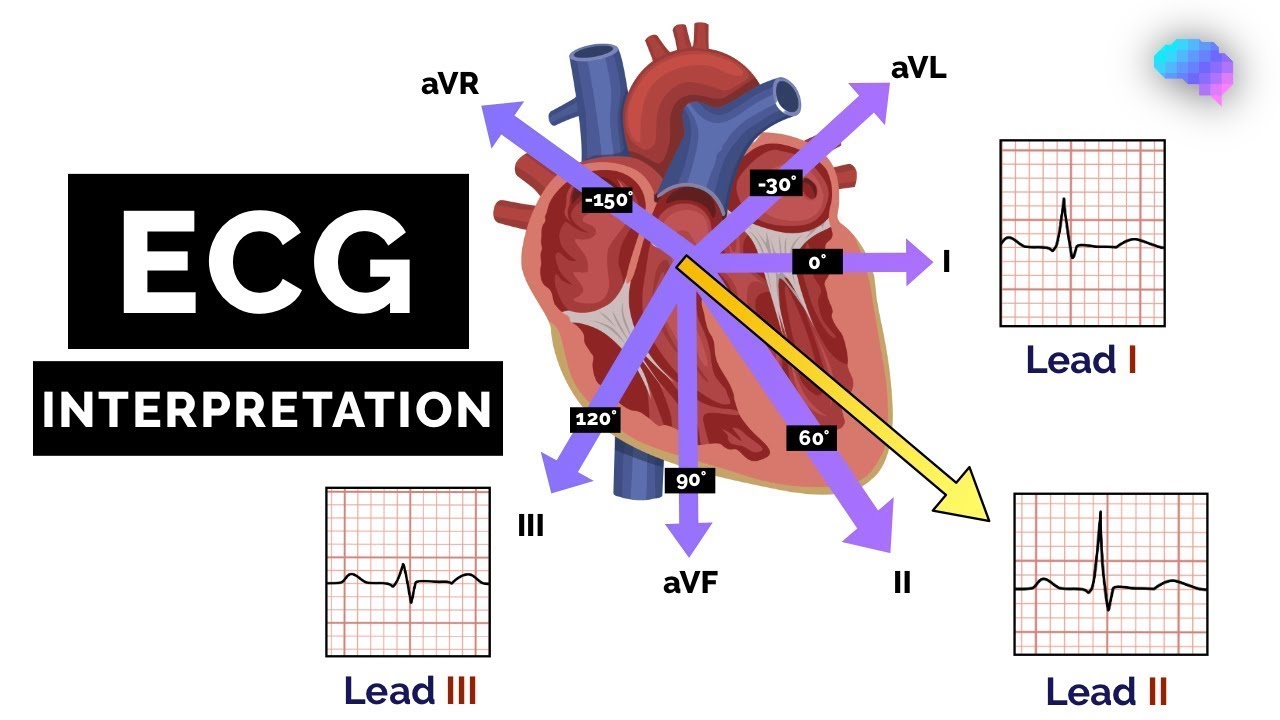
The Electrocardiogram Unlocking The Secrets Of The Heart requires patience and deliberate practice. I have spent years looking at these squiggly lines, and I still get tripped up occasionally. Here is what I have learned about actually using an ECG in clinical practice rather than just passing an exam. An ECG records the electrical activity of the heart through electrodes placed on the skin. The standard 12-lead setup uses ten electrodes. Six go on the chest. Four go on the limbs. That is all there is to it mechanically. The machine amplifies the tiny voltage changes your heart produces and draws them on paper or a screen. What you see on the page is a graphical representation of depolarization and repolarization across different views of the heart. Most people learn the theory first. They memorize that lead II is the rhythm lead, that the QT interval matters, that ST elevation means something bad. This is fine. But the practical skill comes from actually reading dozens of strips day after day until patterns become familiar. I used to read one ECG at a time and overthink each wave. Now I process about fifteen an hour when things are moving quickly. The difference is pattern recognition, not knowledge.
Here is how I actually read an ECG in practice. I start with the rate. I do not calculate it precisely unless I need to. I look at the distance between R waves and estimate. Regular rhythm? Good. Irregular? Then I slow down and figure out why. I check for P waves next. If they are not before every QRS, something is going on. Then I scan the ST segments. This is where most acute problems reveal themselves. A depressed ST by a millimeter or two can be normal in some leads. The same amount of depression in V4 and V5 is a different conversation. I look at the T waves too. Inverted T waves in certain leads are a red flag. I check the QT interval by eye first, measuring from the start of the QRS to the end of the T wave. If it looks long, I calculate it properly using Bazett's formula. The corrected QT should be under 450 milliseconds in men and under 470 in women. I remember reading a strip once where the diagnosis was missed by the automated interpretation. The machine called it a normal sinus rhythm with early repolarization. The patient was a forty-two-year-old man who came in with chest pain. When I looked at it myself, I noticed subtle ST depression in V3 and V4 that the algorithm had glossed over. It turned out to be an anterior ischemic event. The automated readings catch obvious stuff well. They miss subtleties frequently enough that you cannot rely on them alone. I always trust my own reading over the machine output, especially when the clinical picture does not match what the computer says.
Common Pitfalls That Waste Time
Lead placement errors are the most frustrating problem I deal with. I had a patient where the right and left arm leads were reversed. The ECG showed an abnormal Q wave in lead I and poor R wave progression across the precordial leads. It looked like an old anterior infarction on paper. I spent twenty minutes thinking about it before I checked the electrodes and found the swap. Reversed limb leads flip the axis and can mimic pathology that does not exist. This happens more often than you would think, especially in emergency settings where someone is rushing to hook up the machine. Another issue is artifact. Muscle tremor from shivering patients, 60-cycle interference from faulty grounding, and baseline wander from poor skin prep all create noise. I once spent five minutes trying to interpret a tracings that was mostly just the patient's tremor. Cleaning the skin with alcohol and using abrasive pads to remove the top layer of dead cells usually fixes baseline wander. Checking that the electrodes are actually stuck on tight and not peeling at the edges helps too. Pacemaker recognition is another area where beginners struggle. A properly functioning pacemaker shows sharp pacing spikes before the P waves or QRS complexes depending on whether it is atrial or ventricular pacing. But sometimes the spikes are small and easy to miss, especially in V1 where the amplitude of the spike is lower. I learned to look carefully at every beat in the rhythm strip before calling a rhythm sinus. Missing a pacer spike can lead you to diagnose bradycardia when the patient is actually being paced adequately.
Get the Full Details
What the ECG Cannot Tell You
The ECG has real limitations. It is a snapshot in time. A normal ECG does not rule out coronary artery disease. I have seen patients with significant blockages who had completely unremarkable tracings during their visit because they were not having active ischemia at that moment. Serial ECGs are more useful than a single one for chest pain patients. Get one on arrival, repeat it in fifteen to thirty minutes if symptoms persist, and compare them side by side. Changes over time are more informative than any single tracing. The ECG also does not assess mechanical function. A patient can have a relatively normal ECG and still have severely reduced ejection fraction. An echocardiogram is the tool for that. Using an ECG to guess cardiac structure is unreliable. It tells you about rhythm, conduction, and some aspects of ischemia and hypertrophy, but it is not a comprehensive cardiac assessment tool. If you want to get better at this, the practical advice is straightforward. Read as many ECGs as possible. Compare the strips to the eventual diagnosis. Keep a folder of interesting cases and review them periodically. Use free resources like Life in the Fast Lane and the ECG Wave-Maven archives from the University of Utah. These have large libraries of annotated tracings with explanations. The cost is zero and the quality is solid.
I downloaded the MIMIC database once and spent weeks going through it with the clinical correlates attached. It gave me a sense of how ECG findings correlate with actual outcomes and interventions. That experience changed how I approach a new strip. I stop looking for the classic textbook presentation and start asking what this pattern actually means for the patient in front of me. There is no shortcut to this. The computer will help you spot gross abnormalities. It will flag arrhythmias and obvious ST changes. But it will not replace the deliberate practice of looking at each lead systematically and thinking through what you see. That part is entirely on you.