
Gamma Rays In Practice
Gamma rays are photons with energies above roughly 100 keV, produced when atomic nuclei transition from excited states or during particle-antiparticle annihilation. They don't have mass and they travel at the speed of light, which makes them fundamentally different from the charged particle radiation most people picture when they hear the word "radiation." You can't block them with paper or plastic the way you block alpha or beta. Lead and thick concrete are the materials that actually work, and even then you're reducing intensity, not stopping it completely. The three main mechanisms matter for gamma rays is the photoelectric effect, Compton scattering, and pair production. At lower gamma energies, the photoelectric effect dominates, where the photon dumps all its energy into a bound electron. Around the megaelectronvolt range, Compton scattering takes over, meaning the photon bounces off an electron and loses only part of its energy, which is why shielding gets much harder past a certain point. Above 1.022 MeV, pair production becomes possible, creating an electron-positron pair near a nucleus. The exact crossover energies depend on the material's atomic number, which is why high-Z metals like lead are better shields per unit thickness than lower-Z alternatives. I spent years working with Cobalt-60 sources and Ir-192 in industrial radiography and medical sterilization facilities. The thing nobody tells you about gamma ray work is that the dose rate drops so dramatically with distance that you never actually get anywhere near a lethal exposure if you respect the inverse square law. I once had a team member complain about "getting hammered" during a source change. We traced it back to a malfunctioning collimator that was scattering radiation instead of directing it, and the real source was sitting behind a wall that was supposed to block everything. Once we swapped the collimator, the readings dropped from about 80 mSv/h down to 0.3 mSv/h at the same position. It's a fairly common failure mode in older installations.
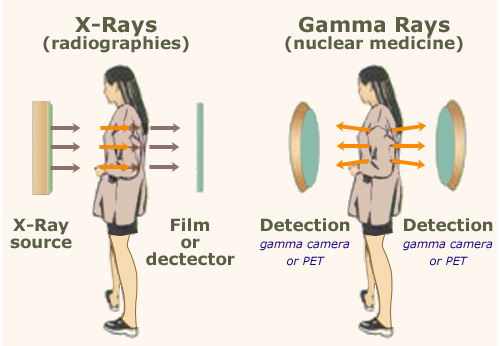
Another thing that trips people up is the difference between exposure and absorbed dose. A gamma ray field and the dose your body actually takes in are not the same number, and the conversion depends on energy. At 1 MeV, 1 Roentgen of exposure translates to roughly 0.0096 Gy in soft tissue, but at 100 keV it's closer to 0.028 Gy because the photoelectric effect couples more efficiently at lower energies. If you're converting old survey meter readings, getting this factor wrong by a factor of three is something I've seen happen repeatedly in accident reports. Gamma irradiation is also used for food sterilization and medical device processing, typically at doses between 15 and 45 kGy. The reason this works so well is that gamma rays penetrate sealed packaging. You don't need to open anything, which means you can sterilize things that would be contaminated during traditional autoclaving. The tradeoff is that some polymers degrade, and certain plastics become brittle after repeated exposure. I've seen PTFE gaskets fail prematurely in sterilized assemblies because the gamma dose broke the polymer chains. When that matters, you switch to electron beam processing, which has lower penetration but causes less bulk degradation. In medicine, external beam radiotherapy relies heavily on high-energy X-rays and gamma rays from sources like Co-60 or linear accelerators. The therapeutic window exists because tumor DNA repairs double-strand breaks more slowly than normal tissue. A typical fractionated schedule of 2 Gy per session over several weeks exploits this difference. What people don't realize is that the biological effectiveness of gamma rays is actually on the lower end of the radiation spectrum. Alpha particles and neutrons have much higher relative biological effectiveness values, but they can't be used for deep tumors because they stop after a few cell layers. Gamma rays win on penetration, even if they're less destructive per unit dose.
The half-life problem with Cobalt-60 is real and often underestimated. It decays at about 13% per year, which means a treatment machine that was calibrated five years ago is delivering roughly half the dose rate it originally was. Facilities that don't account for this either run treatments twice as long as needed or underdose patients. Some centers in developing countries still operate older Co-60 units precisely because linear accelerators require electrical infrastructure and maintenance budgets that aren't always available. That's not a moral judgment, just an operational reality I've seen firsthand. Gamma spectroscopy is another practical application where understanding the interaction mechanisms matters. NaI(Tl) detectors are cheap and adequate for rough identification, but their energy resolution is around 7% at 662 keV, which means two nearby peaks will blur together. HPGe detectors cost ten times as much and need liquid nitrogen cooling, but they give you sub-1% resolution. If you're doing environmental sampling near a nuclear facility, the difference between resolving Cs-137 from Ba-133m and not resolving them is the difference between a useful measurement and a guess. I learned that the hard way on a site survey where an NaI detector kept showing "elevated cesium" that turned out to be a scattered Ba peak. There's also the issue of activation. Bombarding materials with high-energy gamma rays above the giant dipole resonance threshold can make the material itself radioactive. This happens routinely in accelerators and spallation sources. A steel component near a 10 MeV gamma field can produce Mn-56 and Fe-55 through photoneutron and photonuclear reactions. The induced activity usually decays within days or weeks, but if you're handling activated parts, you need to treat them as radiation sources until the dose rates drop to background. I've walked into rooms where maintenance workers were using unshielded tools that had been near an operating linac, and the dose rates on the tool handles were in the tens of microsievert per hour. A simple lead brick box solved the problem immediately.
Get the Full Details
For people who want to understand this more deeply, the ICRU reports and NIST's XCOM database are the standard references. XCOM gives you cross-section data for every element at every energy, and it's freely available online. If you're designing shielding or interpreting spectral data, you should be using it rather than guessing from a textbook table. I keep a bookmark to it in my browser. Most of the confusion I see in this field comes from people working with approximate numbers instead of the actual physics.




