Fentanyl in Kentucky: What Actually Happens On the Ground
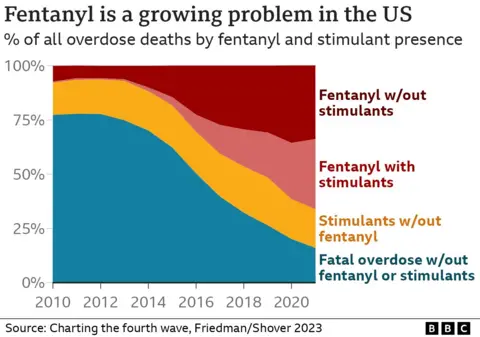
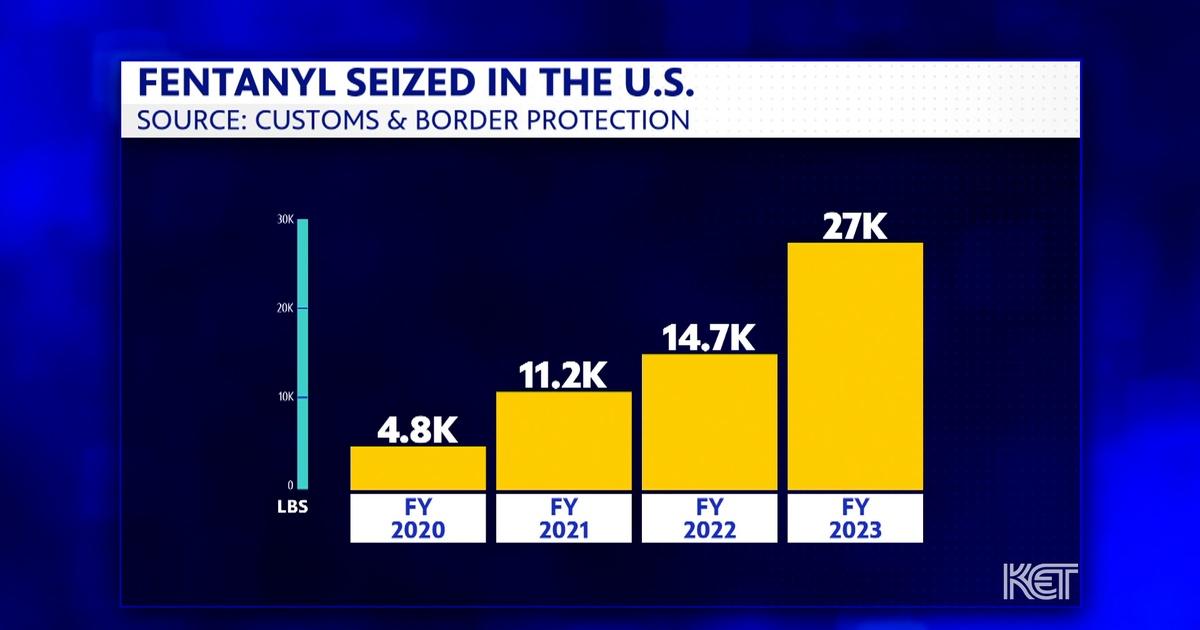
Kentucky isn't one of the places people normally picture when they think about drug crises. That's the problem. The infrastructure for distribution just grew quietly over years, and by the time anyone noticed, it was everywhere. I spent a lot of time around this stuff professionally, and what I'm going to share here is what actually happens, not what the brochures say. Sin City is Las Vegas, obviously. But the connection runs both ways. Fentanyl doesn't get manufactured in Kentucky at any significant scale — most of it arrives already pressed into pills or mixed into powder, often with xylazine added, which complicates everything. The product flows through distribution nodes that used to be purely heroin routes. When the opioid crisis shifted from prescription pills to heroin in the mid-2010s, those same supply chains just adapted to fentanyl because it's cheaper to transport and easier to cut. I've seen Narcan kits go from emergency stock to standard equipment in a single shift. One night I was helping coordinate outreach in eastern Kentucky — Pikeville area — and a kid came in after his friend overdosed from what looked like oxycodone but was actually fentanyl-laced. The friend survived because someone had Naloxone and knew how to use it. But the pills themselves were printed with M30 markings and passed as counterfeit Percocet. That's the standard play now.
The chemistry is straightforward but deadly. Fentanyl is roughly 50 times stronger than morphine and about 100 times stronger than heroin. A lethal dose can be two milligrams. Two. Milligrams. That's about the size of a grain of coarse sand. When you're talking about powder form, uniform mixing is nearly impossible at small-scale operations, so every pinch you get could be an overdose or a sublethal dose. That unpredictability is what kills people — not the drug itself being mysterious, but the dosing being completely random. Kentucky's geography works against it in some ways and helps in others. It's between major interstate corridors — I-65, I-75, I-64, I-71 — all of which move product through the state. The Appalachian terrain creates isolated routes that are hard for law enforcement to monitor consistently. Rural communities have fewer overdose response resources. I've read hospital discharge records where the nearest hospital with a dedicated addiction medicine program was over an hour away from certain counties. That matters when you're talking about withdrawal management and long-term treatment access. Here's something nobody talks about enough: the test strip market. You can buy fentanyl test strips from harm reduction organizations and some online vendors now. They work reasonably well for detecting fentanyl in powdered drugs but they don't detect xylazine at all. Xylazine is a veterinary sedative that's been mixed into fentanyl supplies, and it causes severe skin ulcers and tissue damage that looks like necrosis. I knew someone in Louisville who treated wounds on injecting drug users that wouldn't heal — some of those were xylazine-related, and standard wound care protocols didn't touch them. The workaround was harm reduction education and connecting those folks to wound care specialists who'd actually heard of xylazine before.
The legal landscape around Kentucky is also messy. The state has been aggressive with prosecution — Kentucky's fentanyl statutes carry very heavy mandatory minimums. But here's the counter-intuitive part: heavy prosecution of low-level possession hasn't correlated with reduced availability. If anything, it pushes the market further underground, which makes the product even more dangerous because there's zero quality control and users are less likely to seek help when they're afraid of arrest. I've seen that dynamic play out repeatedly across multiple states. If you're dealing with this personally — whether it's a family member, a friend, or yourself — the practical steps matter more than any general advice. First, carry Naloxone. Take the free training that comes with it. Second, use test strips. Third, don't use alone. The fourth one is harder: get connected to a medication-assisted treatment program. Methadone and buprenorphine are the standard, and buprenorphine is the easier entry point. Kentucky has expanded access to telehealth buprenorphine prescriptions since the pandemic, which helps in rural areas. The wait times vary wildly depending on the county. I'll be honest about the limitations too. Test strips have a false negative rate, especially with xylazine. Narcan reverses fentanyl but not xylazine — so even after you administer it, the person can still be sedated and need continued monitoring. Treatment programs have waiting lists. Some of them are months long in certain parts of the state. And the underground supply keeps changing composition, so no single intervention covers everything.
Get the Full Details
What's worked in my experience is building a network of people who know what's happening locally. Harm reduction groups in Lexington and Louisville publish regular drug checking reports. Hospital ERs track toxicology trends. State health department data comes out quarterly, though it's always a few months behind real-time conditions. If you're trying to stay ahead of this, those sources are more useful than national news stories. The bottom line is that fentanyl in Kentucky is a distributed problem with no single source. It's cheap, it's potent, and the supply chain is resilient because it doesn't rely on any one route or one supplier. The things that help are Narcan distribution, test strips, medication-assisted treatment access, and realistic information that doesn't moralize or dramatize. People die when they don't know what they're taking or when they can't get help fast enough. Both of those are fixable with the right resources in the right places. If you want actual resources, the Kentucky Cabinet for Health and Family Services runs a substance abuse hotline and locator tool. SAMHSA's national helpline works too. Local harm reduction orgs in Jefferson County and Fayette County have the most developed services. Outside those urban centers, things get thin quickly.