Why Your Skin Gets Rough Around Saline Exposure
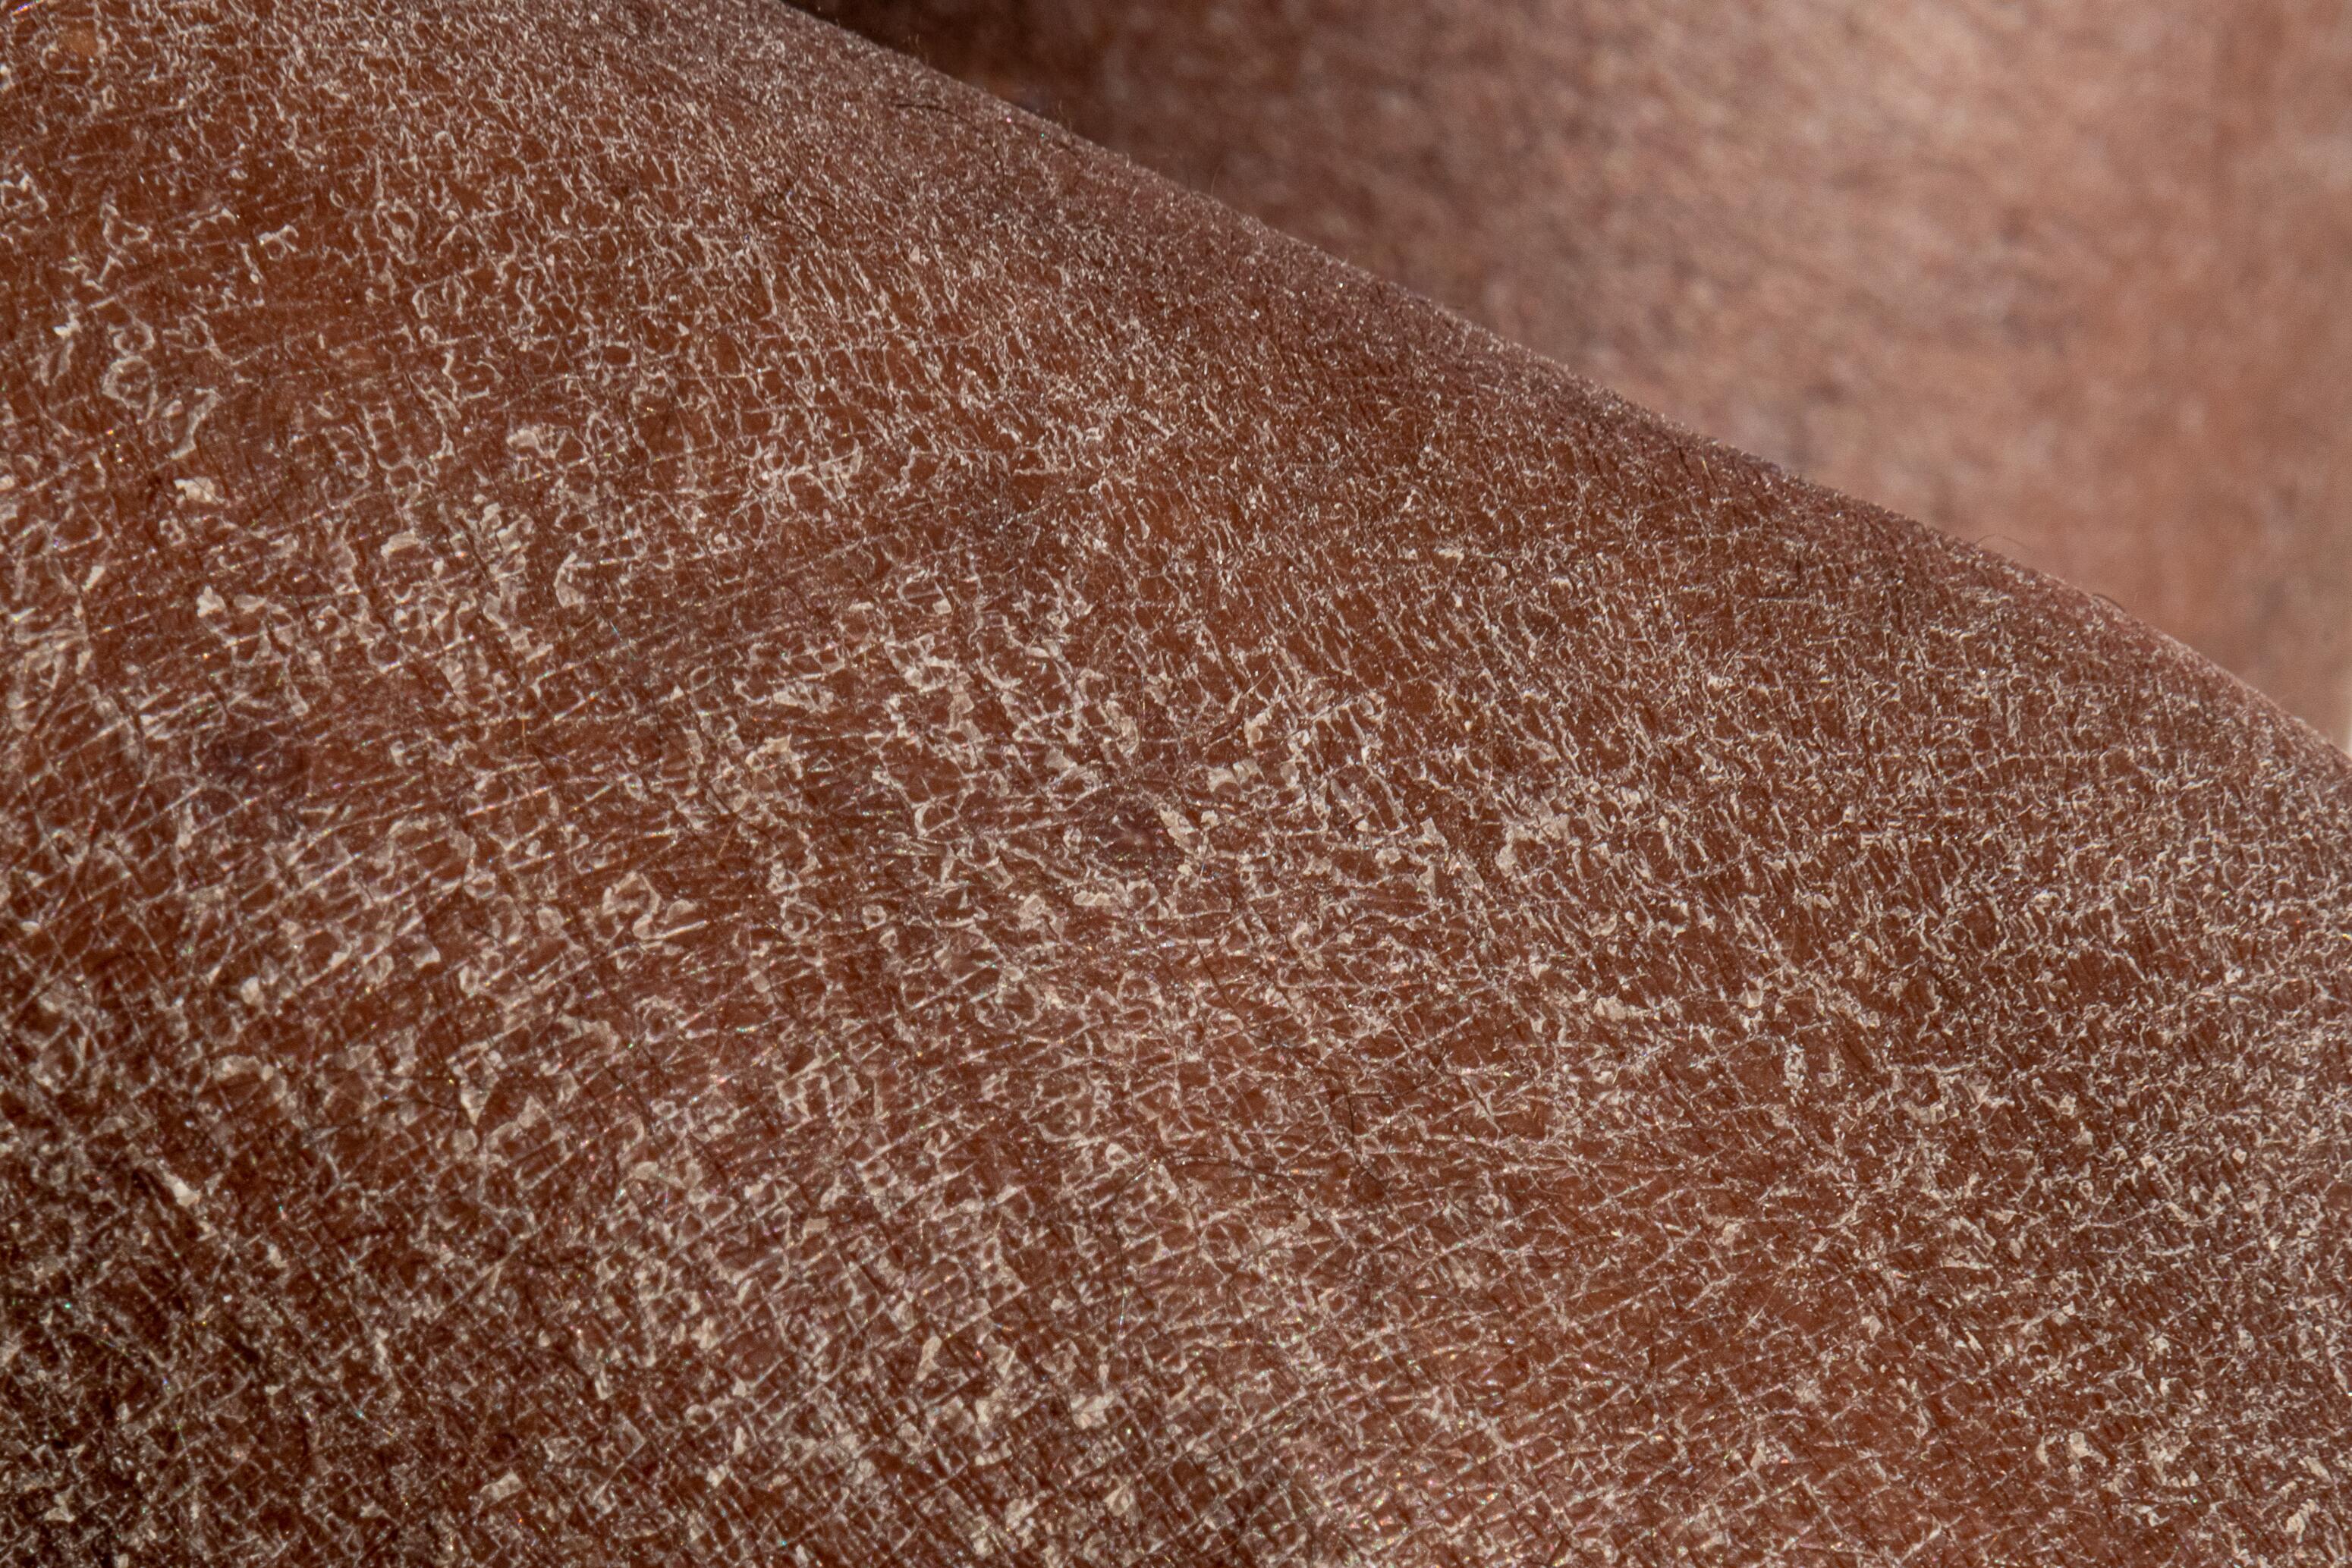
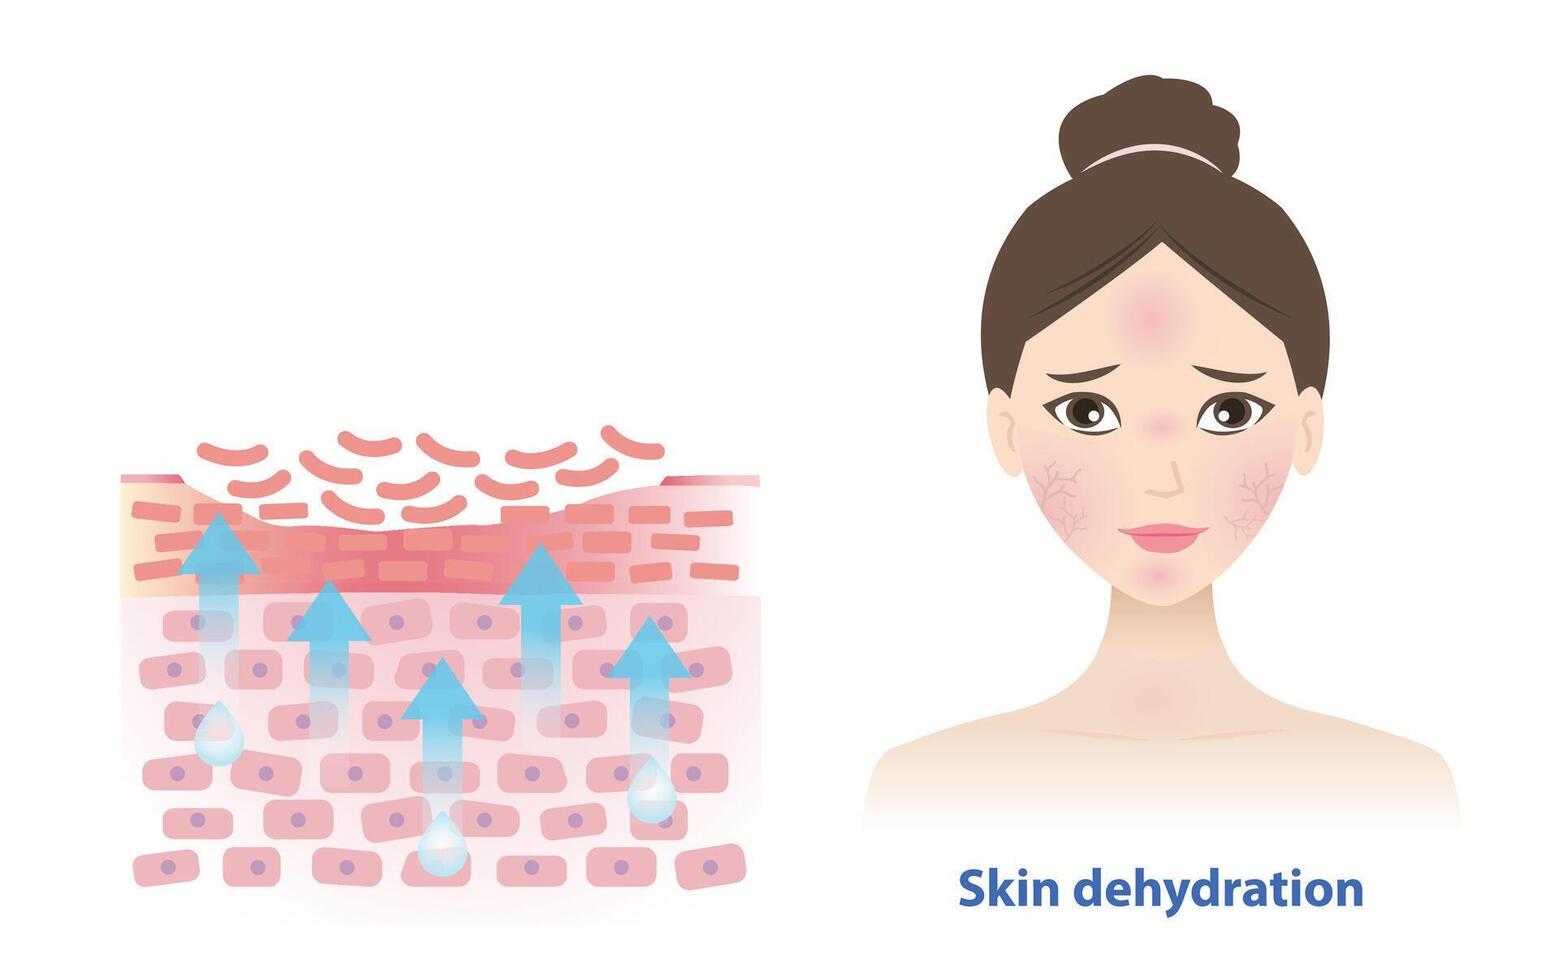
Saline solutions sound harmless. They are basically salt water, right? That is what everyone assumes until they spend enough time working with them and realize how aggressively they pull moisture out of tissue. I deal with this regularly in clinical settings and home care, and the damage is rarely obvious until it becomes chronic irritation or a cracked barrier. When you expose skin repeatedly to normal saline or any hypertonic solution, the osmotic gradient pulls water out of the epidermal cells. This is basic physics, but the real-world effect is not just mild dryness. Over time the stratum corneum loses its lipid matrix integrity, micro-fissures form, and the skin enters a cycle where it cannot retain moisture even after the saline is rinsed off. That is the core problem most people miss. I remember one specific case last year involving a home care nurse who was using saline wipes for wound cleaning around the periwound area on elderly patients with thin skin. She reported increased redness and flaking within days of starting a new protocol. The issue was not an allergy. It was repeated hypertonic exposure without any barrier protection. I had her switch to applying a thin layer of petrolatum around the wound site before cleaning and then moisturizing with a ceramide-based cream afterward. The flaking stopped within a week. That was a clear example of mechanical dehydration versus immune response, and mixing those up leads to wrong treatment decisions.
How Saline Actually Dehydrates Skin
Normal saline is 0.9% sodium chloride. That concentration matches blood plasma, which is why it is called isotonic. It should theoretically not cause fluid shift, right? In practice, repeated application and evaporation change everything. As the water evaporates from the skin surface, the remaining salt becomes more concentrated locally. The area near the skin becomes hypertonic compared to the deeper layers, and water migrates outward to balance the gradient. This is called evaporative concentrating, and it happens every time saline is applied and left to air dry instead of being blotted or rinsed. Hypertonic saline solutions, sometimes used in nasal care or wound management, make this effect much worse. A 3% saline solution will actively draw fluid from the outer skin layers in minutes. People use these for decongestion or cleaning without realizing that splash-back onto surrounding skin is a silent dehydrating event. The skin around the nostrils of frequent nasal spray users is a common place to see this damage. It looks like eczema but responds poorly to steroid creams because the root cause is repeated osmotic stress, not inflammation alone.
Who Is Most at Risk
Certain populations experience far more damage from the same exposure. Elderly skin has a thinner stratum corneum and reduced sebum production, so the barrier recovers slower. Diabetics often have compromised microcirculation in the extremities, meaning dehydration-induced micro-tears take longer to heal and can progress to ulcers. Healthcare workers who sanitize and clean wounds multiple times a day accumulate exposure that adds up quickly. Even something as simple as using saline to rinse eyes can dry out the surrounding periocular skin if not blotted properly afterward. People with pre-existing conditions like atopic dermatitis or psoriasis should be especially careful. Their barrier function is already impaired, and saline exposure can trigger flare cycles that seem unconnected to the actual cause. I have seen patients apply saline to soothe irritated skin, thinking it is gentle, only to make the condition significantly worse within days. The irony is real and worth understanding before any self-treatment attempt.
Get the Full Details

Practical Steps To Prevent Damage
The first step is switching your application method. Instead of letting saline air dry on the skin, use a sterile gauze to gently blot the area after cleaning. This removes excess solution before evaporation can concentrate the salt. If you are using saline sprays near the nose or eyes, keep the application directed and wipe away any runoff immediately. The second step is barrier protection. Apply a light occlusive like petrolatum or a dimethicone-based cream to areas that will see repeated saline contact. This creates a physical barrier between the solution and the skin. It does not interfere with wound healing in most cases and has been standard practice in wound care guidelines for years. The third step is post-exposure rehydration. Use a moisturizer containing humectants like glycerin or hyaluronic acid followed by an occlusive to seal moisture back into the skin. This combination works because humectants attract water into the stratum corneum and the occlusive prevents transepidermal water loss.
Common Mistakes People Make
Many people assume that because saline is "just salt water," it is inherently safe for skin. This leads to overuse. Some patients use saline soaks for dry, cracked hands thinking it will cleanse and heal at the same time. Soaking in saline actually accelerates dehydration because prolonged immersion increases the time the osmotic gradient acts on the skin. Ten minutes of soaking can do more damage than a quick rinse. Another mistake is confusing saline with sterile water. Sterile water is hypotonic and causes cells to swell, while saline is isotonic or hypertonic depending on formulation. Both can damage skin if used improperly, but in completely different ways. Using the wrong solution based on a misunderstanding of tonicity is a frequent error in home care settings where products are labeled confusingly. A third pitfall is using tap water mixed with salt to make homemade saline. The concentration is almost never accurate, and contamination is a real risk. Commercial sterile saline is inexpensive and widely available. Making your own introduces variability that can worsen dehydration or cause infection. The cost difference is negligible compared to treating a skin infection or severe barrier damage.
When To Seek Professional Help
If the skin shows persistent redness, cracking, bleeding, or signs of infection such as warmth and pus after repeated saline exposure, stop home treatment and see a dermatologist or wound care specialist. These symptoms indicate the barrier has progressed beyond simple dehydration into inflammatory or infectious territory. Topical steroids may be needed, but only under professional guidance, because misusing them on an infected area can worsen the outcome significantly. Understanding the mechanism behind saline-induced dry skin matters more than treating the surface symptoms. Once you recognize that osmotic dehydration is happening, prevention becomes straightforward. Protect the barrier, manage application technique, and moisturize properly. The skin will recover faster than you might expect if you stop the underlying cause.