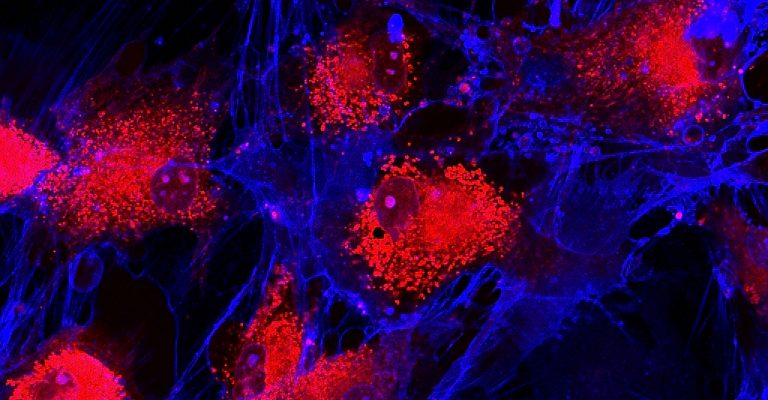
Working With Tissue Culture in Real Oncology Labs
I spent three years running 2D and 3D cell culture workflows in a translational cancer research lab. The kind of work that sits somewhere between routine technique and guesswork depending on which cell line you are trying to grow, whether your mycoplasma screening came back clean that week, and if the CO2 incubator decided to swing pH on a Thursday afternoon. Tissue culture is not glamorous. It is also where most of the actual biological insight comes from before anything touches a mouse or a clinician. The breakthrough narrative around tissue culture and cancer has gotten louder recently, mostly because organoid systems and patient-derived models have moved out of specialist cores and into standard cancer research groups. The technology itself is not new. What changed is accessibility, reproducibility, and the speed at which labs can go from biopsy to working model. That shift matters for drug screening, resistance studies, and mechanistic work that used to require a six-month lead time just to establish a line.
What Tissue Culture Actually Means in Cancer Research Today
Tissue culture is the maintenance and growth of cells outside their native organism, usually in plasticware with defined media, temperature, and gas conditions. In oncology, that covers conventional 2D monolayers, suspension cultures for hematologic malignancies, and the newer 3D systems like organoids, spheroids, and organ-on-a-chip platforms. Each has different throughput, biological relevance, and failure modes. Picking the wrong system for your question is a common mistake that wastes reagents and timelines. The cuttingedge world of tissue culture a breakthrough in cancer research is less about a single invention and more about convergence. Improved matrigel alternatives, standardized extracellular matrix coatings, feeder-free media formulations, automation in seeding and imaging, and better bioreactor scaling have all arrived at the same time. The result is that a lab with modest funding can now run patient-derived organoid pipelines that would have required a dedicated core facility five years ago.
How To Set Up a Practical Organoid Workflow for Tumor Samples
I will describe a workflow that works for solid tumor biopsies, not the idealized cell line case. The steps are routine but unforgiving if you skip details. Organoid culture begins with mechanical and enzymatic dissociation of the fresh specimen, selection of the epithelial or cancer stem cell fraction if your target is defined, embedding in matrix, and initiation in a growth-factor-supplemented medium that matches the tissue of origin. For colorectal-derived models, that means WNT, RSPN, and EGF support. For pancreatic or prostate, the factor balance shifts enough that you cannot borrow the recipe without. The first failure point is almost always viability during dissociation. Over-trypsinization destroys the progenitor compartment you need. Under-digestion leaves clumps that form useless aggregates instead of structured organoids. I solved that by running a time-course digestion on a small aliquot before committing the whole sample, checking dissociation quality under phase contrast rather than trusting the protocol book. The difference between a working batch and a lost biopsy is usually twenty minutes of enzymatic exposure and how gently you pipette afterward. After embedding, medium changes determine whether your organoids expand or collapse. Feeding every two to three days is standard, but the volume and composition depend on matrix lot, organoid size, and how much secreted waste accumulates. I switched from fixed-volume swaps to partial medium replacement once my later passages started showing uneven lumen formation. Keeping the old medium around for osmotic continuity reduced stress during the transition and improved consistency across replicates.
Get the Full Details
Why 3D Systems Outperform 2D Monolayers in Many Cancer Questions
Two-dimensional culture forces cells into an artificial adhesive context with uniform nutrient access and no mechanical confinement. Cancer biology does not happen that way in vivo. Drug penetration, hypoxic gradients, cell-cell signaling, and matrix stiffness all influence response. 3D organoid and spheroid models preserve at least some of those variables, which is why pharmacology readouts often diverge between 2D and 3D even for the same patient sample. The tradeoff is cost, throughput, and interpretability. 3D assays require more matrix, more media, and more careful imaging or readout optimization. High-content screens that work cleanly on flat plates need revalidation in depth. You also get more biological noise because each organoid can behave slightly differently, which matters when your effect size is modest. I learned that the hard way during a kinase inhibitor screen where the 2D IC50 looked promising but the organoid response was scattered due to variable penetration and heterogeneous target expression across the population. Another practical advantage of 3D culture is that it maintains differentiation states longer. Established cell lines tend to drift toward a simplified phenotype under continuous passaging. Patient-derived models retain more of the original tumor architecture and signaling context, which improves relevance for biomarker validation and mechanism work. That relevance comes with a cost in reproducibility between donors and between labs, so standardization is still an open problem.
Common Pitfalls That Waste Time and Samples
Contamination is the obvious risk, but mycoplasma and slow-growing bacterial contaminants cause more subtle damage. They alter metabolism, change drug sensitivity, and can make an otherwise healthy culture behave like a stressed one. I had a line that showed inconsistent proliferation and strange morphology for weeks before a PCR panel revealed mycoplasma. Removing it required discarding the culture and restarting from frozen stock, which set the project back by nearly two months. Regular screening, ideally every month, saves that kind of headache. Batch variation in matrix reagents is another silent issue. Matrigel and alternative hydrogels differ in growth factor content, stiffness, and protein composition between lots. I once attributed a biological effect to a treatment when it was actually a lot change in the embedding matrix. Running side-by-side controls with each new lot and documenting lot numbers in your lab notebook prevents that confusion. It also helps when reviewers ask for reproducibility details. Overpassaging is a third trap. Organoids and spheroids can be expanded for many cycles, but extended passaging selects for adaptable subpopulations and can erode the original tumor heterogeneity you wanted to preserve. I track passage number carefully and freeze early passages as working stocks. When a project requires multiple lines, I allocate dedicated flasks rather than sharing stocks across experiments, which reduces cross-contamination risk and keeps the biological signal cleaner.
Where Tissue Culture Falls Short for Cancer Research
No in vitro system captures the full tumor microenvironment. Immune cells, stromal fibroblasts, endothelial networks, and systemic metabolism all influence tumor behavior in ways that current organoid models only approximate. Co-culture systems are improving, and some labs now integrate patient-derived immune cells or stromal components, but standardization across labs remains limited. If your question depends heavily on immune checkpoint biology or pharmacokinetics, tissue culture alone will not answer it. Scalability is another bottleneck. Generating enough organoid material for mechanistic biochemistry, multi-omics, or preclinical dosing studies can require large initial biopsies and careful pool management. Small samples from needle cores sometimes yield insufficient viable cells for robust expansion, especially for poorly differentiated tumors. In those cases, I supplement with short-term explant culture or fallback to patient-derived xenograft if the sample quality allows, though xenograft introduces its own delays and ethical considerations. Reproducibility across institutions is still evolving. Different labs use different matrix products, media recipes, and passaging protocols, which makes direct comparison difficult. This is a field-wide issue, not a failure of the technology itself, but it means you should treat published organoid protocols as starting points rather than finished methods. Optimization for your specific tumor type and readout is usually necessary.

Practical Steps for Labs Starting Tissue Culture-Based Cancer Projects
Begin with a clear definition of your biological question. If you need high-throughput drug screening, 2D lines or simplified spheroid formats may suffice. If you need patient-relevant pharmacology or resistance modeling, invest in organoid infrastructure and training. The equipment and reagent costs differ substantially, and the skill ceiling for 3D culture is higher than most people expect. Establish standardized operating procedures early. Document media formulations, matrix lots, passaging ratios, and quality control checkpoints. I keep a single lab-wide document that records every variable, because forgetting which matrigel lot produced a given result is a mistake you only make once. Include mycoplasma screening dates, viability thresholds, and criteria for discarding or freezing cultures. Train team members hands-on before letting them work independently. Tissue culture technique looks simple until you are managing a sensitive primary sample and someone pipettes too aggressively or leaves the culture exposed to ambient conditions for too long. I require a supervised run of at least ten successful passages before granting independent access, and I pair new users with experienced colleagues for the first few months. The upfront time investment pays off in reduced sample loss.
Plan for failure modes. Not every biopsy establishes. Some lines die after early passage. Organoids can differentiate unexpectedly or collapse under suboptimal conditions. Keep backup strategies, such as cryopreserved stocks, alternative matrix options, and parallel 2D models when appropriate. Biology is unpredictable, and a good lab prepares for the cases where everything goes slightly wrong.
Looking Ahead Without the Hype
Tissue culture continues to improve, but incremental progress is more realistic than revolutionary change. Better matrices, automated imaging, and integrated multi-omics are arriving steadily. Immune-co-culture systems are becoming more common, though still technically demanding. Computational modeling of organoid growth and drug response is emerging, but validation remains limited. The most useful direction is probably integration rather than isolation. Combining organoid screening with computational prediction, patient clinical data, and selective in vivo validation produces stronger conclusions than any single method alone. I see that pattern working in translational projects where organoids identify candidates and xenograft or clinical correlation confirms relevance. The workflow is slower than pure in silico screening, but the outputs are more trustworthy. If you are considering adopting tissue culture methods for cancer research, start small, document everything, and expect to iterate. The technology is powerful, but it rewards patience and discipline more than enthusiasm. Laboratories that treat it as a mature technique rather than a magic solution tend to get better results over time.