What Actually Happens When You Study the Coronoid Process
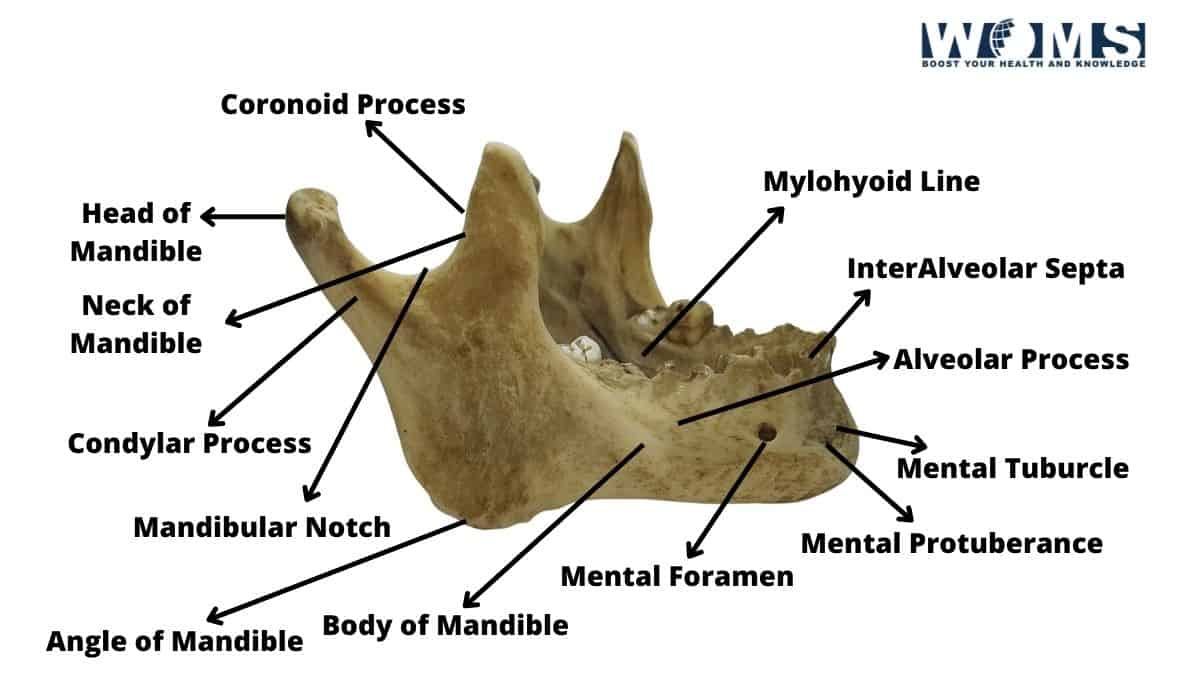
I spent a lot of time looking at this structure during dental school and then again when I was doing my residency in oral surgery. Most textbooks treat it like a footnote. It is not a footnote. It matters more than people give it credit for. The coronoid process is that thin, triangular projection sticking up from the anterior part of the mandibular ramus. It is not a condyle. It does not sit in the glenoid fossa. That is a common confusion right there. The temporalis muscle attaches to it, and that is the whole reason it exists in any meaningful way. The temporalis fans out across the side of the skull and narrows down into a tendon that inserts on the coronoid and the anterior border of the ramus. When that muscle contracts, it pulls the coronoid upward and backward, contributing to elevation and retrusion of the mandible. Simple enough. The complexity comes when you start looking at what happens under load.
Functional Mechanics That Nobody Talks About Enough
The coronoid process is not just a passive attachment point. It acts as a lever arm for the temporalis, and its dimensions vary significantly between people. Some folks have tall, slender coronoids. Others have short, broad ones. This is not cosmetic. It affects how much force the temporalis can generate and how that force is distributed through the mandible during chewing and clenching. There is also a relationship between the coronoid and the zygomatic arch that most people miss. The coronoid sits just below the arch, and during wide opening, it passes under the arch. In some cases, particularly with hypermobility or after trauma, the coronoid can impinge on the arch. That is a real problem, and it is easily overlooked because the pain pattern can refer to the temple or the ear, which makes clinicians think temporomandibular disorder without considering the actual mechanical collision.
Clinical Significance Where It Actually Matters
Fractures of the coronoid are surprisingly common in mandibular fractures, especially in children and young adults. They often get missed on standard panorex views because the superimposition of the zygomatic arch over the coronoid creates a visual mess on 2D imaging. I remember a case where a kid came in after a fall, the panorex looked fine, and the only reason I spotted the fracture was on the CBCT. The coronoid fragment was displaced medially. We monitored it conservatively and it healed without issue, but if we had gone with the 2D read alone, we would have missed it entirely. Coronoidectomy is another area where this structure becomes relevant. It is a standard procedure for certain types of trismus, particularly when there is fibrous or bony impingement between the coronoid and the zygomatic arch. I have done more than a few of these. The key is not just removing the coronoid but understanding how much to remove. Take too little and the restriction persists. Take too much and you risk damaging the temporalis insertion functionally. The sweet spot is usually around two-thirds of the coronoid height, depending on the preoperative range of motion measurement. There is also the issue of coronoid hyperplasia, which is rare but well documented. The coronoid grows excessively long and then gets stuck against the zygomatic arch during opening. These patients present with progressive trismus, and the diagnosis is straightforward once you are looking for it, but again, the panorex can mislead you. CBCT is the right tool here, and I would recommend it over plain film whenever coronoid pathology is on the differential.
Get the Full Details

What Beginners Get Wrong About This Structure
The biggest mistake I see is treating the coronoid as anatomically isolated. It is not. The masseter originates from the zygomatic arch and inserts on the lateral surface of the ramus, and the temporalis inserts on the coronoid. When the masseter and temporalis fire together, they create a compressive force on the condyle and a stabilizing force on the coronoid. Disrupt one side of that equation, and the other side compensates in ways that are not always obvious clinically. Another thing: the coronoid is a common site for myositis ossificans after trauma or surgery. It is not the most frequent location, but it happens enough that I have seen it more than once. A patient will come in weeks after a mandibular fracture repair complaining of decreased opening, and imaging shows heterotopic bone forming around the coronoid. The workaround in those cases is conservative management first. Physical therapy, NSAIDs, sometimes a short course of radiation if the ossification is aggressive. Surgery to remove the heterotopic bone is a last resort because recurrence rates are annoyingly high.
Practical Takeaways
If you are imaging a mandible and you suspect pathology around the coronoid, get a CBCT. It changes the diagnostic yield dramatically compared to 2D imaging. If you are planning a coronoidectomy, measure the coronoid height preoperatively and plan your resection based on the arc of motion you need to restore, not on a generic template. And if you are dealing with a coronoid fracture, do not rush to fixate every fragment. Many of these heal well without surgical intervention, and the morbidity of open reduction and internal fixation in this region is not trivial given the proximity of the temporalis tendon and the neurovascular structures nearby. The coronoid is small. It is easy to overlook. But it matters when you actually need it to function properly, and it matters even more when something goes wrong. Treat it with the attention it deserves.